Insights

HMA Insights: Your source for healthcare news, ideas and analysis.

HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.

or
or
Receive timely expert insights on topics you care about.

1356 Results found.

Medicaid Managed Care Enrollment: Q4 2025 Trends and Early Signals Ahead of New Eligibility Policies

Read Blog

This week Health Management Associates (HMA), draws on its database of monthly Medicaid managed care enrollment to present its latest quarterly analysis, offering a snapshot of enrollment trends across 37 states. 

The analysis comes at a critical time. As states prepare for Medicaid eligibility policy changes that take effect in 2027—including more frequent eligibility determinations and expanded work and community engagement requirements—current enrollment trends provide an early signal of how policy decisions and administrative practices are already influencing coverage levels. 

The HMA Information Services (HMAIS) analysis shows that Medicaid managed care accounted for 85.6 percent of total Medicaid enrollment in December 2025. This analysis, available to HMAIS subscribers, uses data from nearly 300 health plans in 41 states. The report provides by-plan enrollment plus corporate ownership, program inclusion, and for-profit versus not-for-profit status, with breakout tabs for publicly traded plans. 

Key Insights from Q4 2025 Data 

The 37 states included in this review have released monthly Medicaid managed care enrollment data through public websites or in response to a public records request from HMA. The report includes the most recent data obtained and illustrates the effect of state-level choices around eligibility and administration. Key findings include: 

  • As of December 2025, Medicaid managed care enrollment across the 37 states declined by 2.2 million members year over year, falling to 62.5 million—a 3.4 percent decrease. 
  • Of the 37 states, eight—Colorado, Delaware, Mississippi, Missouri, New Jersey, North Carolina, North Dakota, and Oregon—did not experience year-over-year managed care enrollment declines, and instead showed flat enrollment or modest gains. With the exception of Mississippi, these are all Medicaid expansion states. 
  • Arizona and Indiana experienced double-digit percentage declines. Notably, Indiana began requiring enrollees to actively respond to renewal mailers, which aligns with enrollment declines that began in March 2025. 
  • Among the expansion states in the analysis, enrollment declined by 1.7 million (-3.3%) to 50.8 million. The seven non-expansion states experienced a similar decline (-3.6%), bringing enrollment to 11.7 million enrollees. 

Data Considerations. The data have some important limitations. States report enrollment figures at different points during the month, with some data reflecting beginning of the month totals and others capturing end of the month enrollment. In addition, some state datasets encompass all Medicaid programs offering managed care plans, whereas others reflect only a subset of the managed Medicaid population. As a result, the findings should be viewed as indicative of broader trends rather than a comprehensive state-by-state comparison.  

Market Share and Plan Dynamics 

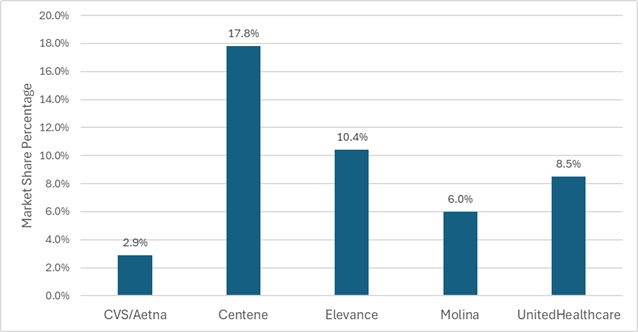
Using our data repository for 300 health plans across 41 states, HMAIS analyzes corporate ownership, program participation, and tax status among Medicaid managed care plans. As of December 2025, Centene maintained the largest share of the national Medicaid managed care market at 17.8 percent, followed by Elevance (10.4%), United (8.5%), and Molina (6.0%) (see Figure 1). These figures highlight continued concentration among large national plans, even as overall enrollment declines. 

Figure 1. National Medicaid Managed Care Market Share by Number of Beneficiaries for a Sample of Publicly Traded Plans, December 2025  
What to Watch  

Enrollment trends observed in the fourth quarter (Q4) of 2025 and continuing into 2026 indicate increasing state attention to eligibility policy and program integrity. State legislative activity, budget pressures, and federal regulatory developments are prompting many states to assess and strengthen certain aspects of their programs related to eligibility, particularly as they prepare to implement redetermination and work and community engagement requirements. 

Several states are already moving toward implementation. Nebraska is scheduled to launch Medicaid work requirements on May 1, 2026, while Montana plans to begin implementation on July 1, 2026. With additional federal guidance still emerging, most other states are working toward compliance ahead of January 2027 deadlines. In expansion states, policymakers retain authority to tighten administrative processes, alter optional benefits, or adjust provider payment levels—actions that may materially affect enrollment. 

These developments underscore why Medicaid managed care enrollment trends deserve close attention. Declines in enrollment are often an early indicator of broader system impacts, including rising uncompensated care for providers, shifts in payer mix, and increased financial pressure on safety‑net systems. For managed care organizations, even modest enrollment changes can mask more significant shifts in risk profiles, geographic concentration, or service needs. 

Connect with Us  

HMA is home to experts who know the Medicaid managed care landscape and how it is evolving. HMAIS’s Medicaid enrollment data, financials, procurement tracking, and a robust library of public documents equips stakeholders with timely, actionable intelligence. 

For more information about the HMAIS subscription, contact Andrea Maresca and Alona Nenko.  

HMA Resource Provides Key Insights about the Evolving Medicare-Medicaid Integration Landscape

Read Blog

People who are dually eligible for Medicare and Medicaid remain a central focus for policymakers and healthcare organizations, given their complex care needs, disproportionate share of spending, and the long-standing challenge of coordinating coverage across two programs. One of the primary vehicles for advancing integration has been Dual Eligible Special Needs Plans (D-SNPs), which continue to play an increasingly prominent role as federal and state policymakers encourage tighter Medicare-Medicaid alignment.

As states play a more active role in shaping enrollment rules, Medicaid contracting, and procurement strategies, the duals market is becoming more structured and more explicitly guided by state policy decisions. Health Management Associates (HMA’s) 2026 Duals Integration Environmental Inventory, examines how this shift shapes the integration landscape in 2026. This comprehensive inventory is based on a review of the 2026 market, insights from states, and other publicly available resources.

This article examines key trends from HMA’s 2026 inventory and addresses federal policy changes scheduled to take effect for 2027, which contribute to this dynamic environment.

What to Expect in 2026

As the landscape for duals integration evolves, the central question has shifted from whether D-SNPs operate in a state to the more consequential question of how states are using Medicaid policy levers (i.e., enrollment rules, procurement, contracting, and managed care structures) to drive tighter alignment between Medicare and Medicaid. 

At the federal level, recent Medicare Advantage and Part D rulemaking is reinforcing that movement. The Contract Year 2025 Medicare Advantage and Part D Final Rule finalized the second phase-down of the D-SNP look-alike threshold to 60 percent for 2026 and established 2027 rules that limit enrollment in certain D-SNPs to members of an affiliated Medicaid managed care organization. The rule also limits the number of D-SNP benefit packages that can be offered alongside an affiliated Medicaid managed care organization. More recently, the Contract Year 2026 Medicare Advantage and Part D Final Rule requires certain D-SNPs to use integrated member ID cards and integrated health risk assessments beginning in 2027. 

Together these rules signal a continued federal emphasis on linking D-SNP enrollment and operations more closely to Medicaid coverage and delivery systems, with states playing a greater role in determining how alignment is achieved. 

What the 2026 Inventory Shows

HMA’s 2026 Duals Integration Environmental Inventory shows how these policy signals are translating into state action. More specifically: 

  • Statewide exclusively aligned enrollment appears in 16 states in the 2026 inventory, up from nine in 2025. 
  • Applicable Integrated Plans (AIPs) are present in 22 states, up from 14, and default enrollment is in place in 21 states, up from 16. 
  • The inventory also captures 6,084,997 total D-SNP enrollees, including 1,975,250 in Highly Integrated SNPs (HIDE) and 743,683 in Fully Integrated SNPs (FIDE-SNPs). 

Those changes are already visible in state markets: 

  • Illinois, Massachusetts, Ohio, and Rhode Island entered 2026 with a greater FIDE-SNP presence tied to legacy Medicare-Medicaid Plan transitions. 
  • Michigan launched MI Coordinated Health as a HIDE-SNP in selected regions in 2026, with statewide expansion planned for 2027. 
  • Delaware also stands out: Although it already had AIPs in the 2025 inventory, it adds statewide exclusively aligned enrollment in 2026 and shows both HIDE-SNPs and coordination-only D-SNPs. 

A Resource to Track State Market Direction

HMA’s 2026 Duals Integration Environmental Inventory, available to HMA Information Services (HMAIS) subscribers, includes a state-by-state view of the Medicaid policy, contracting, and program structures shaping duals integration and D-SNP markets. In addition to enrollment trends, the inventory documents the integration model each state is pursuing, whether long-term services and supports or behavioral health are included in managed care, and how procurement and contract decisions may inform future market activity. 

HMA experts work with clients to apply this information and deepen their understanding of state integration approaches, inform assessments of their market readiness and alignment opportunities, and develop strategies that support more effective Medicare-Medicaid integration. 

Looking Ahead

Notably, HMA’s inventory reflects a point in time understanding of where an individual state is today and what is known at this time about their next steps and plans. However, we expect changes in many states as they seek guidance from the Centers for Medicare & Medicaid Services and the D-SNP community to implement required changes and adopt new regulatory provisions that support state goals and priorities. 

The 2026 inventory suggests that more states are using formal alignment tools, that more enrollment is concentrated in integrated products, and that more markets are being shaped by the interaction between Medicaid structure, procurement, and D-SNP strategy. 

Connect with Us 

For organizations seeking to understand where the market is headed, the Duals Integration Inventory offers a clear view of how state policy and market structure are evolving and where tighter Medicare-Medicaid alignment is taking hold. 

Contact Holly Michaels Fisher and Julie Faulhaber to discuss your organization’s questions and needs regarding an integration strategy and market analysis. For information about the HMAIS subscription, access to the Duals Environmental Inventory contact Andrea Maresca and Gabby Palmieri. 

Connected Crisis Care: Generating Collaborative Solutions for 988 and Beyond

Read More

HMA Solutions

Connected Crisis Care: Generating Collaborative Solutions for 988 and Beyond

Health Management Associates, Inc. (HMA), is a national leader in crisis system design, known for developing innovative, collaborative, data-driven solutions that help states and communities build effective, person-centered crisis response systems. We help strengthen crisis response systems through skill-building and collaboration strategies. Our model creates lasting crisis response system connections, fosters trust, and enhances the overall quality of care across the crisis response continuum.

Is your state, region, or county ready to enhance and sustain its crisis response?

Has your state recently launched 988, mobile crisis teams, or crisis stabilization units and is now exploring next steps to strengthen the system? 

Are you seeking practical, engaging training, and convening strategies to deepen collaboration and elevate your crisis response across all partners? 

Our Approach:

Coordinated Crisis Response Through Skill-Building and System Integration

Our team uses a two-prong approach to bring together a diverse group of providers, partners, and stakeholders to expand system capacity and build trust and collaboration across the crisis response continuum. Through a series of cross-system trainings and convenings, we lay the foundation for better communication, coordination, and collaboration. This approach ensures that individuals in crisis experience more seamless, coordinated, and compassionate care across every point of the response continuum.

Skill-Building:

Monthly Training Programs Tailored to Every Role in Crisis Response

"This training helped cross-train coping strategies for working with clients, reminded us that there is always a path through stress, and helped us focus on meeting individuals where they are in their journey." -Crisis care provider

We collaborate with our clients to determine the best approach for training that meets the needs of your organization. Our monthly virtual training courses are designed to meet crisis response providers where they are—across all levels of readiness and roles. Using diverse learning methods, such as didactic instruction, interactive problem-solving, and peer-to-peer collaboration, we ensure content is practical, engaging, accessible and grounded in best practice frameworks and protocols. Topics include culturally responsive mobile crisis response, trauma-informed care, suicide risk assessments, and working with diverse populations including youth, older adults, and individuals with intellectual/developmental disabilities. Each session builds real-world skills that can be applied immediately in the field. In addition, these courses can be set up to be taken on demand.

System Integration:

Systemwide Convenings to Build Trust and Drive Collaboration

"I appreciate having a variety of divisions and departments (i.e., HR) participating in these monthly convenings. Thank you for this opportunity and collaboration." - Crisis convening attendee

Through structured, facilitated convenings, led by HMA’s crisis response experts, we bring together a diverse network of crisis providers, partners, and stakeholders to strengthen coordination across the full crisis continuum. We use Liberating Structures and other learning techniques to enhance engagement, foster relational trust, share knowledge, and sustain collaboration. Convening topics can be aligned with the monthly training topics to reinforce learning and provide opportunities to operationalize new skills and understanding across the crisis continuum. Convenings often highlight local exemplars as a way to share local best practices and encourage locality-specific collaboration and problem-solving.

Ready to Build Trust and Capacity in Your Crisis System?

We are excited to partner with your crisis care system to help you create a transformative response model based on collaboration, trust, and ongoing professional development. In addition to this suite of offerings, the HMA team has expertise in helping communities develop and implement strategic roadmaps for next-phase crisis system improvement.

Who We Help

911/call centers/emergency management services (EMS)

Associations and foundations

Behavioral health care providers

Coalitions and advocates

Criminal justice stakeholders and facilities

Crisis care systems and providers

Educational settings and academic institutions

Federal, state, and local government agencies

Health plans

Hospitals and health systems

Investors

Law enforcement

Public health departments

Project Spotlight:

What Makes HMA Different?

Many of our team members are former executives and clinical leaders from the behavioral health sector. They bring decades of experience in leading behavioral health care in inpatient, outpatient and emergency department settings, and have been instrumental in establishing the 988 program. HMA provides the depth, agility, and collaborative approach to address today’s most urgent behavioral health challenges. We know the challenges faced by states and organizations, and support strategic planning and implementation, large scale crisis system redesigns, crisis needs assessments, and relationship building with stakeholders.

Contact our experts:

Headshot of Angela Bergefurd

Angela Bergefurd

Senior Principal

A seasoned behavioral health leader with more than 25 years of government healthcare experience, Angela Bergefurd has a deep understanding … Read more
Headshot of Allie Franklin

Allie Franklin

Managing Director

Allie Franklin is a licensed clinical social worker with decades of experience in public, private, and non-profit behavioral health, healthcare, … Read more
Headshot of Jennifer Hodgson

Jennifer Hodgson

Principal

Jennifer Hodgson is a licensed marriage and family therapist who maintained a private practice and taught in higher education for … Read more
Headshot of Monica Johnson

Monica Johnson

Managing Director

A skilled state and federal government executive, Monica Johnson has over 25 years of experience in the behavioral health field. … Read more
Headshot of Kim Williams

Kim Williams

Principal

Kim Williams is an experienced executive, policy leader and social worker with a record of transformational growth, accomplishment, and innovation … Read more

Medicare’s “Inpatient Only” Rule Is Going Away. Now What?

Listen Now

This episode of Vital Viewpoints on Healthcare explores how evolving Medicare payment policy is reshaping where and how care is delivered. The discussion covers the phase-out of the inpatient only list and the operational and financial challenges tied to shifting procedures into outpatient settings. Zach Gaumer, regional director at Health Management Associates, shares his perspective on the policy mechanics, provider behavior, and market signals emerging from CMS rulemaking; while Rachel Stewart, senior consulting actuary at Wakely (an HMA Company), explains how plans are modeling uncertainty, navigating contract dynamics, and assessing the downstream impact on costs and quality across the healthcare system.

CMS’s LEAD Model: A New Phase for Accountable Care and Application Considerations

Read Blog

The Long‑term Enhanced Accountable Care Organization (LEAD) Model represents the next major step in the Centers for Medicare & Medicaid Services (CMS) accountable care strategy and reinforces a federal commitment to value-based participation in Traditional Medicare. Announced as the successor to ACO REACH, LEAD is a voluntary, nationwide, 10‑year model that will operate from 2027 to 2036, making it the longest-running accountable care organization (ACO) model the Center for Medicare and Medicaid Innovation has tested.

Momentum around the LEAD ACO model has accelerated since CMS’s recent release of the Request for Applications (RFA), which formally moves LEAD from policy design to implementation. The RFA requires prospective participants to evaluate program design choices, financial implications, and operational readiness on a compressed timeline. Notably, CMS has indicated that additional opportunities to express interest will follow for organizations that are not prepared to apply for participation in the initial cohort.

This article explains key design elements of the LEAD model and identifies considerations for organizations assessing whether and when to pursue participation in LEAD.

Core Design Evolutions of the LEAD Model

While LEAD builds on many of the elements from ACO REACH, its design reflects how the Innovation Center intends to address challenges with previous ACO models, such as the Medicare Shared Savings Program (MSSP). At its core, LEAD seeks to establish a pathway to long‑term engagement in value-based care that creates an attractive option for all types of providers, including ACOs with a history of engaging in value-based care and providers that have yet to meaningfully participate.

LEAD introduces a set of targeted design changes intended to improve predictability, alignment accuracy, and long‑term participation in accountable care—most notably through revised benchmarking, updated beneficiary alignment, and expanded flexibility for engaging specialists and high‑needs populations.

1. Revising Benchmarking Policies to Support Predictability and Success

  • LEAD provides a major win for ACOs seeking long-term predictability by setting a long-term benchmark that will not rebase for the entirety of the 10-year model. In MSSP, many ACOs eventually face the “ratchet effect” in which benchmarks erode after rebasing to reflect the ACO’s more recent spending patterns. It can create a significant hurdle for ACOs that have already successfully reduced spending, as their own prior success lowers their benchmark. By not rebasing for the entirety of the model period, LEAD provides an attractive alternative to the MSSP, which rebases every five years.
  • LEAD will also support historically successful ACOs by transitioning to a fully regional rate book by the end of the model period. As a result, benchmarks will be set based on overall spending in the region where an ACO operates rather than an ACO’s historical spending. While ACO REACH also used a regional rate book to inform some ACO benchmarks, LEAD goes further by seeking to transition all ACOs to a benchmark based fully on a regional rate book while also adding protections for higher-spending ACOs by transitioning regions at different timelines to ensure that newer ACOs have the opportunity to implement the kinds of care delivery changes that lead to lower spending before they are subject to penalties.
  • Other notable changes to benchmarking include a variety of ACO-specific adjustments and the addition of an administrative component to benchmarking. ACOs will be eligible to receive a boost to their benchmarks with either a regional efficiency adjustment for ACOs with lower spending or a prior savings adjustment for ACOs with a demonstrated history of achieving savings. LEAD also introduces an administratively set component to benchmarking—the Accountable Care Prospective Trend—which already is used in the MSSP, though LEAD adds a new guardrail policy to promote predictability.

2. Improving Accuracy in Beneficiary Alignment

  • LEAD’s new “hybrid” alignment option increases accuracy and responsiveness. Monthly additions of voluntarily aligned beneficiaries and mid-year recognition of new participant taxpayer identification numbers (TINs) adopted after the start of the performance year (PY) allow alignment to better reflect real-time care relationships, averting lag and operational friction.

3. Adding Support for High-Needs Beneficiaries

  • LEAD expands support for beneficiaries with complex needs through a universal High Needs category and recalibrated risk adjustment. By moving away from ACO REACH’s population‑exclusive model, LEAD lowers barriers for organizations that serve a disproportionate share of high‑needs and dually eligible populations. In addition, CMS will test Medicare‑Medicaid alignment in two states, and help states develop arrangements supporting the provision of value-based care between ACOs and state Medicaid agencies or managed care organizations.

4. Promoting Deeper Engagement with Specialists

  • LEAD increases flexibility for engaging specialists in value‑based arrangements. New Non‑Primary Care Capitation options and episode-based risk arrangements (CMS‑Administered Risk Arrangements (CARAs)), allow ACOs to share risk with specialists without Total Care Capitation, reducing operational complexity while expanding accountability beyond primary care.

5. Advancing Technology Adoption and Innovation

  • LEAD introduces structured pathways to promote technology adoption. Planned Artificial Intelligence (AI)‑inferred risk adjustment will be phased in following successful testing and validation, while the Tech Enabler Initiative and Rapid Cycle Innovation Program seek to reduce administrative burden and accelerate evidence generation—particularly for smaller or resource‑constrained ACOs.
Next Steps

The Innovation Center is operating on an accelerated timeline for the initial LEAD cohort. Prospective ACOs have fewer than 50 days to digest a detailed Request for Applications and model potential performance. Applications are due May 17, 2026. ACOs that participated in ACO REACH in PY 2026 will be well-positioned, as many of the provisions in LEAD will be familiar, and the agency is permitting this group of ACOs to submit an abbreviated application for participation.

For organizations not ready to apply for the first cohort, CMS will release a standardized Letter of Interest form by April 17, 2026, to gauge interest in future application rounds. In this context, organizations considering LEAD participation should be assessing not only near‑term application readiness, but also longer‑term strategic alignment with the model’s 10‑year commitment, risk structure, and operational requirements. Key considerations include benchmarking predictability, readiness to manage regional benchmarks, capacity to engage specialists and high‑needs beneficiaries, technology capabilities, and alignment with broader value‑based care strategies across Medicare and Medicaid.

Connect with Us

Health Management Associates (HMA), supports organizations across the LEAD decision continuum, including those pursuing immediate application and those preparing for future cohorts. HMA can help organizations:

  • Interpret LEAD’s policy and financial design relative to existing ACO and MSSP participation
  • Model performance scenarios under alternative benchmark, alignment, and risk configurations
  • Assess operational readiness across care management, contracting, analytics, and compliance
  • Develop application strategies and supporting materials, including responses to the LEAD RFA
  • Choose to defer application on steps that preserve future optionality

As CMS advances LEAD under an ambitious timeline, early analysis and disciplined decision‑making will be critical for organizations seeking to align participation with their long‑term value‑based care strategies.

For questions contact Amy Bassano and Rebecca Nielsen.

Connecting the Dots: Medicaid Community Engagement Requirements and State Readiness for 2027

Read Blog

Our March 19, 2026, Connecting the Dots analysis described the federal requirements and the operational questions states and partners will need to answer to effectively implement Medicaid work and community engagement requirements. Since then, federal officials have advanced their forthcoming regulation to the final stage of review and intend to meet the statutory requirement to release interim final guidance by June 2026. In addition, many states have taken early steps to communicate upcoming changes and begin planning for system, policy, and partner readiness.

While state sessions are clearly grabbing a lot of energy, timing of pulling together many of the moving parts is becoming a concern as states undergo one of the most fundamental operational challenges to the Medicaid program since its inception. This article synthesizes emerging approaches and identifies practical opportunities to refine strategies and strengthen readiness while minimizing burden for enrollees and state Medicaid agencies.

Early Actions in States Preparing to Implement Work and Community Engagement Requirements

1. States Are Launching Websites that Highlight Coming Changes

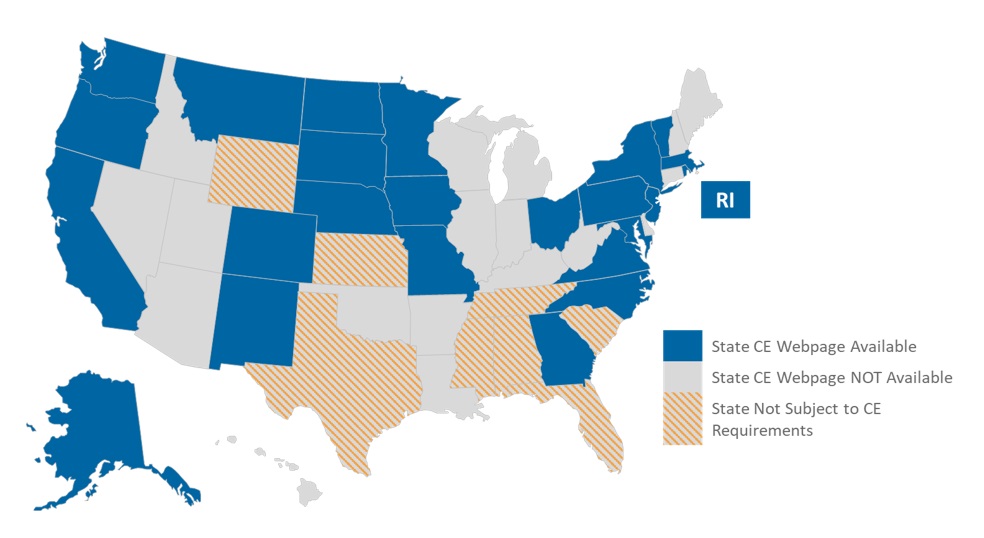
As of April 2026, more than half of US states that are subject to the Medicaid work and community engagement requirement had posted web page content describing forthcoming changes associated with the 2025 budget reconciliation act (P.L. 119-12, OBBBA). Some websites provide high-level descriptions of key provisions (e.g., qualifying beneficiary ages, qualifying activities, and exemptions), while others include more detailed information reflecting state-specific policy decisions, educational messages, and suggested steps that beneficiaries, providers, managed care plans (MCPs), and community-based stakeholders can take now (see Figure 1).

Figure 1. States with a Community Engagement Web Page

For example, Ohio’s website describes the requirements for, and provides examples of, acceptable documentation Medicaid members may use to demonstrate compliance or eligibility for an exemption. Ohio also offers a “Communications Partner Packet” that contains frequently asked questions (FAQs) and draft outreach materials to support stakeholder communications and increase awareness. The communications tools include a one-page flyer, a rack card, and potential social media posts to raise awareness of the changes, with some use of QR codes to enhance quick access to key websites like the beneficiary self-service portal.

2. States are Beginning to Make and Communicate Preliminary Policy Decisions

States must make a range of policy decisions, including the penalty start date, the number of required months of compliance for both the initial application and subsequent renewals, the potential adoption of short-term hardship exceptions, and how exceptions are defined and operationalized. While most states anticipate compliance beginning January 1, 2027, in alignment with OBBBA, Nebraska and Montana have announced plans to begin implementation in 2026, and their websites reflect additional policy details to support accelerated timelines.

A handful of states, including Arkansas and Ohio, also are communicating ahead of OBBBA’s timeline to promote awareness and engagement before the work and community engagement requirement becomes effective. Table 1 summarizes examples of the current state planning[1] around the number of required months of compliance for the initial application and renewals.

Table 1. Sample Number of Months in Compliance

States also are taking different approaches to exemptions and short-term exceptions. Although many exemptions and exceptions are defined in statute, the interpretation of “medically frail” remains an area in which states have significant flexibility, with implications for how many individuals are exempt. Many states have experiences with establishing definitions of medically frail. For example, states that offer an adult benefit package that differs from the state plan benefit package must allow medically frail adults to opt in to the state plan. At least 12 states already make medically frail determinations, and these existing policies and processes may inform approaches for work and community engagement requirements.

One of those states—Nevada—has posted a proposed definition of medically frail with a request for public comment, including a sample list of qualifying medical conditions. Although such lists can provide clarity, they also underscore the importance of a clear and straightforward exemption request process to support appropriate determinations, including for individuals with conditions that are omitted from a specified list.

3. States Are Securing Additional Support to Address Administrative Challenges

The new eligibility criteria, coupled with more frequent eligibility checks, are placing substantial new demands on Medicaid agencies, eligibility systems, and personnel. In response, states are considering or actively pursuing a range of approaches to strengthen administrative capacity. Examples include:

  • Hiring new state eligibility and enrollment workers: Indiana and Montana
  • Funding system enhancements and improvements: Alaska and New Jersey
  • Hiring outreach and engagement contractors: Arizona and Arkansas

States are also proposing to take a more coordinated, cross-agency approach that uses other state agencies and programs as data sources and referral pathways to help beneficiaries meet their work and community engagement requirements. A variety of states are looking to leverage data from their Supplemental Nutrition Assistance Program (SNAP) program to facilitate compliance checks, and Kentucky has proposed receiving data from a variety of sources (e.g., Department of Revenue, Department of Corrections, Unemployment Insurance, Vital Statistics, and others) to more automatically identify eligibility and exemption changes.

States like Hawaii, Montana, and Nebraska have highlighted their labor departments to connect people to job and community service resources. Virginia’s work and community engagement website directs the public to a series of different programs based on whether they are interested in employment, volunteer, or education resources. Minnesota also has introduced legislation proposing collaboration between the commissioner and county agencies to link beneficiaries to other critical services like job training, childcare, and transportation.

Shrinking federal contributions and constraints on Medicaid revenue strategies—such as limits on provider taxes—are prompting states to rethink how Medicaid agencies operate within existing budgets. Limited federal funding to support administrative needs elevates the importance of efficiency, coordination, and automation.

What States Might Do to Chart a Better Path Forward

A robust pre-implementation plan is critical to successful work and community engagement implementation. A well-documented plan helps states fully document the variety of moving parts across policy, systems, and partners, clarify milestones and decision points, and define what readiness looks like in practice.

Key components of a pre-implementation plan may include:

  • Signing agreements and contracts to support infrastructure. Pre-implementation planning should ensure that appropriate support from third-party vendors and sister agencies is secured to optimize flexibilities and manage the requirements. Examples may include maintenance of effort (MOE) agreements, memoranda of understanding (MOU), contract updates, and requests for proposals (RFP) as appropriate. States may need to use expedited contracting vehicles when available and maximize existing vendor arrangements. Agreements should address data governance, privacy, and cost allocation issues to support smooth operational integration and reduce downstream friction.
  • Quantifying and automating exemptions. Systems and reporting should be updated to identify, notify, and manage cases for expansion adults who are likely exempt. Leveraging additional resources and data matching may help states identify common exempt populations, such as caretakers with dependents under age 14, disabled veterans, and pregnant women without requiring additional verification. Understanding the demographics of the remaining nonexempt population may also be useful in outreach, education, and links to supports.
  • Preparing for readiness review, including system readiness, coverage transition, and churn management. Pre-implementation plans should prioritize robust system testing, staff training, and timely updates to required documentation (e.g., state plan amendments, policy and member manuals, notices, and reviewing and approving MCP communications). Building in clear transition supports for individuals who may lose coverage or transition to other coverage options can improve continuity of coverage, reduce uninsurance and uncompensated care, and limit administrative burden following implementation.
  • MCP contracts. Most enrollees subject to work and community engagement requirements are enrolled in Medicaid MCPs. States will need to describe enhanced roles and responsibilities in both the MCP contracts as well as the rates. Clear contract expectations can support transparency and mutual accountability across partners.
  • Test communications with the target audiences to ensure understanding and appropriate action. Awareness of the new work and community engagement requirement was one of the biggest challenges Arkansas faced when it launched its program in 2018. Beneficiaries also struggled to understand whether the requirement applied to them and what they needed to do to comply. States must build communications plans and messaging to clearly address these issues to reduce the number of beneficiaries losing coverage simply because they did not understand the new requirements.
Connect with Us

Health Management Associates (HMA) Medicaid experts assist Medicaid and state policymakers with the following:

  • Strategic positioning
  • Policy-to-operations design
  • Cross-agency governance and partner alignment
  • Information systems impact assessment, change planning, testing strategies and readiness metrics
  • Scenario planning and beneficiary impact analysis
  • Communications and operational playbooks
  • Program integrity, reporting, and audit support

HMA Medicaid experts can also assist MCPs, providers, and community-based organizations with:

  • Risk assessments (e.g., enrollment, utilization, and spending impacts)
  • State-specific policy and operational insights and trends
  • Communications, outreach, and engagement strategies and content
  • Member retention strategies
  • Grassroots workforce development and community engagement strategies

For questions, contact HMA contributors to this article Lora Saunders, Matt Powers, Andrea Maresca, and Amber Swartzell.

[1] Some of these policies are in pending legislation and, therefore, are subject to change.

Webinar Replay – Saving Lives with Compassion: Overdose Response Training with RiVive®

Watch Now

This webinar was held May 7, 2026.

This webinar presented findings from the 2025 RiVive Community Engagement Report and best practices in compassionate overdose response™, with a focus on the community use of RiVive naloxone nasal spray 3 mg. A panel of expert speakers presented their protocols for effective overdose intervention, guidance on the training of others, and strategies for integrating trauma-informed approaches into post-overdose care.

The webinar covered why compassionate dosing is important, how to integrate this concept into trainings for community members, and communication strategies for teaching titration, rescue breathing, and overdose prevention.

Learning Objectives:

  • Learn how to describe why compassionate dosing is important.
  • Apply evidence-based strategies for compassionate, trauma-informed intervention during overdose emergencies.
  • Integrate stigma-reducing practices into community response frameworks to enhance support for individuals affected by opioid use.

Speakers:

  • Dr. Michael Hufford, Co-Founder, CEO, Harm Reduction Therapeutics
  • Van Asher, Harm Reduction Consultant, Harm Reduction Therapeutics

CMS Quality Conference 2026: CMS Signals a Faster Path from Policy to Practice in Quality

Read Blog

The Centers for Medicare & Medicaid Services (CMS) convened the CMS Quality Conference 2026 (QualCon) at a moment when healthcare quality policy is increasingly being shaped through formal rulemaking as well as informal policy signals and implementation vehicles. The discussions reflected CMS’s core priorities—wellness and prevention, digital infrastructure, patient safety, and program integrity—and reinforced a broader theme that CMS intends to continue to move faster to advance these priorities than traditional regulatory timelines allow. 

Health Management Associates (HMA) experts attended QualCon and are working with healthcare organizations as they interpret these signals and prepare to implement the policy priorities highlighted during the conference. This article describes these cross-cutting issues and highlights strategies and actions healthcare entities can take now. 

Moving Faster Requires Different Approaches to Policy and Implementation 

CMS Administrator Dr. Mehmet Oz emphasized CMS’s increasing use of voluntary commitments, public-private collaboration, Requests for Information (RFIs), and other informal policy tools as alternatives or precursors to formal requirements, creating an imperative for early stakeholder engagement. 

  • CMS leaders highlighted stakeholder convenings as a key vehicle to drive change outside of regulatory processes, including the pledge by health plans to streamline and improve prior authorization requirements. These commitments may signal future regulatory mandates and shifts in the marketplace. 
  • The CMS Health Tech Ecosystem provides the foundation for quality initiatives. The CMS Administrator highlighted the 600-plus organizations that have committed to the goals of the CMS Health Tech Ecosystem, including companies that support conversational artificial intelligence (AI) assistants that would make ingestion and sharing of data with healthcare providers easier through the “Kill the Clipboard” efforts, and have pledged to support interoperability. 
  • CMS is using listening sessions and RFIs to shape the direction and drive quality policy. The agency leaders invited new ideas and reinforced the value of feedback received through RFIs, citing examples such as the 2025 RFI on the Health Technology Ecosystem, Medicare Advantage improvements, and the RFI on Comprehensive Regulations to Uncover Suspicious Healthcare (CRUSH). CMS leaders also convened sessions pertaining to patient safety, dialysis care, and best practices for medication for treatment of opioid use disorder, signaling these are areas under consideration for policy development. 

Health and Wellness Positioned as a Core Component of Quality Efforts 

QualCon prominently featured CMS’s commitment to promoting health and wellness. Dr. Oz discussed underutilization of existing benefits, such as annual wellness visits, and CMS Deputy Administrator and Director of the Center for Medicare, Chris Klomp, focused on community-based approaches to prevention. Mr. Klomp also spoke of ongoing interest in moving physician payment toward primary care and away from specialty procedures. 

CMS officials highlighted new Center for Medicare and Medicaid Innovation (Innovation Center) models, such as ACCESS (Advancing Chronic Care with Effective, Scalable Solutions) and Make America Healthy Again: Enhancing Lifestyle and Evaluating Value-based Approaches Through Evidence (MAHA ELEVATE), which are aligned with the Administrator’s policy priority of empowering patients. CMS officials also acknowledged challenges to behavioral change and the levers CMS is employing in new models, including technology and incentives for beneficiaries, partnerships, and community health workers. 

Digital Infrastructure Framed as Necessary for Quality Reforms 

QualCon also emphasized making quality measurement fully digital, specifically using FHIR® (Fast Healthcare Interoperability Resources) specifications. Agency officials reported having FHIR specifications for 70+ measures and characterized FHIR as the standard for new measures. Use of FHIR aligns with broader interoperability rules, including one requiring state Medicaid programs and payers participating in public programs to use FHIR for electronic prior authorization by January 2027. 

Quality measurement leaders spoke about the value of integrating quality data in real time and the move from “lagged scorecards” to “continuous intelligence.” Notably, attendees expressed enthusiasm about the potential for AI to support measurement and personalization of quality, measures addressing trajectories of care over time, and new approaches to risk adjustment. 

Application of AI to Patient Safety Is on the Horizon 

Patient safety discussions focused on the potential for AI‑enabled tools to identify risk earlier and prevent harm, particularly with regard to medication safety and error prevention. CMS speakers emphasized that realizing these gains depends on intentional governance, standardized workflows, and patient involvement in AI development and deployment. Rather than positioning AI as a substitute for clinical judgment, sessions framed it as an augmentation tool requiring clear safeguards and accountability. 

Avoiding Fraud, Waste, and Abuse 

CMS leaders noted the potential to avoid fraud, waste, and abuse through a cross-functional fraud detection center that can analyze claims in real time. CMS also discussed collaboration with states and private insurers and encouraged external input. 

Medicaid Discussions 

Medicaid received more limited attention at this conference. CMS Medicaid officials reiterated interest in having fewer quality measures and engaged in discussion with state leaders on how to focus quality efforts. They highlighted learnings about the Medicaid early, periodic, screening, diagnosis, and treatment (EPSDT) program and from CMS Innovation Center models centered on maternal health and substance use disorder care. 

What We’re Watching Next 

Following QualCon HMA experts are continuing to follow several federal quality-related initiatives that affect plans, health systems, states, and other healthcare delivery organizations include: 

  • How CMS translates voluntary commitments and Health Tech Ecosystem initiatives into lasting policy expectations for transforming quality 
  • The pace at which digital quality measurement shifts from pilot to standard practice 
  • How AI governance frameworks evolve alongside additional real-world use cases in quality and safety 

Connect with Us 

HMA, including Leavitt Partners and Wakely, work with healthcare organizations to navigate the transition to digital quality measurement and act upon digital quality data to improve healthcare delivery. 

Wakely uses analytics-driven operating design and return on investment (ROI) analysis, clinical data acquisition models and tools, and pilot-based validation of measure rates and processing performance to support scalable digital quality measurement (dQM) adoption, as outlined in the dQM Playbook. 

Leavitt Partners is working with federal agencies on a number of activities related to the CMS Health Tech Ecosystem and interoperability, including the Kill the Clipboard initiative, which was informed by a seminal Leavitt Partners white paper. In addition, Leavitt Partners convenes the Digital Quality Implementers Community, which is working to solve both technical and policy issues in digital quality measurement. 

For details, contact our experts below.

Outlook 2026: Regulatory Uncertainty, Evidence Evolution, and the Future of Healthcare Innovation

Read Blog

As healthcare innovation accelerates, regulatory and policy frameworks are evolving just as rapidly. Across drug development, medical devices, diagnostics, and emerging therapies, innovators are navigating a landscape shaped by shifting federal signals, changing evidentiary expectations, and growing pressure to align regulatory success with real‑world access and affordability. 

This article draws on insights from experts at Health Management Associates, Inc. (HMA), and Leavitt Partners, an HMA company, who bring decades of experience working within the US Food and Drug Administration (FDA) and in collaboration with industry leaders to address complex regulatory, commercialization, and access challenges. Their perspectives reflect firsthand experience with translating policy intent into operational reality across the healthcare ecosystem. 

These insights underscore a central theme in early 2026: Innovation is advancing faster than the policy frameworks designed to support it. For developers, investors, payers, and policymakers alike, the challenge is no longer whether innovation is possible, but whether regulatory and coverage pathways can evolve quickly and coherently enough to support it. 

A More Fragmented Policy Signal Environment 

Historically, federal health policy followed relatively formal and predictable channels—rulemaking, guidance documents, and established notice and comment processes. Today, innovators increasingly receive policy signals through nontraditional and informal mechanisms, including agency websites, journal articles, speeches, podcasts, and pilot initiatives. 

This evolution in communication and how we ingest information has two implications. 

First, it creates greater uncertainty for market planning, as policy direction often emerges incrementally or indirectly. In addition, the higher stakes are higher for understanding the federal regulatory environment. Organizations that closely track agency behavior, precedent, and internal norms are better positioned to distinguish meaningful change from repackaged status quo. 

For innovators operating on 10‑to-15-year development timelines, even modest policy volatility can materially affect research and development (R&D) investment decisions, pipeline prioritization, and commercialization strategies. 

Innovation Is Outpacing Traditional Evidence Models 

Scientific progress, especially in rare disease therapies, advanced biologics, and precision medicine, can both strain and challenge traditional clinical trial paradigms. Small patient populations, heterogeneous disease pathways, and novel mechanisms of action are making large, randomized trials increasingly difficult or impractical. 

In response, federal regulators are signaling a broader openness to: 

  • Real‑world evidence (RWE) 
  • Natural history studies 
  • Registries and longitudinal data 
  • Biomarkers and intermediate endpoints 

These approaches are not new, but their expanding role reflects a recognition that traditional evidence hierarchies alone are no longer sufficient for evaluating next‑generation therapies. At the same time, regulators continue to emphasize that alternative evidence must meet rigorous scientific standards, particularly when used to support initial approval or expanded indications. 

The implication for innovators is that evidence strategy can no longer be an afterthought. Developers must design programs that support regulatory approval and downstream coverage, pricing, and post‑market evaluation. It is possible for evidence frameworks to overlap, but they must remain distinct. 

Regulatory Approval Is a Midpoint for the Innovator Product Journey 

A recurring challenge across healthcare sectors is the disconnect between regulatory approval and payer coverage decisions. While regulators focus on safety and efficacy, payers assess value, durability of response, and budget impact because they often struggle to justify large upfront payments within their annual budgeting structure. 

This misalignment is particularly acute for high-cost therapies with long-term benefits and products approved through accelerated or flexible pathways, where long-term value may misalign with short-term payer budgeting cycles. 

As policymakers explore ways to modernize regulatory frameworks, questions remain about whether coverage and payment systems will adapt in parallel. Without greater alignment, innovators may continue to face scenarios where regulatory success does not translate into timely or consistent patient access. 

Predictability and Durability Are Emerging Policy Priorities 

Looking further ahead in 2026 and beyond, predictability and durability—not just flexibility—are emerging as core priorities for industry and policymakers alike. Flexibility is essential to support innovation, but durable policy frameworks, particularly those derived from statute, offer greater confidence in long‑term investments. 

Several themes will likely shape the next phase for how federal health policy handles innovation: 

  • Streamlining early clinical development, including first‑in‑human studies 
  • Codifying successful regulatory pathways to ensure durability across presidential administrations 
  • Clarifying expectations for post‑market evidence generation 
  • Improving transparency and consistency in agency advice 

These efforts reflect a broader recognition that innovation ecosystems depend not just on scientific breakthroughs, but also on stable rules of the road. 

Why It Matters 

For healthcare innovators, the policy environment in 2026 presents both opportunity and risk. They can leverage new evidence frameworks, engage earlier with regulators, and shape emerging policy conversations; however, they also face risks linked with unpredictability, misaligned incentives, and uncertainty around long‑term access and reimbursement. 

Successful innovation will increasingly depend on industry partners with integrated strategies that connect regulatory planning, evidence development, policy engagement, and market access from the earliest stages of innovation. 

For policymakers, the challenge is to modernize regulatory and coverage frameworks in ways that support innovation without sacrificing rigor, affordability, or public trust. 

Connect with Us 

As healthcare continues to evolve, one thing is clear: Innovation policy is no longer a niche concern. Rather, it is central to the future of access, outcomes, and system sustainability. 

For further exploration of these issues, listen to HMA’s recent podcast on how evolving regulatory frameworks are shaping innovation, commercialization, and access across healthcare. The discussion features insights from Ben Shand of HMA and Julie Tierney of Leavitt Partners, whose combined experience spans senior roles within FDA and extensive collaboration with industry on complex regulatory and policy challenges. The conversation expands on the themes highlighted here, including regulatory predictability, evidence evolution, and strategies for navigating uncertainty across the product life cycle. 

The takeaway is clear: Waiting until late in development to collaborate with regulators and policymakers is no longer a viable strategy. Organizations that engage earlier and more actively are better positioned to anticipate shifts, shape the conversation, and avoid costly misalignment between approval and coverage. 

HMA can help you identify where the policy landscape is creating new opportunities and where risks may emerge. We work with organizations to develop proactive engagement strategies that align with today’s changing environment, especially when traditional approaches are no longer delivering results.

Ready to talk?