Insights

HMA Insights: Your source for healthcare news, ideas and analysis.

HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.

or
or
Receive timely expert insights on topics you care about.

1351 Results found.

Graduate Medical Education (GME) Consulting

Read More

HMA Solutions

Graduate Medical Education (GME) Consulting

Build and sustain GME programs that strengthen the workforce and expand access to care. HMA provides graduate medical education consulting for hospitals, health systems, federally qualified health centers (FQHCs, both teaching health centers and those that are not) and GME consortia that want to assess, build, expand, finance, operate or improve GME programs.

Who needs GME consulting support?

Hospitals, health systems, FQHCs (both those that are teaching health centers and those that are not) and GME consortia use graduate medical education to address workforce shortages, expand access, develop new care models and align training with community needs. Establishing or strengthening a GME program, however, requires more than accreditation. Leaders must align strategy, financing, operations, educational quality, clinical capacity and long-term sustainability.

HMA helps organizations make informed GME decisions and move from planning to implementation. HMA supports clients across the GME life cycle, from early feasibility and strategic planning through program development, accreditation, launch, ongoing operations, performance improvement and growth.

Which organizations need this service?

Hospitals considering a new residency program

Health systems expanding existing GME programs

FQHCs and teaching health centers evaluating GME participation

GME consortia developing shared training infrastructure

Organizations seeking accreditation, financing, operational or compliance support

Why organizations choose HMA

Our team of experts brings together GME accreditation expertise, financial and reimbursement strategy, operational implementation experience, workforce and population health insight and health policy knowledge.

Our approach helps leaders:

Assess whether GME is the right strategy for their workforce and access priorities

Understand the operational and financial requirements of a new or expanded program

Build accreditation-ready infrastructure and applications

Strengthen existing programs and improve performance

Align GME investments with community health and physician workforce needs

Develop practical plans that can be implemented and sustained

HMA can help leaders move from opportunity to execution.

Assess GME feasibility and strategic fit

Organizations need to determine whether and how GME can support their broader goals. This process may include assessing physician workforce needs, specialty opportunities, organizational readiness, partnership options, population health priorities and the potential impact of a new or expanded program.

Build or Expand GME programs

We can support the major decisions and workstreams required to establish a GME program, including sponsoring institution applications, consortium development, GME infrastructure design, program director recruitment, specialty applications, curriculum development, site visit preparation, project management and launch planning.

Strengthen GME operations and compliance

Existing programs may need additional capacity, stronger processes or support in response to changing requirements. HMA provides GME office support, GME Committee (GMEC) planning and materials, policy and procedure development, Annual Institutional Review and Special Institutional Review support, Clinical Learning Environment Review (CLER) readiness, compliance audits, quality monitoring, technology-enabled services and updates on emerging GME issues.

Improve financial sustainability

GME programs require a clear understanding of costs, reimbursement, funding sources and financial risk. HMA helps clients evaluate financial performance and develop sustainable strategies through financial modeling, reimbursement analysis, direct and indirect GME payment strategy, FQHC prospective payment system (PPS) impact assessment, fiscal intermediary assistance, grant writing, teaching health center funding strategy, business terms for agreements and documentation and coding support for teaching physicians.

Build educational quality and leadership capacity

Strong programs depend on prepared leaders, engaged faculty, effective coordinators and reliable educational processes. HMA supports faculty development, curriculum design and evaluation, Annual Program Evaluations, Clinical Competency Committee and Program Evaluation Committee training, coordinator training, Designated Institutional Official (DIO) and GME leadership development, board and senior leadership education and resident and faculty well-being.

Align GME with workforce and population health priorities

GME is most valuable when it supports the communities and care systems an organization serves. HMA helps clients connect GME strategy to physician workforce needs, regional priorities, specialty access and population health goals. Support may include strategic planning, physician needs assessments, state and regional consultations, large data analyses, economic impact analyses, specialty program design, benchmarking, outcomes monitoring and disaster management or program closure support.

Transform primary care residency clinics

For organizations seeking to transform ambulatory training environments, HMA supports implementation of the 10 building blocks of high-functioning primary care residency clinics: engaged leadership, data-driven improvement, empanelment, team-based care, patient-team partnership, population management, continuity, access, comprehensiveness and care coordination, future-state clinic design, scheduling, resident engagement and work-life redesign.

Questions leaders should be asking

What workforce and access challenges should GME help us address?

Is our organization ready to sponsor, expand or strengthen a program?

Which specialties and training locations best align with community needs?

What infrastructure, leadership, partnerships and operational capacity will be required?

How will the program be financed and sustained over time?

Are our current systems supporting accreditation, educational quality and resident well-being?

How can GME strengthen our primary care delivery model and long-term workforce pipeline?

GME FAQs

What is graduate medical education consulting?

Graduate medical education consulting helps hospitals, health systems, FQHCs (those that are teaching health centers and those that are not) and GME consortia assess, build, expand, finance, operate and improve residency and fellowship training programs. HMA supports organizations across the full GME life cycle, from feasibility and strategic planning to accreditation readiness, program launch, operations, compliance and long-term sustainability.

How can an organization determine whether to start or expand a GME program?

Before starting or expanding a GME program, organizations should evaluate workforce needs, specialty demand, clinical training capacity, leadership readiness, partnership opportunities, accreditation requirements and financial sustainability. HMA helps clients conduct GME feasibility assessments and develop practical recommendations that align training investments with organizational strategy and community health needs.

What does a GME feasibility assessment include?

A GME feasibility assessment may include market and workforce analysis, specialty opportunity assessment, clinical site capacity review, organizational readiness evaluation, financial modeling, funding and reimbursement analysis, partnership strategy and implementation planning. The goal is to help leaders understand whether GME is viable, what resources are required and which program model is most sustainable.

How can HMA help with GME accreditation readiness?

HMA supports accreditation readiness by helping organizations develop the infrastructure, documentation, policies, governance processes, educational design and project plans needed to sponsor institution and residency program applications. This support may include application development, GMEC planning, curriculum design, site visit preparation, Annual Institutional Review support, CLER readiness and program improvement planning.

How can organizations finance and sustain GME programs?

Sustainable GME programs require a clear understanding of costs, reimbursement, funding sources and financial risk. HMA helps organizations evaluate DGME and IME payments, teaching health center funding, FQHC PPS impact, grant opportunities, fiscal intermediary considerations, business terms and financial models that support long-term program viability.

Can FQHCs and teaching health centers participate in GME?

Yes. FQHCs, teaching health centers and community-based organizations can play an important role in GME by supporting training models that expand access, strengthen primary care and build physician workforce pipelines in underserved communities. HMA helps organizations assess readiness, evaluate partnership models, understand funding implications and design sustainable clinical training environments.

When should an organization seek outside GME consulting support?

Organizations should consider outside GME consulting support when they are evaluating whether to launch or expand a program, preparing for accreditation, developing a sponsoring institution application, assessing financial sustainability, strengthening operations or compliance, transforming residency clinics or aligning GME strategy with physician workforce and population health priorities.

A practical partner for GME growth

Let HMA connect your GME strategy with the realities of accreditation, financing, operations, workforce development and care delivery. We combine GME accreditation expertise, financial and reimbursement strategy, operational implementation experience and health policy insight to help clients make defensible decisions and execute with confidence. Whether you need a focused readiness assessment, support with a new program, help improving an existing program or an end-to-end roadmap for sustainable growth, HMA can tailor the right level of support.

Ready to strengthen or expand your GME program?

Connect with HMA to assess readiness, evaluate financial and operational requirements or develop a customized roadmap for sustainable GME growth.


CMS Marketplace Anti-Fraud Actions: Financial and Strategic Implications for ACA Health Insurers

Read Blog

Program integrity has become an urgent, administration-wide healthcare priority, placing the Affordable Care Act (ACA) Marketplace under heightened scrutiny. On September 22, 2026, the Centers for Medicare & Medicaid Services (CMS) announced Federal Marketplace anti-fraud actions with immediate operational and financial implications for insurers. 

This week, actuaries from Wakely Consulting Group, an HMA company, examine how Marketplace disenrollment actions could affect health insurers in 2026 and beyond across enrollment, morbidity, risk adjustment, financial reporting, operations, distribution strategy, and future pricing. 

CMS Marketplace Anti-Fraud Actions and Unauthorized Enrollment Cancellations 

CMS’s three-part program integrity strategy focuses on preventing fraudulent and improper enrollments, removing confirmed unauthorized enrollments, and enforcing Marketplace requirements for agents and brokers. The agency also established a Federal Marketplace anti-fraud coordination group comprising leaders from CMS and the US Department of Health and Human Services (HHS) to direct these efforts. 

CMS reported canceling approximately 315,000 enrollments covering more than 760,000 individuals after determining that the coverage was unauthorized. The agency expects approximately $2.2 billion in advance payments of the premium tax credit (APTC) to be returned and will continue working with insurers to identify additional cases, prevent improper subsidy payments, and recoup prior payments. 

This action follows a June 2026 report from the HHS Office of the Assistant Secretary for Planning and Evaluation, which identified approximately 1 million highly suspicious agent- and broker-assisted HealthCare.gov enrollments involving applications without a Social Security number and members paying no premium. 

Although the absence of a Social Security number does not independently establish fraud, the September announcement sends a strong signal about CMS’s willingness to cancel enrollments confirmed as unauthorized. 

Financial and Operational Implications for ACA Marketplace Insurers 

Enrollment Losses and Morbidity Risk for ACA Marketplace Plans 

In their August 2026 white paper, Implications for Potential Marketplace Unauthorized Enrollment Actions, actuaries from Wakely noted that while the overall enrollment reduction is known, its distribution across issuers and markets is not publicly available. If canceled members are disproportionately healthy or had limited healthcare utilization, their removal could increase average claims among the remaining population. For example, if non-utilizers represented 10 percent of an issuer’s enrollment, removing them would increase average claims per member per month by approximately 10 percent, assuming no other changes. 

ACA Risk Adjustment Implications of Marketplace Disenrollments 

Changes in enrollment and morbidity could materially affect ACA risk adjustment transfers, but the results will vary according to each issuer’s concentration of confirmed or potentially unauthorized enrollment. Issuers with greater exposure to canceled enrollment could see more favorable risk adjustment results even as average claim costs increase. Those transfers may not fully offset deterioration in the remaining risk pool, which underscores the need for plan- and state-specific analysis. 

APTC Recoupment and Financial Reporting Considerations for Insurers 

The timing and process to recoup approximately $2.2 billion in APTCs has near-term financial reporting considerations. Issuers should evaluate potential effects on: 

  • Premium and APTC accruals 
  • Risk adjustment transfer accruals 
  • Per member claims cost estimates 
  • Premium deficiency reserve considerations 

According to CMS, the cancellations announced in September 2026 will be applied retroactively to original effective dates. The full effect of this heightened scrutiny, however, will depend on how CMS approaches recoupment and how quickly issuers process enrollment and financial adjustments.  

Issuers may also incur near-term costs associated with identifying and investigating suspicious enrollments, reconciling records with CMS, processing cancellations, adjusting revenue accruals, supporting affected consumers, and updating broker oversight. Lower enrollment also leaves fewer premium dollars available to cover fixed administrative expenses. 

How CMS Disenrollments Could Affect Future Marketplace Premiums 

As 2027 premiums are finalized, issuers will need to consider enrollment and morbidity shifts for 2028 prices. Insurers with established monitoring and projection processes will be better positioned to assess new CMS information and adjust forecasts as policy and enforcement evolve for 2026 and 2027. 

CMS Broker Enforcement and Marketplace Distribution Risks 

In addition to strengthening oversight of enrollment data, CMS has intensified enforcement of agent and broker requirements. Since January 2026, the agency has sent termination notices to more than 200 noncompliant agents and brokers and issued 569 notices of intent to terminate Exchange Agreements associated with 2026 applications that lacked identifying applicant information. Issuers should assess concentration by broker, monitor enrollment quality, and consider how enforcement may affect acquisition channels, member mix, and future growth. 

Market-Level Variation in Marketplace Disenrollment Risk 

The effects of CMS’s actions are limited to Federally Facilitated Marketplace (FFM) states and state-based Marketplaces using the federal platform (SBE-FM) and do not extend to state-based Marketplaces operating their own eligibility and enrollment systems. Individual issuer effects could vary materially based on several factors, including state, county, issuer, product, broker channel, and member premium contribution. 

Some issuers will be more exposed than others, particularly those with more enrollees paying low or $0 net premiums, greater broker reliance, substantial automatic reenrollment, or a strong presence among lower-cost plans. Understanding the financial impact will require analysis at the plan and market levels. 

Key Actions for Health Insurers Following CMS Marketplace Disenrollments 

Health insurers should assess a range of outcomes at the plan and state levels. This analysis should show how the concentration and health profile of canceled enrollment could affect claims, APTCs, risk adjustment, financial accruals, administrative expenses, distribution, and future rates. 

The timing of CMS’s actions will shape those outcomes. Because the announced cancellations apply retroactively to original effective dates, insurers will need to account for APTC recoupment and related enrollment and financial adjustments. The ultimate impact will depend on the data CMS provides, the scope of additional reviews, processing timelines, and any appeals or corrections. Issuers should revisit their forecasts as these details emerge and federal actions continue ahead of the 2027 plan year. 

Assessing Marketplace Disenrollment Risk: How HMA and Wakely Can Help 

Health Management Associates (HMA) and Wakely Consulting Group combine policy, market, actuarial, and financial expertise to help health plans and state regulators assess the effects of Marketplace program-integrity actions. For insurers, our teams can develop plan-by-plan and state-by-state projections of enrollment, morbidity, claims, APTCs, risk adjustment, and premiums; test prospective and retrospective cancellation scenarios; and translate the findings into pricing, forecasting, distribution, and market strategy decisions. 

State insurance regulators in affected FFM and SBE-FP states will need a market analysis of how the cancellations are distributed across issuers and whether changes in enrollment and morbidity could affect rates, risk adjustment, capital, or continued plan participation. Regulators should also evaluate whether approved 2027 rates and financial assumptions remain supportable and monitor solvency and consumer access as insurers adjust to this and CMS’s broader program integrity actions. HMA and Wakely can support this work through state-specific market assessments, issuer-level stress testing, rate and risk-pool analysis, and scenario projections that help regulators identify emerging concerns and act before they threaten market stability.

Pennsylvania Health Policy Conference 2026: What’s Next for Medicaid Enrollees, Rural Hospitals, and the Workforce

Read Blog

State of Reform (SOR), an HMA Company, hosted its inaugural Pennsylvania Health Policy Conference in Harrisburg on September 16, 2026, bringing together more than 170 interest-holders, including state health and human services departments leaders, policymakers, providers, health plans, community‑based organizations (CBOs), and others to discuss the most pressing health-related issues in the commonwealth. 

The conference focused on how federal Medicaid policy changes, managed care challenges, and workforce shortages, are reshaping Pennsylvania’s healthcare landscape while highlighting prevention and cross-sector collaboration as essential to building a more sustainable system. Key discussions are highlighted below. 

Central Discussions: Federal Medicaid Policy, Managed Care, and the Workforce 

Pennsylvania Medicaid 

Valerie Arkoosh, MD, Secretary of the Pennsylvania Department of Human Services (DHS) opened the conference by examining how federal policy and fiscal pressures are likely to affect Pennsylvania’s health and human services system. She discussed the anticipated loss of Medicaid coverage for approximately 310,000 enrollees due to the 2025 budget reconciliation act (P.L 119-21, now known as the Working Families Tax Cut Act [WFTCA]) and the resulting strain on individuals, providers, and the broader healthcare system. 

WFTCA and broader financial pressures also raise concerns about the sustainability of hospitals, with closures threatening access to care, especially in rural and underserved communities. Hospitals and safety-net facilities are consistently working against staffing shortages, capacity constraints, and shifting payer dynamics. Pennsylvania is using funds from the Rural Health Transformation Program (RHTP) to support struggling rural hospitals as best it can. DHS has awarded $42 million in RHTP grant fund awards so far to support various rural facilities. 

Medicaid managed care 

Community HealthChoices (CHC), Pennsylvania’s Medicaid managed long-term services and supports (MLTSS) program, has been at the forefront of the healthcare conversation in the state as a result of the cancellation of its 2024 contract awards for the program. In June 2026, DHS released a request for information seeking responses on several topics that could shape a new CHC re-procurement, including the number of Medicaid managed care organizations (MCOs) within CHC, regional versus statewide coverage, length of contract terms, strategies to align coordination of Medicare and Medicaid, artificial intelligence (AI), and other program recommendations. 

During the managed care discussion, Sally Kozak, Deputy Secretary of the Office of Medical Assistance Programs, and Emily Katz, Executive Director of Pennsylvania Medicaid MCOs, joined health plan leaders in assessing how well the physical health managed care program is improving access, quality, and cost management. 

The conversation centered on persistent challenges involving provider participation, care coordination, the complexity of administering the programs, and the variation in performance by region. There are opportunities to reform or refine managed care to better align incentives with patient needs and system sustainability. 

Workforce shortages 

Like all states, Pennsylvania is facing a health professional shortage across all sectors. Jennifer Hale, Director of the Bureau of Policy and Regulatory Management in the Office of Long-Term Living, and Garry Pezzano, President and Chief Executive Officer of LeadingAge PA, highlighted how this issue is affecting people who need long-term care. Speakers emphasized that Pennsylvania’s ability to meet the needs of an aging population will depend largely on strengthening the workforce that delivers these services. They explained several of the strategies underway and being discussed to achieve this goal, for example by improving wages and benefits for direct care workers, strengthening education and training pipelines, expanding loan repayment programs, prioritizing recruitment, and investing in technology for telehealth services and AI-assisted workflows. 

Advancing Change: Upstream Interventions and Collaboration 

Paying for care continues to be a chief concern. While many of the financial pressures come from within the healthcare system as the result of policy and budgetary challenges, throughout the conference speakers emphasized that many of Pennsylvania’s most pressing healthcare challenges begin outside the healthcare system. Food insecurity, unstable housing, transportation barriers, limited caregiver support, and lack of social and community supports worsen health outcomes and lead to increased healthcare expenditures. 

Panelists called for greater investment in upstream prevention services that help people remain healthy and independent before their needs become more acute to contain costs over time. Speakers recommended approaches such as expanding housing supports, food as medicine initiatives, community health worker investments, caregiver supports, reentry services, and technology that allows people to receive care at home, as well as other initiatives to ensure people can remain healthy and independent. 

Pennsylvania has already begun investing in several of these areas. The fiscal 2027 budget allocated $1.9 million to the Investments in Health pilot program for housing stability services and reentry supports for incarcerated individuals. Federal matching dollars for the first year of this program total $5.2 million. Another tool, PA Navigate, connects people with CBOs, state agencies, and providers that can help people access basic necessities. 

Speakers also stressed that these efforts will have limited reach if organizations operate separately. Better coordination among healthcare providers, MCOs, CBOs, hospital systems, and state agencies can reduce the fragmentation, make services easier to navigate, and help funding and data systems support common goals. That message was consistently expressed throughout the conference: Pennsylvania’s healthcare challenges cannot be addressed by one sector alone, and progress will depend on sustained collaboration among the organizations that serve individuals and communities. 

Looking Ahead 

If you are looking for strategies and solutions to address urgent healthcare policy and operational challenges, Health Management Associates (HMA) experts are available to help you navigate these complex changes and identify practical paths forward. 

Through the HMA National Conference, State of Reform partnership events, and other HMA meetings across the country, we connect state leaders, providers, health plans, and community stakeholders to share insights, elevate lessons, and advance solutions. Join us at an upcoming event—including our next HMA National Conference in New Orleans, LA, October 5–7, 2026—or explore additional opportunities to engage with HMA and access the full schedule of conferences and resources. 

State of Reform develops its conference agendas through collaboration with HMA subject matter experts/market leads and stakeholders across the public and private sectors, including state officials, community-based organizations, providers, payers, and more.

VA Community Care Program: Richard Topping to Discuss NextGen VA at HMA 2026 Conference

Read Blog

Health Management Associates (HMA) is pleased to welcome The Honorable Richard F. Topping, Assistant Secretary for Management and Chief Financial Officer at the US Department of Veterans Affairs (VA), to HMA’s US Healthcare 2026: Signals, Signs & Flashing Lights conference, October 5-7, 2026, in New Orleans, LA. His participation will give health plans, providers, technology companies, and other organizations interested in working with the VA Community Care program a timely opportunity to hear directly from senior VA leadership about the priorities shaping the program’s next phase. 

VA Community Care Priorities and Opportunities for Collaboration 

HMA’s Jean Glossa, MD, MBA, FACP, will join Mr. Topping during Community Care for Veterans—NextGen VA to discuss priority healthcare issues for the VA. They will examine the VA care delivery system, Mr. Topping’s areas of oversight, and opportunities to better integrate care delivered by VA providers with services furnished by contracted community providers. 

In addition to its direct care system, the VA operates six national payer programs, including VA Community Care—now the fourth-largest health insurer in the United States. Mr. Topping will describe how the VA is shifting Community Care from a network administration model toward a true healthcare purchasing and performance‑management model. CCN NextGen is the VA’s first major modernization of Community Care contracting since the MISSION Act, which took effect in 2019. This 10‑year, multiple‑award IDIQ structure will increase competition, enable regional adaptability, and support iterative improvements through sequential task orders opening up new opportunities for industry to partner with the VA. 

Explore Best Practices for Working with the VA 

Mr. Topping also will participate in one of HMA’s Coffee Conversations and Collaborations, a highly interactive format, which fosters practical discussion. Participants will have an opportunity deepen their knowledge about effective approaches to working with the VA, ask questions, and share experiences. This combination of senior-level perspective and smaller group dialogue makes Mr. Topping’s participation especially relevant for managed care plans, provider organizations, technology firms, and other partners monitoring the direction of VA Community Care. 

Join VA and Healthcare Leaders at HMA’s 2026 Conference 

HMA is honored to host Mr. Topping and create space for a substantive discussion about the future of VA Community Care. Register for HMA’s US Healthcare 2026 conference to hear directly from leaders who are shaping public healthcare and connect with peers working to turn policy priorities into stronger systems of care. 

The Value of Home-Based Personal Care Services

Register Now

This webinar, supported by TEAM Services Group, will provide an overview of home-based care, including the populations served, key service types, and delivery models. Experts will discuss findings from a review of the value of home-based care, highlighting its potential to stabilize health, improve the care experience, reduce unnecessary healthcare utilization, and enhance safety and satisfaction for both individuals receiving care and their family caregivers. The webinar will also examine opportunities to expand access to high-quality home-based care, including policy and system-level strategies that can strengthen the structural components needed to make these services more widely available to those who could benefit.

Learning Objectives

  • Describe the fundamentals of home-based care, including target populations, service types, and delivery models.
  • Review evidence on the value of home-based care, including its potential to improve clinical outcomes, reduce unnecessary healthcare utilization, generate cost savings, and enhance patient and family caregiver satisfaction.
  • Identify policy levers and system-level strategies that can strengthen high-value long-term services and supports (LTSS), including home-based care, and improve access to quality services.

Community Health Assessments & Improvement Plans

Read More

Flexible, actionable support to help communities move from assessment to measurable community health improvement.

Community health leaders need clear, credible, and actionable community health assessment/community health improvement plan (CHA/CHIP) processes that satisfy accreditation expectations while helping partners align around shared priorities. Health Management Associates (HMA) supports public health agencies, hospitals, collaboratives, and community partners with right-sized services that move efficiently from assessment to strategy to measurable improvement.

Why Communities Choose HMA

Practical support designed around local goals, capacity, and community priorities

Right-Sized Scope – Select the level of support that fits your timeline, budget, staffing, and readiness

Meaningful Engagement – Bring community members, partners, and decision-makers into the process in purposeful ways

HMA’s CHA & CHIP Service Offerings

Three flexible pathways—plus add-on support tailored to your community

Every community starts from a different place. HMA’s flexible CHA/CHIP pathways make it easy to select the right level of support and add only the enhancements that advance local priorities.

FOUNDATIONAL

Foundational CHA
MAPP Essentials


Best for: Smaller or rural communities, limited budgets, & routine CHA updates.

Focus: Efficient, PHAB-ready assessment.

COMPREHENSIVE

Comprehensive CHA
MAPP Standard


Best for: Most counties, regions, and accreditation-driven efforts.

Focus: Full MAPP process with comprehensive community engagement.

ADVANCED

Deep Engagement & Equity-Centered CHA
MAPP Advanced

Best for: Large jurisdictions, regional collaborations, and transformation-focused initiatives.

Focus: Community co-creation, equity, systems change, and implementation readiness.

Optional Enhancements

Add targeted support to any pathway based on local priorities, accreditation needs, and implementation goals.

Community Engagement

Focus groups, surveys, listening sessions, and culturally specific outreach

Advanced Analytics & Equity

Neighborhood analysis, equity assessments, and disparities analysis

Data Visualization & Communications

Geographic Information Systems (GIS) mapping, dashboards, and public-facing materials

Accreditation & Planning Support

PHAB documentation, CHIP facilitation, and early implementation planning

Project Examples

Community Health Assessment and Improvement Planning Resources

How can communities move from a compliance-driven assessment to a connected system for improving health?

These four reports demonstrate how HMA partners with communities to conduct Community Health Needs Assessments (CHNAs), CHAs, CHIPs that examine local health conditions, identify priority needs, advance health equity, and inform measurable strategies for action.

The reports represent communities in Oregon, Washington, California, and Colorado. They demonstrate the value of combining community voice, quantitative and qualitative data, cross-sector partnership, priority setting, implementation planning, and performance measurement.

A Community-Informed and Equity-Centered Health Assessment of Clackamas, Multnomah, and Washington counties in Oregon and Clark County in Washington State

Prepared for the Healthy Columbia Willamette Collaborative, this regional assessment brings together community input and data to identify health needs across four counties and support coordinated, equity-centered planning for a collaboration across public health, hospitals, and health systems.

Read the 2025 Community Health Needs Assessment →

San Bernardino County: Our Community Vital Signs

Prepared for San Bernardino County Department of Public Health, this community health assessment provides information about the health and well-being of San Bernardino County residents. It is designed to support community understanding, priority setting, cross-sector collaboration, and evidence-informed health improvement efforts.

Read the San Bernardino County Community Health Assessment →

Prepared for the Imperial County Community Health Improvement Partnership, this CHIP translates identified health priorities into strategies and actions designed to improve health outcomes across Imperial County.

The plan illustrates how communities can connect assessment findings to implementation, partnership, accountability, and measurable progress.

Read the Imperial County Community Health Improvement Plan →

Prepared for the Yampa Valley Regional Collaborative, the Yampa Valley Community Health Needs Assessment was developed through a collaborative effort involving The Health Partnership, Memorial Regional Health, Northwest Colorado Health, Routt County Public Health, UCHealth Yampa Valley Medical Center, and United Way.

The report combines community survey findings, community meetings, and public health and socioeconomic data. It identifies two priority areas for Yampa Valley:

  • Behavioral health
  • Access to culturally and linguistically responsive health care

It also identifies four important drivers of health: 1) access to healthy foods; 2) affordable housing; 3) economic opportunity, including jobs and wages; and 4) transportation.

Read the 2022 Yampa Valley Community Health Needs Assessment →

From Assessment to Action

A CHA or CHNA is more than a compliance document. It can serve as the foundation for a connected planning system.

Community engagement → Data and assessment → Priority setting → Implementation → Measurement and accountability

These reports offer practical examples of how HMA approaches this important work with communities to gather input, analyze local conditions, identify priorities, plan responses, and create stronger pathways from assessment to measurable action.

Communities represented

  • Clackamas County, OR
  • Multnomah County, OR
  • Washington County, OR
  • Clark County, WA
  • San Bernardino County, CA
  • Imperial County, CA
  • Yampa Valley and Routt County, CO

Topics covered

Community health assessment, community health needs assessment, community health improvement plan, CHA, CHNA, CHIP, health equity, community engagement, community voice, behavioral health, access to health care, culturally and linguistically responsive care, social determinants of health, social drivers of health, cross-sector collaboration, public health planning, hospital community benefit, priority setting, implementation planning, performance measurement, and community health improvement.

Medicaid Managed Care Enrollment Declines in Q2 2026: HMA Analysis of State Trends and Market Share

Read Blog

Health Management Associates (HMA) analyzed monthly Medicaid managed care enrollment data reported by 34 states in the second quarter of 2026. Enrollment totaled 59.2 million members in June 2026—a decline of 3.5 million members (5.5%) from June 2025. The broader Medicaid and CHIP population has declined at approximately the same pace as managed care, with the Centers for Medicare & Medicaid Services (CMS) data showing a 5.9% decrease from May 2025 to May 2026. 

The findings establish a timely baseline before new eligibility policies take effect. Under the 2025 budget reconciliation act (P.L. 119-21), now known as the Working Families Tax Cut (WFTC) Act, most states must implement Medicaid community engagement requirements for certain adults beginning January 1, 2027, conduct eligibility redeterminations every six months for this population, and implement other policies that will narrow Medicaid eligibility. 

Medicaid Managed Care Enrollment Trends in Q2 2026 

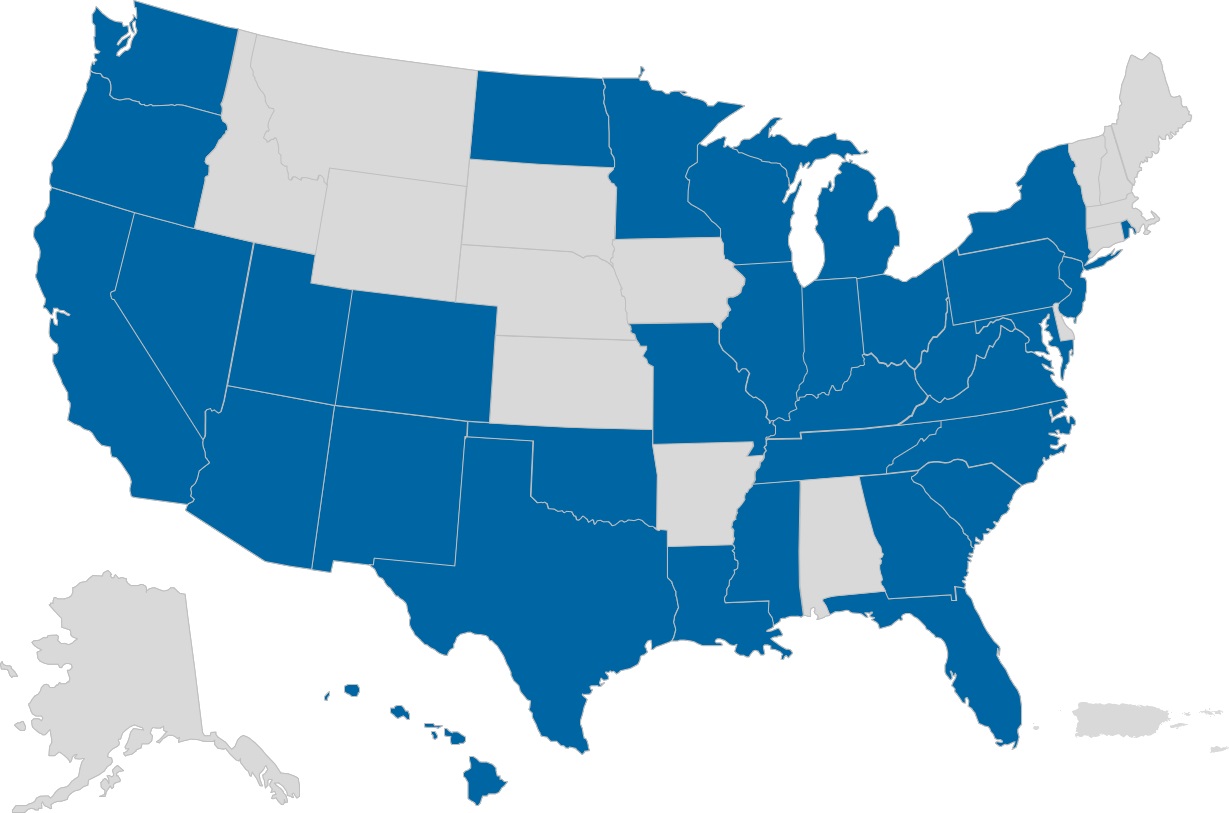
HMA Information Services (HMAIS) tracks monthly Medicaid enrollment for all states, including managed care enrollment in the subset of states with managed care programs. Among the 34 states with managed care programs that reported enrollment data in the second quarter of 2026: 

  • Enrollment changes varied across states, reflecting a combination of state-specific demographic, administrative, operational, and policy factors. 
  • Only three states—Mississippi, Nevada, and South Carolina—reported modest gains in Medicaid managed care enrollment since June 2025. 
  • Arizona, Indiana, and Louisiana each reported double-digit declines, ranging from 10.1% to 21.1%. 
  • The seven non-expansion states in this analysis—Florida, Georgia, Mississippi, South Carolina, Tennessee, Texas, and Wisconsin—experienced a decline of 455,000 (3.8%), bringing enrollment to 11.6 million enrollees. 

Among the expansion states in the analysis, enrollment decreased by 3 million (5.9%) to 47.6 million. The larger decline among expansion states is particularly relevant because adults in expansion states will be most directly affected by the new community engagement and six-month redetermination policies. Details are illustrated in Figure 1. 

Figure 1. States Included in the Medicaid Managed Care Enrollment Analysis, June 2026

Note: States colored as blue shown on the map above are included in the HMA Enrollment Analysis. 

National Medicaid Managed Care Market Share 

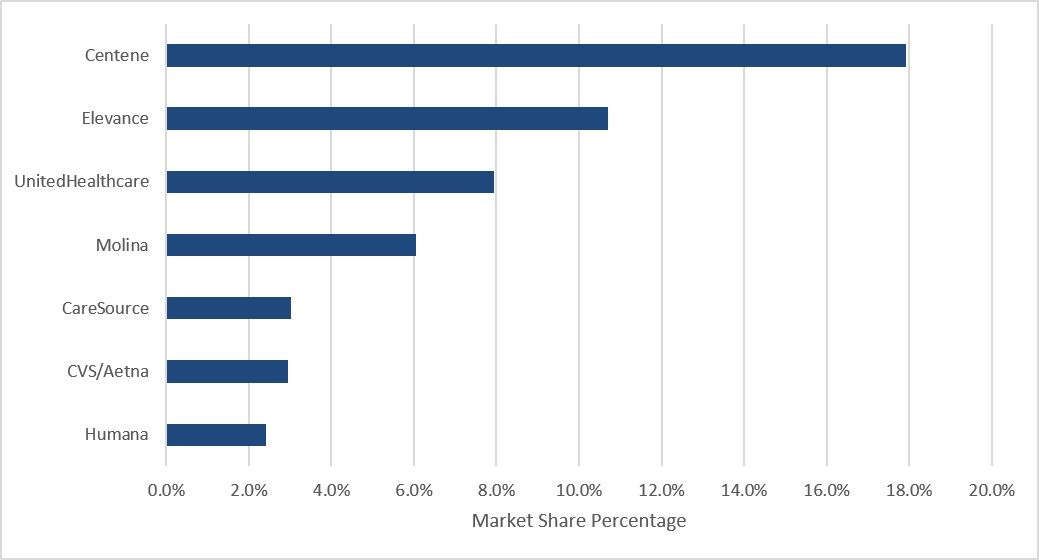
HMAIS also tracks Medicaid managed care ownership, program participation, and tax status for nearly 300 plans. In this June 2026 snapshot, Centene covered 17.9% of enrollees, followed by Elevance at 10.7%, UnitedHealth Group at 8%, and Molina at 6% (see Figure 2). These four organizations represented 42.6% of enrollment in the HMAIS dataset, underscoring continued concentration among large, national Medicaid managed care organizations. (Note: The number and mix of plans changed over the past 12 months, and several state enrollment reports reflect different reporting months. Other limitations are discussed in the Data Considerations section of this article.) 

The enrollment declines as well as pressure from acuity, utilization, and payment rates are compelling Medicaid managed care organizations (MCOs) to reassess where they participate, including whether individual markets can support sustainable performance. For example, one national Medicaid MCO has publicly discussed exiting unprofitable Medicaid markets and left one state market in August 2026 with plans to exit another at the end of the year. These decisions illustrate how enrollment contraction can interact with rate adequacy, acuity, utilization, and state-specific contract performance to influence plan participation. 

Figure 2. National Medicaid Managed Care Enrollment Share by Parent Organization, June 2026 

How Medicaid Work Requirements and Eligibility Policies Could Affect Enrollment in 2027 

In June 2025, approximately 20.4 million people were enrolled in Affordable Care Act Medicaid expansion plans—5 million of whom reside in California, and nearly 2 million live in New York. The WFTC Act applies requirements to Affordable Care Act (ACA) expansion adults and certain Medicaid Section 1115 demonstration populations in 44 states beginning January 2027. 

In September 2026, CMS published an implementation resource that outlines an optional framework that states may use to identify and verify individuals who qualify for the medical frailty exclusion. Although the framework gives states options for consideration, they still must determine which health conditions to cover and data sources to use when additional documentation is requested and how to notify members of their determinations. Many states have already made decisions about these issues, which could materially affect administrative workload, the consistency of determinations, and whether eligible individuals maintain coverage as well as the number of people who retain coverage and the composition of the population that remains enrolled. 

In addition, a few states have already started implementing the new eligibility policies. For example, Nebraska launched Medicaid work/community engagement requirements on May 1, 2026. Montana began implementation on July 1, 2026, while Arkansas began a soft launch in July 2026 before enforcement begins in January 2027. Iowa intends to begin early implementation December 1, 2026. Although Montana and Arkansas are not managed care states, they, along with Nebraska, can offer directional insights on beneficiary response, exclusion determinations, procedural losses, appeals, and administrative workload before nationwide implementation. 

Notably, the second quarter enrollment decline predates full implementation of the new federal eligibility policy changes and community engagement requirement, which means future enrollment changes may not be entirely attributable to the WFTCA requirements. 

Organizations should continue to monitor total enrollment, churn, eligibility category, risk mix, and transitions to Marketplace or uninsured status. 

Data Considerations. HMA Information Services (HMAIS) tracks monthly Medicaid managed care enrollment, ownership, program participation, and tax status for approximately 300 plans. The data in this analysis have some important limitations. States report enrollment figures at different points throughout the month, with some data reflecting beginning of the month totals and others capturing end of month enrollment. In addition, some state datasets encompass all Medicaid programs that offer managed care plans, whereas others reflect only a subset of the managed Medicaid population. As a result, the analysis can be used to identify direction, magnitude, and market signals rather than as a comprehensive state-by-state comparison. 

The HMAIS enrollment reports and analyses, available through subscription, use data from nearly 300 health plans in 39 states, DC, and Puerto Rico. HMAIS’s Medicaid enrollment data, financials, procurement tracking, and a robust library of public documents equips stakeholders with timely, actionable intelligence. Subscribe here. 

Preparing for Enrollment Shifts

WFTC Act implementation will require state-specific policy decisions, eligibility system changes, new data-matching processes, staff training, beneficiary outreach, and workable approaches to identifying people who qualify for exemptions for medical frailty and other conditions. Differences in data availability, verification pathways, documentation requirements, and review processes could produce materially different effects on enrollment, continuity of coverage, beneficiary experience, and the risk profile of the population that remains enrolled. 

Healthcare executives and state Medicaid leaders should establish a baseline, monitor emerging implementation signals, and model the operational and financial implications. Priority measures include enrollment and churn, procedural terminations, exclusion determinations, appeals, transitions to other coverage, changes in acuity and utilization, payer mix, and geographic variation. These insights can inform decisions about eligibility operations, beneficiary support, capitation and rate development, network strategy, provider reimbursement, revenue forecasting, and uncompensated care exposure. 

MCOs are unable to help states with determining eligibility determination or compliance, cannot receive capitation rate bumps for non-medical activities, or use their own work programs to help beneficiaries meet the community engagement requirements but may be able to provide support through outreach and education. CMS has indicated it expects to provide additional guidance on what activities are appropriate. MCOs can potentially use their existing relationships with beneficiaries, care managers, providers, and community organizations to help members understand and navigate the new requirements. 

HMAIS provides the market intelligence needed to track these shifts, including state-reported enrollment, plan ownership, financial performance, procurement activity, and related public documents. HMA consultants extend that intelligence through state- and market-specific scenario modeling, policy and operational analysis, and implementation support—helping clients forecast enrollment and revenue, assess payer mix and utilization effects, strengthen eligibility and beneficiary support workflows, evaluate competitive positioning, and prepare for changes in program financing and oversight. 

Contact HMA to translate evolving enrollment and implementation signals into an actionable strategy for your state, market, or organization.

Medicaid Funding Changes, Eligibility Requirements, and the Safety Net: What Community Leaders Need to Know

Read More

HMA Solutions

Medicaid Funding Changes, Eligibility Requirements, and the Safety Net: What Community Leaders Need to Know

Federal policy and funding changes are reshaping Medicaid, healthcare delivery, human services, and the local safety net. HMA helps healthcare, Medicaid, human services, and community leaders assess the impact of federal funding changes, protect access to care, strengthen local safety-net systems, and develop practical implementation strategies.

Communities Face Converging Fiscal and Service Pressures

Changes to Medicaid financing, eligibility, and community engagement requirements will not remain contained within state Medicaid agencies. The effects can move across health systems, local government, human services programs, community-based organizations, and households. When coverage becomes harder to maintain, people still need care and support. The costs and responsibilities often surface elsewhere in the community.

Hospitals and healthcare providers may face greater uncompensated care and pressure on already vulnerable service lines. Counties and municipalities may encounter increased demand for behavioral health, public health, housing, emergency response, and other locally supported services. Human services agencies may need to implement more complex processes without additional workforce capacity. Community-based organizations may be asked to help people navigate new requirements while also managing reductions or instability in their own funding.

These pressures will not be distributed evenly. Children and families, people with disabilities, older adults, rural residents, people experiencing homelessness, low-income working adults, pregnant and postpartum people, individuals with behavioral health needs, and people involved with child welfare systems may face heightened risk when administrative complexity and service constraints increase.

Supporting the Leaders Closest to Community Impact

HMA works with the organizations responsible for financing, administering, delivering, and sustaining healthcare and community supports.

State Medicaid agencies, health and human services departments, and executive and legislative leaders

Counties, municipalities, public health agencies, and local human services systems

Hospitals, rural health organizations, safety-net providers, health plans, and provider associations

Behavioral health organizations, child welfare agencies, housing and homelessness systems, and family-serving organizations

Community-based organizations, coalitions, foundations, associations, and cross-sector partnerships

Our multidisciplinary teams connect Medicaid and healthcare expertise with human services, community systems, organizational strategy, operations, financing, analytics, and implementation support. That breadth allows HMA to help clients understand not only what a policy change requires, but also how the change will affect people, providers, partners, workflows, budgets, and outcomes.

HMA Can Help Leaders Move from Uncertainty to Action

HMA can tailor support to a single organization, local community, statewide system, or cross-sector coalition. Engagements may include rapid analysis, operational planning, stakeholder engagement, implementation support, and performance monitoring.

Assess Policy and Fiscal Impact

Translate federal and state changes into clear implications for coverage, enrollment, provider reimbursement, service utilization, administrative cost, workforce demand, and local government exposure.

How HMA helps: Policy analysis, fiscal-impact assessment, coverage and enrollment scenario planning, provider vulnerability analysis, local cost-shift analysis, and executive briefings.

Prepare Medicaid and Eligibility Operations

Help agencies and partners prepare for eligibility, verification, reporting, data-matching, communication, and coverage-retention challenges while reducing avoidable administrative burden.

How HMA helps: Operational readiness assessments, workflow mapping, data-gap analysis, implementation roadmaps, community communications, and performance measures.

Evaluate Safety-Net and Provider Vulnerability

Identify where reductions in coverage or reimbursement may threaten access, critical service lines, rural providers, behavioral health capacity, maternity care, specialty services, and community-based care.

How HMA helps: Provider and service-line vulnerability assessments, market and network analysis, rural access review, scenario modeling, mitigation planning, and monitoring dashboards.

Strengthen Community Infrastructure

Assess whether community-based organizations and local partners have the capacity, funding, data, referral relationships, and operating infrastructure needed to absorb new responsibilities.

How HMA helps: CBO capacity and sustainability assessments, referral-network mapping, partnership strategy, reimbursement opportunity analysis, sustainability planning, and technical assistance.

Build Cross-Sector Response Plans

Bring healthcare, Medicaid, human services, public health, housing, workforce, philanthropy, and community partners together around shared risks, priorities, roles, resources, and accountability.

How HMA helps: Stakeholder engagement, facilitated convenings, governance design, shared implementation planning, resource mapping, and accountability frameworks.

Redesign Human Services and Community Systems

Help agencies align policy, funding, operations, workforce, technology, community voice, and performance expectations so systems can function more effectively under constraint.

How HMA helps: Current-state assessments, operating-model redesign, workforce strategy, change management, implementation tools, and continuous quality improvement structures.

Develop Sustainable Financing Strategies

Help clients move beyond reliance on a single funding source by identifying opportunities to maximize, blend, braid, and sequence public and private resources.

How HMA helps: Funding opportunity scans, Medicaid optimization, financing and reimbursement strategy, financial modeling, grant and partnership strategy, and sustainability roadmaps.

Use Data to Target Resources and Track Results

Combine policy, fiscal, enrollment, utilization, geographic, provider, and community information to identify hotspots, prioritize resources, and monitor whether implementation is protecting access.

How HMA helps: Data inventory and gap assessments, community indicator mapping, geographic hotspot analysis, dashboards, performance measures, and evaluation plans.

Questions Leaders Should Be Asking Now

HMA Has the Right Team

HMA brings deep Medicaid, healthcare, human services, financing, implementation, and community-system expertise to help clients translate policy change into operational readiness, protect access to care, strengthen safety-net infrastructure, and coordinate action across providers, agencies, local governments, and community partners.

Connect with HMA to discuss what the changing fiscal landscape means for your state, community, organization, providers, and residents.

HMA Conference to Open with State Leaders’ Insights on Healthcare Policy and Program Pressures

Read Blog

The Health Management Associates (HMA) Conference, US Healthcare 2026: Signals, Signs & Flashing Lights, will open October 6, 2026, with a discussion between two distinguished state officials—Bruce D. Greenstein, Secretary of the Louisiana Department of Health, and Stephen Cha, MD, Commissioner of the New Jersey Department of Human Services. Their conversation will frame the major policy, financial, and operational issues confronting the states and set the tone for deeper discussions throughout the conference about solutions being designed and implemented across the healthcare sector. 

Navigating a New Federal Landscape 

Mr. Greenstein, chief technology officer at the US Department of Health and Human Services (HHS) during the first Trump administration, and Dr. Cha, who has served in a range of roles at HHS and its agencies, bring both state and national perspectives to the discussion. Drawing on their experiences, they will discuss the challenges confronting public healthcare programs and the consequential choices before them. 

Those choices are becoming increasingly significant as federal policy changes reshape public healthcare coverage and financing. State leaders must protect access, sustain systems of care, and accept greater accountability for spending. Mr. Greenstein and Dr. Cha will explore the difficult tradeoffs behind their decisions, the potential consequences for health plans, providers, community organizations, and the people they serve. They will also address how leaders can manage fiscal and operational pressures without losing sight of quality and outcomes. 

In addition, the conversation will answer key questions about the future of state health and human services programs, including:  

  • How can artificial intelligence, data, and other technologies help states reduce administrative burden, improve oversight, and make programs more responsive?  
  • Where can states work more effectively with health plans, providers, technology companies, and other industry partners, and where is closer coordination with sister agencies essential to advancing shared goals? 

Mr. Greenstein and Dr. Cha will offer examples of how their states and their peers in other states have responded to these issues. 

Representing states with different political and policy environments, they also will explore where leaders across party lines are reaching similar conclusions—even when their strategies differ—and which practical challenges receive scant attention. Their exchange will consider how states should define success amid changing federal expectations, which outcomes matter most, and what early evidence can show whether a policy is working or health outcomes are beginning to deteriorate. 

Michael O. Leavitt, former Utah Governor and US Secretary of HHS, and co-founder of Leavitt Partners, an HMA Company, will moderate the discussion, adding his state and federal expertise and knowledge to a timely conversation about governance, accountability, and value. 

The opening plenary session will take place Tuesday, October 6, from 8:30 to 9:30 a.m. in New Orleans, LA. 

Register today to join the conversation.

Ready to talk?