Insights

HMA Insights - Blog

or
or
Receive timely expert insights on topics you care about.

569 Results found.

CMS’s 2027 Medicare Advantage Proposed Rule Focuses on Outcomes and Competition

Read Blog

On November 28, 2025, the Centers for Medicare & Medicaid Services (CMS) released the Contract Year 2027 Policy and Technical Changes to the Medicare Advantage Program and Medicare Prescription Drug Benefit Program. Each annual rulemaking cycle offers CMS an opportunity to recalibrate program priorities.  

This proposed rule offers a road map for CMS’s vision for Medicare Advantage (MA) and Part D. Signaling how CMS leadership intends to shape the MA and Part D programs beyond 2027—prioritizing outcomes, streamlining operations, and inviting dialogue on modernization—the proposed rule reflects a strategic imprint on the program’s trajectory. The deadline to submit comments is January 26, 2026. 

Given CMS’s goal of modernizing MA and Part D, plans, providers, and advocates should engage early to inform final policies. Health Management Associates (HMA) policy and actuarial experts, including Wakely and Leavitt Partners (both HMA companies), are analyzing and modeling the effect of the proposed changes. This article highlights some of the major policy updates that require near-term planning by states, Medicare Advantage plans, providers who serve MA beneficiaries, and their partners. 

Key Themes in the Proposed Rule 

Requests for Information 

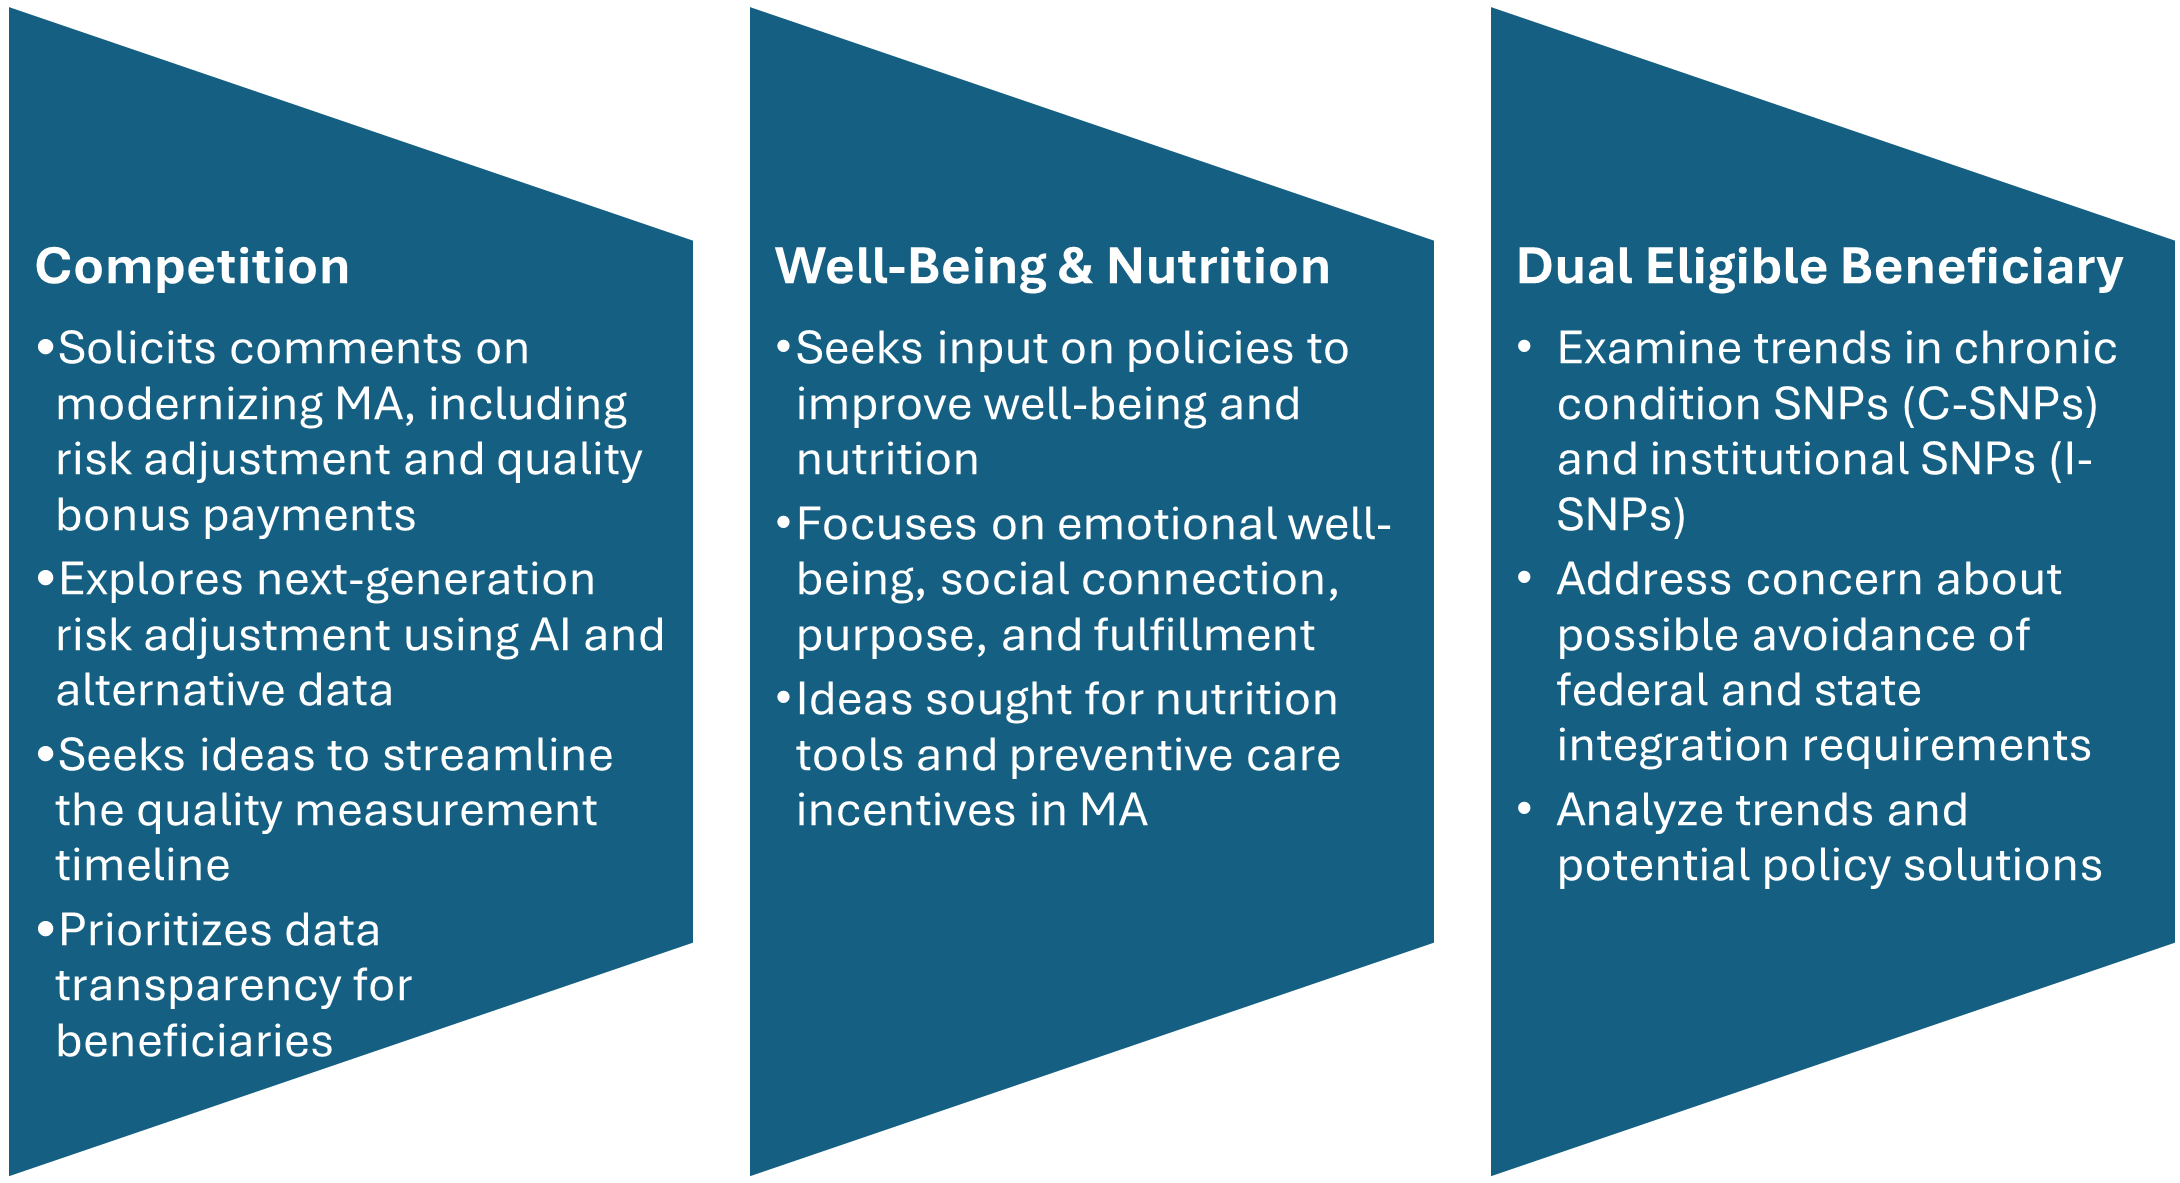
CMS includes three significant requests for information (RFIs) and highlights additional opportunities to provide input on approaches to reduce administrative burden throughout the program. CMS’s modernization RFI focuses on financing and other strategies to support beneficiaries with plan selection. In addition, CMS seeks input on emerging trends in MA special needs plans (SNPs), citing concerns about rapid growth and potential program integrity issues. Consistent with the departmentwide priorities, the RFI also delves into potential strategies for plans to address nutrition and wellness benefits for MA enrollees. 

Figure 1. RFIs Signaling New Policy Directions 
Star Ratings Overhaul: Refocusing on Outcomes and Experience

CMS proposes significant changes to the Star Ratings system, which influences plan bonuses and consumer choice. The changes increase the focus on clinical care, outcomes, and patient experience of care measures where performance is not topped out and align with universal foundation of measures. 

  • Health Equity Index Rollback: Rather than implement the previously planned Excellent Health Outcomes for All reward (formerly Health Equity Index) for 2027, the agency will continue using the historical reward factor that incentivizes consistently high performance across all measures. 
  • Measure Streamlining: Twelve process-heavy or administrative measures will be removed. 
  • Behavioral Health: A new measure for depression screening and follow-up will be introduced for the 2027 measurement year, with integration into Star Ratings by 2029.  

Why It Matters: Removing these measures continues the shift away from administrative compliance, easing burden while strengthening quality incentives. 

Medicare and Medicaid Dual Eligible SNPs and Integration 

CMS is proposing several changes to improve how Medicare Advantage plans serve people who qualify for both Medicare and Medicaid (dual-eligible beneficiaries): 

  • Starting in calendar year (CY) 2027, CMS proposes to allow D-SNPs and I-SNPs two opportunities to change to their model of care (MOC)—the framework for how they coordinate care. These windows would be January 1 through March 31 and October 1 through December 31. 
  • When beneficiaries are automatically moved (i.e., passively enrolled) from one integrated D-SNP to another, CMS will no longer require the new plan’s provider network to closely match the old plan’s network. Instead, the new plan must ensure that all incoming members receive uninterrupted care for at least 120 days (up from 90 days), helping prevent gaps in treatment. 
  • In states where dually eligible individuals are explicitly carved out from or not required to enroll in Medicaid managed care, CMS proposes to let highly integrated dual eligible special needs plan (HIDE SNP) continue to enroll full-benefit, dual-eligible (FBDE) individuals in the same service area, even if those individuals are in Medicaid fee-for-service. This change is intended to maintain coverage and simplify enrollment for these beneficiaries. 

Why It Matters: While the proposed changes revise broader policies, the updates could have significant effects on D-SNP and MA integration. These changes also could shape states’ decisions regarding their integration policies. Plans should continue to monitor these developments. 

Other Notable Changes  

CMS proposes a new special enrollment period (SEP) for beneficiaries when their providers leave a plan’s network, eliminating the requirement that CMS deem the change “significant.” The intent of this change is to preserve continuity of care and ease the burden of beneficiaries switching plans. In addition, CMS plans to codify SEP policies for greater consistency. 

The proposed rule also calls for the following: 

  • Codifying multiyear changes stemming from the Inflation Reduction Act, including elimination of the coverage gap phase 
  • Lowering annual out-of-pocket thresholds and removal of cost sharing in catastrophic coverage 
  • Transitioning to the Manufacturer Discount Program and updating true out-of-pocket (TrOOP) calculations 
  • Clarifying specialty-tier drugs and subsidy structures 

As a result, plans will have updated financial responsibilities. 

Connect With Us 

As CMS sets a new course for Medicare Advantage and Part D, organizations face both opportunities and challenges in adapting to these changes. HMA brings deep expertise in Medicare policy, actuarial modeling, and operational strategy. Our team—including experts from Wakely and Leavitt Partners—can help plans, providers, and stakeholders interpret the proposed rule, assess its impact, and develop actionable strategies for compliance and competitive positioning. 

Whether you need data-driven analysis, scenario modeling, or hands-on support preparing for implementation, HMA is ready to partner with you to navigate the evolving Medicare landscape and achieve your goals. Contact our experts below to discuss your questions and how HMA can help.
Beyond Compliance: Turning Medicaid Requirements into Stronger State Programs

Read Blog

Key Insights from the 2026 NAMD Fall Conference and What They Mean for Your Organization 

Medicaid leaders have never had the luxury of focusing on one issue at a time, but even by their standards, the current environment is unusually demanding. 

Health Management Associates (HMA) leaders attended the National Association of Medicaid Directors (NAMD) Fall Conference, October 21-23, 2026, during which federal and state leaders shared their priorities and implementation plans. Several themes stood out: 1) preparing for community engagement requirements, 2) strengthening program integrity, 3) adapting to major changes in Medicaid financing, 4) demonstrating value and accountability in managed care, and 5) improving quality and outcomes for Medicaid enrollees. 

These priorities are arriving alongside revisions to Section 1115 demonstration policy, budget pressures, and, in many states, leadership transitions. Many also reflect long-standing Medicaid challenges, including fragmented data, complex eligibility processes, uneven coordination across agencies, and difficulty connecting payment to outcomes. The insights below highlight how the work in progress can also build the capabilities that Medicaid programs will need in 2027 and beyond. 

What We Heard at NAMD 

Community Engagement Implementation Can Build Lasting Infrastructure 

Community engagement implementation was among the most prominent topics discussed at the conference, highlighting the scale of the work ahead for states and partners. Although the community engagement requirement is an eligibility policy, it touches nearly every part of the Medicaid enterprise, including: verifying eligibility and exemptions, using data from other programs, updating systems and workflows, communicating with beneficiaries, and defining roles for managed care plans, providers, workforce agencies, and community organizations. A process that looks straightforward in policy can still create significant burdens for members and the organizations that support them. In HMA’s work with states, much of the effort goes into connecting policy choices to the realities of data, systems, budgets, and the member experience. 

What it means for states and Medicaid partners 

Many implementation investments can deliver value well beyond what is prescribed in the requirement itself. Integrating Medicaid and workforce data can streamline verification now and support other cross-program initiatives later. Clear beneficiary notices can improve renewals, and operational dashboards can give leaders early visibility into enrollment disruptions, processing backlogs, and disparities. States and partners that approach implementation strategically can build capabilities that outlast any single federal mandate. 

Program Integrity Works Best When It Is Built into the Program 

Fraud, waste, and abuse is receiving heightened attention as federal and state leaders focus on payment accuracy, provider and vendor oversight, and the stewardship of public dollars. Medicaid leaders emphasized that the strategic value of program integrity extends well beyond audit and recovery, spanning finance, eligibility, provider oversight, analytics, operations, technology, compliance, and executive decision-making. 

Federal officials also signaled a commitment to shift from reactive enforcement to prevention, encouraging states to bring solutions forward and share what they are learning. The challenge, however, is balancing closer scrutiny with protecting access in services where it is already fragile, including behavioral health, personal care services, nonemergency medical transportation, and applied behavior analysis. 

What it means for states and Medicaid partners 

As states redesign processes and programs, program integrity is most effective when it is embedded in the design from the outset, rather than added later as another layer of oversight. Furthermore, collaboration across states is already driving changes in state approaches. For example, states are increasingly flagging provider enrollment concerns and sharing that information with one another. Clear documentation, robust data, provider education, well-designed payment controls, and meaningful monitoring can reduce improper payments while revealing where policies produce unintended consequences or where services are not reaching members. 

Managed Care Value Has to Be Defined Before It Can Be Demonstrated 

Discussions at NAMD were candid that managed care has yet to is not yet deliver its full potential, partly because the data needed to show that care is truly being managed are often incomplete. Rather than questioning whether to keep managed care, Centers for Medicare & Medicaid Services (CMS) officials encouraged states leaders to focus on accountability, which also requires reliable encounter data. 

Health plans are increasingly expected to demonstrate value beyond managing benefits and financial risk, whether through better access, fewer avoidable hospitalizations, improved maternal health, more effective behavioral healthcare, a better member experience, or lower total cost. What plans can realistically deliver, however, depends on reimbursement levels, financial risk, incentives, available data, partner capabilities, and the time needed to show results, a point that also came through clearly at HMA’s 2026 National Conference. 

What it means for states and Medicaid partners 

Adding performance measures to managed care contracts is rarely enough on its own. States get further when procurements start with a clear answer to what the state is buying, rate setting is grounded in transparent data, and contracts focus on the outcomes the state most wants to improve. States can then decide what needs to change in payment, what data will show progress, and whether plans, providers, and other partners have the resources, information, incentives, and time to influence results. 

Better Outcomes Depend on Doing Fewer Things Well 

Quality discussions at NAMD centered on the need for greater focus, as states use 250 unique state-designed quality measures, and 38 states have signed on to CMS’s national Medicaid Quality Pledge. Trying to do everything accomplishes little, especially as burden flows from states to health plans, providers, and vendors. The priority is the conditions driving much of Medicaid spending, including hypertension, diabetes, behavioral health, and maternal health, and whether investments are keeping people healthy and out of the hospital. 

What it means for states and Medicaid partners 

States that concentrate measures, data collection, and investments on the outcomes that matter most can reduce burden across the system. Federal officials want data treated as core infrastructure and greater standardization so states have the information needed to develop sound policy. 

Partnerships Depend on Clearly Defined Roles 

Partnership, a hallmark of NAMD meetings, was again a defining theme this year. Medicaid agencies cannot achieve their goals alone, and leaders were focused on practical, shared solutions that deliver better outcomes for members. Community engagement, for example, may require coordination with state labor and workforce agencies, Supplemental Nutrition Assistance Program (SNAP) and Temporary Assistance for Needy Families (TANF) programs, community colleges, employers, community-based organizations, providers, and managed care plans, each with its own systems, responsibilities, and funding streams. 

What it means for states and Medicaid partners 

Tighter budgets make it more important to be clear about what each partner contributes. For states, health plans, and providers, reaching that understanding requires honest decisions about which capabilities to keep in-house, where a partner is better positioned to deliver, and how those roles fit together around shared goals. 

Looking Ahead: Using Today’s Requirements to Build for Tomorrow 

Meeting new federal requirements on time remains essential, but how states meet them will determine whether the work creates lasting value. Decisions made early in implementation will shape those results, and they carry added weight as administrations and agency leadership change. 

Work on the community engagement requirement will continue well beyond the January 2027 effective date as states, health plans, providers, and community partners monitor results and adapt to evolving federal policy. HMA’s interdisciplinary team brings policy, actuarial, operations, data, and technology expertise to each stage of that work. Our experts help organizations design workable verification processes, model enrollment and financial impacts, build data and program integrity safeguards, align managed care contracts and partner roles, and track outcomes over time. Connect with our experts to discuss your organization’s priorities. 

Minnesota’s Medicaid Balancing Act: Protecting Coverage While Fighting Fraud

Read Blog

Minnesota’s efforts to keep people covered while addressing Medicaid fraud were central to discussions at the September 30, 2026, Health Policy Conference in Minneapolis. Hosted by State of Reform, an HMA company, the conference brought together lawmakers, state officials, providers, community-based organizations, and policy experts to discuss the healthcare landscape. Specific topics covered included how to respond to the 2025 budget reconciliation legislation (commonly referred to as OBBBA or the Working Families Tax Cut Act [WFTCA]) and address fraud, waste, and abuse (FWA) without disrupting coverage or weakening provider capacity. 

Particularly for the Medicaid program, discussions connected immediate implementation decisions with how healthcare leaders could introduce more accountability into the program without making healthcare harder to access or weakening an already strained delivery system. 

Key Discussions: Coverage, Oversight, and Continuity of Care 

Federal Medicaid changes put pressure on coverage continuity. 

An estimated 140,000 Minnesotans could lose Medicaid coverage as provisions of the WFTCA take effect, including work requirements, six-month redeterminations, and cost-sharing for the expansion population, and coverage changes affecting some lawfully present immigrants. State lawmakers, including Sen. Alice Mann, Vice Chair of the Health & Human Services Committee, and Rep. Mohamud Noor, Co-Chair of Human Services Finance & Policy, shared their concerns about the coverage losses and steps they are taking to soften the effects; for example, requiring a one-month lookback period for the work requirements instead of three. 

Discussions at the conference also made clear that Minnesota leaders are focused on how people experience Medicaid changes in practice. Representative Noor emphasized the need for practical support, including guidance around work requirements, help for people who qualify for emergency medical assistance, and attention to people in long-term care. He also stressed the importance of keeping counties involved because they will experience much of the operational and financial impact of federal policy changes. 

In Minnesota, the state can set policy and build eligibility systems, but counties, health plans, providers, and community organizations are the ones that recognize when someone is at risk of losing coverage. Former Minnesota Department of Human Services Deputy Commissioner Chuck Johnson suggested that, as Minnesota implements federally required eligibility changes, it should also think about redesigning the eligibility process itself and using the federally-driven eligibility changes as an opportunity to make the state’s system easier to navigate. 

Program Integrity Activities Earlier 

Minnesota’s Medicaid fraud concerns have brought greater scrutiny to how the state manages providers and protects public funds. In December 2025, the Centers for Medicare & Medicaid Services (CMS) requested a corrective action plan (CAP) to address concerns regarding FWA within the state’s public benefits programs. The Minnesota Department of Human Services (DHS) submitted a CAP on December 31, 2025 and CMS approved a revised version of the plan March 19, 2026. The state’s response has included revalidating high-risk Medicaid providers, establishing a moratorium on new service providers in certain high-risk areas, creating a public program integrity dashboard, and discontinuing the Housing Stabilization Services benefit. Minnesota also secured funding to expand DHS’s program integrity workforce by more than 400 positions over two years. 

Speakers at the conference agreed that addressing those problems also means helping providers build stronger operations. Mr. Johnson acknowledged both the fraud that needs to be stopped and the politically charged perceptions surrounding it. He also encouraged offering support to providers so they can improve integrity within their own operations. 

That emphasis on prevention carried into the discussion with Health Management Associates (HMA) Associate Principal Jen Bridgeforth and Regional Director Clint Eisenhower. Both focused on the work that happens before an improper payment is made—from everyday compliance practices within provider organizations to the way states design programs. 

Written compliance procedures, staff with the right expertise, and technology that supports oversight can help organizations identify risks earlier. Ms. Bridgeforth emphasized that responsibility extends across an organization. Those safeguards take time and money, she noted, but the administrative burden and costs increase substantially when audits uncover fraud. Mr. Eisenhower connected that day-to-day work to policy decisions, adding that program integrity needs a place in program design. 

Speakers also emphasized that Minnesota’s anti-fraud efforts should account for what happens to people receiving care, noting, for example, ongoing behavioral health provider capacity gaps and the risk of deepening access challenges. This theme of involving providers in discussions extended into conversations about medical respite, homelessness, and complex discharge where problems have emerged when healthcare and community systems are misaligned. 

The Bottom Line: Practical Solutions, Collaboration, and Shared Responsibility 

The key takeaway from the conference was that Minnesota’s healthcare coverage and delivery system challenges require practical solutions. These efforts should focus on: 1) cross-sector approaches to helping people retain Medicaid coverage, 2) a more systematic statewide approach to program integrity, and 3) new initiatives to improve complex discharge for children and adults, which could provide lessons for broader policy change. 

Another theme that emerged across sessions was the need for shared responsibility in designing, implementing, and sustaining responses to changes and pressures stemming from the WFTCA, as well as other pressures on the healthcare system. This coordinated response calls for respecting each other’s unique roles and perspectives while recognizing the interconnected nature of the work. For example, Minnesota counties will need support from the state as Medicaid eligibility requirements change. Health plans, providers, and community organizations can reach people before administrative issues turn into coverage losses. State program integrity officials can work with providers to identify vulnerabilities upstream instead of relying primarily on audits after payments have been made. Hospitals, behavioral health providers, housing organizations, and community partners can build clearer pathways for people who otherwise become caught between systems. 

Looking Ahead 

If you are looking for strategies and solutions to address urgent healthcare policy and operational challenges, HMA experts are available to help you identify practical paths forward. 

Through the HMA National Conference, State of Reform partnership events, and other HMA convenings across the country, we connect state leaders, providers, health plans, and community stakeholders to share insights, elevate lessons, and advance solutions. Join us at one of our next SOR events—November 10, 2026, in Raleigh, NC, or November 17, 2026, in Chicago, IL—or explore additional opportunities to engage with HMA and access the full schedule of conferences and resources. 

State of Reform develops its conference agendas through collaboration with HMA subject matter experts/market leads and stakeholders across the public and private sectors, including state officials, community-based organizations, providers, payers, and more. 

What Comes After 988? A New National Roadmap for Behavioral Health Crisis Care

Read Blog

Why HMA and NAMI Are Building the Next Chapter of Crisis Care

Key Takeaways

  • In October 2026, the National Collaborative for Crisis Systems Innovation, a partnership between HMA and NAMI, released its Strategic Plan & Implementation Roadmap.
  • The plan focuses on four priorities (Awareness, Access, Capacity, and Quality) to strengthen the 988 Suicide & Crisis Lifeline and the full behavioral health crisis continuum through early 2028.
  • Launched in May 2026, the Collaborative brings together advocates, government leaders, philanthropic organizations, providers, people with lived experience, families, researchers, and technical experts to turn crisis policy into practice.

When the 988 Suicide & Crisis Lifeline launched in July 2022, I had the privilege of serving as the inaugural director of the 988 & Behavioral Health Crisis Coordinating Office at SAMHSA. I saw firsthand what three simple digits could mean for someone on the worst day of their life. I also learned something every crisis leader eventually comes to understand: A number is only as strong as the system behind it.

Four years later, communities across the country are still working to build that system. States and localities face inconsistent access to robust crisis lines, workforce shortages, financing challenges, gaps in coordination across systems, and uncertainty around policy, leadership, and funding transitions. Too many people still can’t get the full continuum of crisis care when they need it most.

That’s why I’m so proud that HMA and NAMI joined forces in May 2026 to launch the National Collaborative for Crisis Systems Innovation. The Collaborative is a national hub for alignment, learning, and action in behavioral health crisis care. It gives partners a shared forum to identify common priorities, elevate what’s working, and turn vision into practice.

Our mission is clear: Ensure that every person experiencing a behavioral health crisis can access timely, compassionate, and effective support by advancing connected, sustainable crisis systems and driving collaboration and innovation across the full crisis continuum.

What Are the Four Priorities of the Crisis Care Strategic Plan?

This month, the Collaborative released its Strategic Plan & Implementation Roadmap, which lays out how we’ll move from concept to action through early 2028. The plan is built around four mutually reinforcing priorities, namely:

  • Awareness: People know what to do and where to turn in a crisis.
  • Access: The system people reach out to is fully available in every community.
  • Capacity: There are enough crisis responders to help every person in need.
  • Quality: Every person gets quality care, no matter how they enter the crisis system.

None of these priorities stands on their own. Awareness means little if help isn’t available when someone calls, texts, or chats. Access falls short without a workforce to answer. And capacity only matters if people receive high-quality care. Moving all four forward together is how we build a crisis system that people can trust.

What Is HMA’s Role in Strengthening Crisis Systems?

At HMA, our behavioral health team works alongside state agencies, communities, providers, and payers to turn crisis policy into services people can actually reach. Through the Collaborative, we bring that on-the-ground perspective together with NAMI’s deep connection to people with lived experience and their families. Together, we convene advocates, government leaders, philanthropic organizations, providers, people with lived experience, families, researchers, and technical experts, so the people closest to the work help shape where it goes next.

Our goal is to provide a stable, trusted platform for shared learning, cross-sector coordination, and forward-looking leadership. Over the long term, that means boosting national awareness of the 988 Lifeline, catalyzing innovation, ensuring continuity through periods of change, and leading with consistency. That last point matters now more than ever. Crisis systems can’t afford to start over every time leadership, policy, or funding shifts.

The Work Continues

Helping bring 988 to communities across the country was one of the greatest honors of my career. But 988 was never meant to be the finish line. It was the starting point for a crisis care system that is coordinated, equitable, sustainable, and trusted. I’m grateful to our partners at NAMI and to my HMA colleagues for carrying this work forward. The work continues, and I hope you’ll join us.

Frequently Asked Questions

What is the National Collaborative for Crisis Systems Innovation?

The National Collaborative for Crisis Systems Innovation is a national hub for alignment, learning, and action in behavioral health crisis care. HMA and NAMI launched it in May 2026 to help partners identify common priorities, elevate what’s working, and turn vision into practice.

What does the Strategic Plan & Implementation Roadmap include?

The plan outlines the Collaborative’s vision, mission, priorities, and early focus areas, and shows how the Collaborative will move from concept to action through early 2028. It is built around four mutually reinforcing priorities: Awareness, Access, Capacity, and Quality.

How does the plan support the 988 Suicide & Crisis Lifeline?

The 988 Suicide & Crisis Lifeline made crisis support easier to locate, but a number is only as strong as the system behind it. The plan is designed to boost national awareness of 988 and strengthen access, workforce capacity, and quality across the full crisis continuum, so people get effective care no matter how they enter the crisis system.

Who participates in the Collaborative?

The Collaborative convenes advocates, government leaders, philanthropic organizations, providers, people with lived experience, families, researchers, and technical experts, so the people closest to the work help shape where crisis care goes next.

How does HMA help states and communities strengthen crisis systems?

HMA’s behavioral health team works alongside state agencies, communities, providers, and payers to turn crisis policy into services people can actually reach. Through the Collaborative, HMA provides a stable, trusted platform for shared learning, cross-sector coordination, and continuity through periods of leadership, policy, or funding change.

Learn More

Download the National Collaborative for Crisis Systems Innovation Strategic Plan & Implementation Roadmap to explore the Collaborative’s vision, mission, priorities, and early focus areas through early 2028. For more information, visit crisisinnovation.org.

To talk with HMA about strengthening crisis systems in your state or community, connect with our behavioral health team.

By Monica Johnson, MA, LPC, Managing Director, Health Management Associates

2027 Medicare Advantage Star Ratings: Quality Bonus Payment Impacts

Read Blog

The Centers for Medicare & Medicaid Services (CMS) released the 2027 Medicare Advantage (MA) and Part D Star Ratings on October 8, 2026. CMS reported little change in the number of contracts earning at least 4 Stars and an increase in enrollment in higher-performing plans. Wakely Consulting Group, an HMA Company, found more year-over-year change than those figures suggest.  

Wakely’s new white paper, Stars Gone Wild: Summary of 2027 Medicare Advantage and Part D Star Ratings, examines how plan performance changed and what the 2027 results mean for Medicare Advantage (MA) organizations’ quality strategies and future quality bonus payments (QBPs).  

2027 Star Ratings: Rising Cut Points and Quality Bonus Payments 

Achieving 4 Stars has a direct financial implications for Medicare Advantage plans. Contracts rated at 4 Stars and higher receive a 5% increase in benchmark rates through the QBP. Even a small ratings change that moves a contract above or below that threshold can significantly affect payment. The 2027 Overall Star Ratings will determine QBPs for the 2028 payment year.  

Wakely found that plan performance in general improved between the measurement years underlying the 2026 and 2027 Star Ratings, but Star Rating cut points rose slightly faster. After adjusting for enrollment changes, crosswalks, and plan terminations, the enrollment-weighted average Overall Star Rating fell from 4.08 in 2026 to 4.01 in 2027. The share of enrollment in contracts rated at least 4 Stars also fell from 73.2% to 71.7%. 

CMS and Wakely present different perspectives on enrollment trends. CMS’s figures reflect enrollment at the time each year’s Star Ratings are published. Wakely’s year-over-year analysis uses updated enrollment information for both years and accounts for known plan crosswalks and terminations. Under Wakely’s approach, the 2026 baseline for enrollment in 4+ Star plans is approximately 73% versus approximately 67% in CMS’s published figures. Using that baseline, Wakely’s analysis shows a decline in 2027.  

The 2026 Star Ratings determine QBPs for the 2027 payment year. Using current enrollment information helps plans estimate how many members will be affected by the associated rate adjustments and how those changes will influence QBP revenue.  

Medicare Advantage Star Ratings Results by Insurer 

National averages mask large differences among insurers. 

Wakely examined the 10 largest parent organizations, which account for 27.8 million members (~ 80%) of MA-PD enrollment. Humana’s share of enrollment in 4+ Star contracts increased by 53% in 2026–2027. Much of that increase came from a single contract, which covers more than 2 million members and improved from 3.5 to 4 Stars. Kaiser maintained 100 percent of its membership in 4+ Star plans for the third consecutive year.  

Health Care Service Corporation’s enrollment in 4+ Star contracts declined by 47.6%. United and CVS each saw approximately 15% of their membership drop below the 4-Star threshold, representing roughly 2 million members combined.  

Special Needs Plans: Enrollment in 4+ Star Contracts Declines 

Wakely’s analysis of Special Needs Plans (SNPs) analysis covers more than 10.7 million members. The share of enrollment in 4+ Star SNP contracts fell from 78% in the 2026 Star Ratings to 55% in 2027, a 23% decline. Of the five largest SNP parent organizations, only Humana saw an increase. United, which has more than 3.7 million SNP enrollees, experienced a 27% decline in 4+ Star SNP contract enrollment.  

MA Star Ratings Trends by State 

Some states saw steep declines in enrollment among plans with higher ratings, whereas others saw large gains. Rhode Island, Louisiana, and Georgia had the largest declines in enrollment in 4+ Star contracts, while Montana, South Dakota, and North Dakota had the greatest increases. Among the states highlighted in Wakely’s paper, Rhode Island experienced the steepest decline, from 94.6% to 35.0%. South Dakota rose from 37.8% to 100%. These state-level differences show why national trends alone may tell plans little about what is changing in their own markets. 

Quality Improvement Strategies for Medicare Advantage Star Ratings 

Star Ratings connect the care members receive with the bonus funding plans can use to support benefits and other priorities. That makes it important to know whether investments in provider engagement and member outreach are closing gaps in care, improving outcomes, and helping plans perform better on the measures that drive their ratings.  

Health Management Associates (HMA) work on quality improvement and Wakely’s Star Ratings analysis reinforce the connection between care outcomes and financial decisions. Clinical, quality, member engagement, and provider strategy teams have developed an understanding of what members need; actuarial, data, and financial consultants help assess the results and financial implications. Together, they can use those findings to guide spending, set clear responsibility for improvement, and focus resources as rating standards and regulations change. 

Star Ratings Litigation and Potential Methodology Changes 

CMS recalculated ratings across the market following litigation over the 2026 ratings, including Clover Health’s challenge, but used the previously finalized measure set for 2027. Wakely estimates that measures representing approximately two-thirds of the program’s current weight remain subject to legal uncertainty.  

Wakely anticipates significant program changes, leaving plans to meet current requirements while preparing for shifts in measures and methodology, including those that could result from litigation.  

Medicare Advantage Star Ratings Support from HMA and Wakely 

Understanding what drives a plan’s Star Ratings is only part of the work. HMA and Wakely bring together actuarial analysis, risk adjustment, rate setting, quality strategy, payment policy, and competitive positioning to help plans turn those findings into an improvement strategy. 

Our integrated teams connect the clinical and operational work of improving quality with the financial and market decisions plans face. We support plans in their efforts to analyze performance and forecast payment impacts, set priorities, implement quality strategies, and track progress as rating standards change. 

For a closer look at the findings, read Wakely’s Stars Gone Wild: Summary of 2027 Medicare Advantage and Part D Star Ratings and join the November 5, 2026, Stars Gone Wild webinar for a discussion of the results and the policy and methodology changes ahead. 

Contact HMA and Wakely to discuss the factors that are driving your plan’s Star Ratings and how our teams can help improve performance, prepare for payment changes, and strengthen your competitive position. 

What the NDC-12 Transition Means for the US Healthcare Ecosystem

Read Blog

Key Takeaways on the 12-Digit NDC Transition from the September 2026 Quarterly Forum

The NDC Coordination and Implementation Forum is organized by the Leavitt Center for Alliances, an initiative of Leavitt Partners, an HMA Company, that develops and supports consensus-based alliances to address complex, cross-sector healthcare challenges.

On September 26, more than 350 industry leaders representing government, life sciences, health plans, providers, standards organizations, and technology partners came together at the first quarterly meeting to discuss how the healthcare ecosystem can prepare for the transition by the Food and Drug Administration (FDA) to a uniform 12-digit National Drug Code, or NDC-12. The change will affect manufacturers, distributors, pharmacies, providers, payers, technology companies, regulators, and other healthcare stakeholders.

Key takeaways from the Forum:

1. The transition will affect the entire healthcare ecosystem

The new NDC format will require updates across drug data, business systems, shared infrastructure, standards, barcodes, billing, reimbursement, surveillance, and supply chain processes. Organizations will need to understand how their work aligns with the timelines and dependencies of other stakeholders.

2. Dual operability will be a central implementation challenge

Organizations will need to simultaneously manage 10-digit, 11-digit, and 12-digit NDCs during the transition. This period of dual operability makes data mapping, system testing, historical-data management, and cross-sector coordination especially important.

3. The shared roadmap provides a common view of readiness

The NDC Forum’s ecosystem-wide roadmap tracks major milestones, dependencies, decision points, and readiness risks. It identifies foundational work beginning in 2026, with important milestones for standards, NDC conversion, FDA data systems, pharmacy and provider readiness, testing, and the planned go-live date of March 7, 2033.

4. Early action is essential

The forum emphasized that the implementation timeline is front-loaded. Impact assessments, ownership decisions, standards updates, data foundations, and system planning need to begin well before NDC-12 enters production.

5. Collaboration will drive successful implementation

The NDC Forum brings together stakeholders to share information, identify cross-sector risks, and coordinate execution. Short-duration “Strike Forces” will focus on issues such as roadmap validation, regulatory clarity, label-data alignment, post-2036 NDC-10 management, and UPC-A barcode replacement.

The NDC-12 transition is a multi-year effort that requires shared visibility, coordinated planning, and sustained participation across healthcare. Organizations can help shape the implementation by joining the NDC Forum and contributing their perspective.

Strike Force participation is available to NDC Forum members. By joining now, your organization can bring its perspective directly into these discussions, learn how other stakeholders are approaching the same challenges, and help shape solutions before implementation decisions become difficult or costly to change.

Become a member and get involved: https://ndcforum.org/get-involved

Five Takeaways on Medicaid, AI, Financial Sustainability, and Program Integrity from HMA’s 2026 National Conference

Read Blog

From financial sustainability and program integrity to value, technology, and cross-sector collaboration, healthcare leaders are being challenged to rethink how their organizations operate. 

Healthcare leaders are entering a period in which the decisions they make now will shape their organizations for years to come. During the Health Management Associates (HMA) 2026 National Conference, US Healthcare 2026: Signals, Signs & Flashing Lights, conversations repeatedly touched on a common question: How do healthcare organizations adapt their strategies and operating models to deliver better outcomes in a more constrained environment? 

Across discussions on financial sustainability, program integrity, technology, AI, access, and the future of public programs, a clear imperative emerged: Organizations face more difficult choices about where to invest, how to define and demonstrate value, and how to work across traditional silos. The implications extend well beyond any one program or sector. 

Five takeaways stand out for healthcare leaders looking ahead.

1. Financial sustainability requires organizations to get much clearer about where they create value

Financial pressure was an ongoing topic of discussion at the conference, though conversations diverged from the traditional focus on managing tighter budgets. Instead, leaders are reconsidering where their organizations can have the greatest impact and the expertise they need to protect and strengthen, and where partnerships can improve effectiveness of service delivery. 

The conversation about sustaining access to care brought that challenge into sharp focus. Safety-net providers are confronting growing needs while also reassessing how far they can stretch their existing resources. Panelists emphasized the need for organizations to stay anchored to their mission, continually assess priorities and resources, and resist the temptation to pursue every potential opportunity or funding stream. Partnerships with government, philanthropy, schools, community organizations, and other healthcare organizations can help extend reach while allowing organizations to concentrate resources where they are uniquely positioned to deliver. 

What healthcare leaders should be thinking about

The organizations that emerge stronger will be clear about their mission and where they create distinctive value. Executive teams should be asking whether their resources, partnership, and operating models reflect those priorities.

That shift will require difficult decisions. Sustainability cannot be achieved by cutting costs indiscriminately or expecting existing models to absorb additional pressure indefinitely. Organizations will need a clearer view of the services and capabilities they must preserve, where operational models need to change, and which investments can produce meaningful results for the communities they serve.

2. Program integrity is moving closer to the center of healthcare operations

Program integrity is receiving heightened attention, particularly as public programs face greater scrutiny over how healthcare dollars are spent. Federal and state leaders highlighted the tension healthcare leaders must manage, specifically, improving stewardship of public dollars while preserving access to necessary services and avoiding undue burden on legitimate providers. They also highlighted the importance of provider management, including using data analytics to determine utilization and payment, quality, and member outcomes—all of which can help organizations identify problems earlier and make better decisions about where intervention is warranted. 

Across the sessions, healthcare leaders spoke of program integrity as a component of operations, signaling a movement away from the historical framing of program integrity as a stand-alone function. The shift creates an opportunity to connect program integrity more deliberately with quality and value.

 What leaders should be thinking about

Expect program integrity to become more integrated with operational and financial strategy. Organizations that strengthen data, governance, provider oversight, and cross-functional coordination now will be better positioned as federal and state expectations continue to evolve.

3. Managed care entities must create value across the healthcare ecosystem

Expectations for managed care delivery systems are changing, particularly for Medicaid managed care entities. Conversations throughout the conference centered on how to achieve value. Speakers discussed concepts for a financial framework that gives plans and their partners enough time, resources, and flexibility to demonstrate value. The number of years available to show results, the structure of incentives, reimbursement levels, and the allocation of financial risk all shape what plans, providers, and community partners can realistically deliver. As expectations rise, states and managed care entities will need to align these factors more deliberately so that accountability for outcomes is matched by the conditions needed to produce them. 

Plans need a clear understanding of where each partner can make a meaningful contribution, whether by strengthening primary and specialty care, addressing behavioral health and social needs, improving data exchange, or reaching members who remain disconnected from care. The value comes from how well those capabilities work together around shared priorities.

What healthcare leaders should be thinking about

Medicaid managed care leaders should not wait for the next contract cycle to determine whether their financial and partnership models can deliver the outcomes now expected of them. They should identify where incentives, reimbursement, risk, timelines, or data constraints are working against shared goals and address those gaps with states and partners.  

4. Technology strategy needs to start with the problem, not the tool

Throughout the AI preconference session and the main event, healthcare organizations grappled with the immediate challenge of deciding where AI adds value and whether they are prepared to use it responsibly. 

The AI preconference discussion focused on a framework to support key decisions and the need to put readiness before adoption. Core components of the readiness framework include reliable data, workforce preparation, engaged leadership, governance, and clear operational processes. Both technology experts and clinical leaders encouraged organizations to prioritize practical, high-value use cases rather than implementing AI broadly for its own sake. 

And, as the conference discussion of the Office of the National Coordinator’s Trusted Exchange Framework and Common Agreement (TEFCA) and the Centers for Medicare & Medicaid Services (CMS) Health Tech Ecosystem demonstrated, simply connecting more data is too little. The next step is making that information usable in ways that improve decisions, coordination, and care without creating additional work.

What leaders should be thinking about

Before making the next technology investment, organizations should be clear about the problems they are trying to solve. The strongest use cases will connect technology to a defined operational or clinical need, supported by the governance, data workforce, and measurement needed to determine whether is is actually working.  

5. Some of the biggest opportunities are emerging between programs, sectors, and traditional lines of business

Healthcare may be organized around programs and sectors, but the problems leaders are trying to solve rarely respect those boundaries. 

That was particularly evident in conversations about behavioral health. People with complex needs often interact with not only healthcare providers, but also housing, social services, and criminal justice systems. Better outcomes, therefore, depend in part on connecting services and organizations that historically have operated separately. 

The same concept surfaced during the discussion about sustaining access. Speakers challenged organizations to move beyond a siloed mindset and focus more broadly on what patients and communities need while using partnerships to extend their reach. 

A conversation with leaders from the US Department of Veterans Affairs (VA) offered another perspective on this opportunity. The VA is taking steps to make its healthcare data more actionable and to ensure its Community Care program draws on core capabilities of industry and to ensures its approach is informed by both Medicare and Medicaid. 

There is an important strategic implication here. Expertise developed in Medicaid managed care, value-based purchasing, population health, provider networks, data analytics, program integrity, interoperability, and implementation does not necessarily have to remain within the business or program where it originated. Leaders have an opportunity to look across the healthcare ecosystem for proven approaches and consider where those capabilities can solve problems in new settings. 

What healthcare leaders should be thinking about

The next opportunity may site outside the line of business in which an organization has traditionally operated. Leaders who can identify where their expertise translates, and where partners bring complementary capabilities, may find new ways to address longstanding challenges.

From Responding to Change to Shaping What Comes Next 

The discussions at HMA’s 2026 National Conference point to a healthcare environment that is entering a different phase. Understanding policy change remains essential. The work ahead, however, needs to be strategic and transformational. 

The leaders best positioned for what comes next will know where their organizations create value, be able to demonstrate it, and recognize when bringing that expertise into a new partnership, program, or market can be transformative. 

HMA can help leaders move this work forward by bringing the right partners to the table and connecting strategy with execution. As a convener and strategic advisor, HMA combines market and policy expertise with data analysis and technology capabilities to help organizations assess changing expectations, align financial and operating models, and build partnerships that deliver measurable value. 

These conversations continue in 2026 through HMA’s State of Reform events, where policymakers, health plans, providers, community organizations, and other stakeholders come together to examine state and local market realities and develop practical solutions. HMA’s next national conference will be held October 12-14, 2027, in Nashville, TN. 

What CMS’s New Medicaid Quality Pledge Means for the Future of Measurement

Read Blog

The Centers for Medicare & Medicaid Services (CMS) has launched the Investing in Health Outcomes initiative with a founding group of 37 states, establishing a voluntary Medicaid Quality Pledge intended to shift Medicaid and Children’s Health Insurance Program (CHIP) quality strategy toward outcomes that matter to beneficiaries. The initiative is an effort to redirect policy, tools, data, and improvement resources away from an expansive inventory of process-oriented requirements and toward a more focused system that can demonstrate progress in prevention, chronic disease management, and behavioral health. 

That direction matters now because Medicaid agencies, managed care entities, providers, and vendors are being asked to improve outcomes while managing extensive and often duplicative performance reporting expectations. CMS reported that its review of managed care programs in 42 states identified approximately 450 reporting requirements corresponding to roughly 260 unique quality measures, many focused on processes and utilization. A smaller, more coherent portfolio could reduce administrative burden, but only if the measures selected are meaningful, the data are trusted, and accountability is built into the policy and contractual structures that drive delivery-system behavior. 

Through this voluntary pledge, CMS is encouraging, rather than requiring participating states to apply the four principles, as they develop health outcome targets and consider outcomes-oriented measures for state quality strategies and upcoming procurements. A disciplined, multiyear approach focused on a limited number of priorities is therefore best understood as an implementation strategy that states can use to make the pledge actionable and establish a credible performance trajectory. 

To learn more about the four principles for an outcome-focused Medicaid quality system access the full report. 

CMS Marketplace Anti-Fraud Actions: Financial and Strategic Implications for ACA Health Insurers

Read Blog

Program integrity has become an urgent, administration-wide healthcare priority, placing the Affordable Care Act (ACA) Marketplace under heightened scrutiny. On September 22, 2026, the Centers for Medicare & Medicaid Services (CMS) announced Federal Marketplace anti-fraud actions with immediate operational and financial implications for insurers. 

This week, actuaries from Wakely Consulting Group, an HMA company, examine how Marketplace disenrollment actions could affect health insurers in 2026 and beyond across enrollment, morbidity, risk adjustment, financial reporting, operations, distribution strategy, and future pricing. 

CMS Marketplace Anti-Fraud Actions and Unauthorized Enrollment Cancellations 

CMS’s three-part program integrity strategy focuses on preventing fraudulent and improper enrollments, removing confirmed unauthorized enrollments, and enforcing Marketplace requirements for agents and brokers. The agency also established a Federal Marketplace anti-fraud coordination group comprising leaders from CMS and the US Department of Health and Human Services (HHS) to direct these efforts. 

CMS reported canceling approximately 315,000 enrollments covering more than 760,000 individuals after determining that the coverage was unauthorized. The agency expects approximately $2.2 billion in advance payments of the premium tax credit (APTC) to be returned and will continue working with insurers to identify additional cases, prevent improper subsidy payments, and recoup prior payments. 

This action follows a June 2026 report from the HHS Office of the Assistant Secretary for Planning and Evaluation, which identified approximately 1 million highly suspicious agent- and broker-assisted HealthCare.gov enrollments involving applications without a Social Security number and members paying no premium. 

Although the absence of a Social Security number does not independently establish fraud, the September announcement sends a strong signal about CMS’s willingness to cancel enrollments confirmed as unauthorized. 

Financial and Operational Implications for ACA Marketplace Insurers 

Enrollment Losses and Morbidity Risk for ACA Marketplace Plans 

In their August 2026 white paper, Implications for Potential Marketplace Unauthorized Enrollment Actions, actuaries from Wakely noted that while the overall enrollment reduction is known, its distribution across issuers and markets is not publicly available. If canceled members are disproportionately healthy or had limited healthcare utilization, their removal could increase average claims among the remaining population. For example, if non-utilizers represented 10 percent of an issuer’s enrollment, removing them would increase average claims per member per month by approximately 10 percent, assuming no other changes. 

ACA Risk Adjustment Implications of Marketplace Disenrollments 

Changes in enrollment and morbidity could materially affect ACA risk adjustment transfers, but the results will vary according to each issuer’s concentration of confirmed or potentially unauthorized enrollment. Issuers with greater exposure to canceled enrollment could see more favorable risk adjustment results even as average claim costs increase. Those transfers may not fully offset deterioration in the remaining risk pool, which underscores the need for plan- and state-specific analysis. 

APTC Recoupment and Financial Reporting Considerations for Insurers 

The timing and process to recoup approximately $2.2 billion in APTCs has near-term financial reporting considerations. Issuers should evaluate potential effects on: 

  • Premium and APTC accruals 
  • Risk adjustment transfer accruals 
  • Per member claims cost estimates 
  • Premium deficiency reserve considerations 

According to CMS, the cancellations announced in September 2026 will be applied retroactively to original effective dates. The full effect of this heightened scrutiny, however, will depend on how CMS approaches recoupment and how quickly issuers process enrollment and financial adjustments.  

Issuers may also incur near-term costs associated with identifying and investigating suspicious enrollments, reconciling records with CMS, processing cancellations, adjusting revenue accruals, supporting affected consumers, and updating broker oversight. Lower enrollment also leaves fewer premium dollars available to cover fixed administrative expenses. 

How CMS Disenrollments Could Affect Future Marketplace Premiums 

As 2027 premiums are finalized, issuers will need to consider enrollment and morbidity shifts for 2028 prices. Insurers with established monitoring and projection processes will be better positioned to assess new CMS information and adjust forecasts as policy and enforcement evolve for 2026 and 2027. 

CMS Broker Enforcement and Marketplace Distribution Risks 

In addition to strengthening oversight of enrollment data, CMS has intensified enforcement of agent and broker requirements. Since January 2026, the agency has sent termination notices to more than 200 noncompliant agents and brokers and issued 569 notices of intent to terminate Exchange Agreements associated with 2026 applications that lacked identifying applicant information. Issuers should assess concentration by broker, monitor enrollment quality, and consider how enforcement may affect acquisition channels, member mix, and future growth. 

Market-Level Variation in Marketplace Disenrollment Risk 

The effects of CMS’s actions are limited to Federally Facilitated Marketplace (FFM) states and state-based Marketplaces using the federal platform (SBE-FM) and do not extend to state-based Marketplaces operating their own eligibility and enrollment systems. Individual issuer effects could vary materially based on several factors, including state, county, issuer, product, broker channel, and member premium contribution. 

Some issuers will be more exposed than others, particularly those with more enrollees paying low or $0 net premiums, greater broker reliance, substantial automatic reenrollment, or a strong presence among lower-cost plans. Understanding the financial impact will require analysis at the plan and market levels. 

Key Actions for Health Insurers Following CMS Marketplace Disenrollments 

Health insurers should assess a range of outcomes at the plan and state levels. This analysis should show how the concentration and health profile of canceled enrollment could affect claims, APTCs, risk adjustment, financial accruals, administrative expenses, distribution, and future rates. 

The timing of CMS’s actions will shape those outcomes. Because the announced cancellations apply retroactively to original effective dates, insurers will need to account for APTC recoupment and related enrollment and financial adjustments. The ultimate impact will depend on the data CMS provides, the scope of additional reviews, processing timelines, and any appeals or corrections. Issuers should revisit their forecasts as these details emerge and federal actions continue ahead of the 2027 plan year. 

Assessing Marketplace Disenrollment Risk: How HMA and Wakely Can Help 

Health Management Associates (HMA) and Wakely Consulting Group combine policy, market, actuarial, and financial expertise to help health plans and state regulators assess the effects of Marketplace program-integrity actions. For insurers, our teams can develop plan-by-plan and state-by-state projections of enrollment, morbidity, claims, APTCs, risk adjustment, and premiums; test prospective and retrospective cancellation scenarios; and translate the findings into pricing, forecasting, distribution, and market strategy decisions. 

State insurance regulators in affected FFM and SBE-FP states will need a market analysis of how the cancellations are distributed across issuers and whether changes in enrollment and morbidity could affect rates, risk adjustment, capital, or continued plan participation. Regulators should also evaluate whether approved 2027 rates and financial assumptions remain supportable and monitor solvency and consumer access as insurers adjust to this and CMS’s broader program integrity actions. HMA and Wakely can support this work through state-specific market assessments, issuer-level stress testing, rate and risk-pool analysis, and scenario projections that help regulators identify emerging concerns and act before they threaten market stability.

Pennsylvania Health Policy Conference 2026: What’s Next for Medicaid Enrollees, Rural Hospitals, and the Workforce

Read Blog

State of Reform (SOR), an HMA Company, hosted its inaugural Pennsylvania Health Policy Conference in Harrisburg on September 16, 2026, bringing together more than 170 interest-holders, including state health and human services departments leaders, policymakers, providers, health plans, community‑based organizations (CBOs), and others to discuss the most pressing health-related issues in the commonwealth. 

The conference focused on how federal Medicaid policy changes, managed care challenges, and workforce shortages, are reshaping Pennsylvania’s healthcare landscape while highlighting prevention and cross-sector collaboration as essential to building a more sustainable system. Key discussions are highlighted below. 

Central Discussions: Federal Medicaid Policy, Managed Care, and the Workforce 

Pennsylvania Medicaid 

Valerie Arkoosh, MD, Secretary of the Pennsylvania Department of Human Services (DHS) opened the conference by examining how federal policy and fiscal pressures are likely to affect Pennsylvania’s health and human services system. She discussed the anticipated loss of Medicaid coverage for approximately 310,000 enrollees due to the 2025 budget reconciliation act (P.L 119-21, now known as the Working Families Tax Cut Act [WFTCA]) and the resulting strain on individuals, providers, and the broader healthcare system. 

WFTCA and broader financial pressures also raise concerns about the sustainability of hospitals, with closures threatening access to care, especially in rural and underserved communities. Hospitals and safety-net facilities are consistently working against staffing shortages, capacity constraints, and shifting payer dynamics. Pennsylvania is using funds from the Rural Health Transformation Program (RHTP) to support struggling rural hospitals as best it can. DHS has awarded $42 million in RHTP grant fund awards so far to support various rural facilities. 

Medicaid managed care 

Community HealthChoices (CHC), Pennsylvania’s Medicaid managed long-term services and supports (MLTSS) program, has been at the forefront of the healthcare conversation in the state as a result of the cancellation of its 2024 contract awards for the program. In June 2026, DHS released a request for information seeking responses on several topics that could shape a new CHC re-procurement, including the number of Medicaid managed care organizations (MCOs) within CHC, regional versus statewide coverage, length of contract terms, strategies to align coordination of Medicare and Medicaid, artificial intelligence (AI), and other program recommendations. 

During the managed care discussion, Sally Kozak, Deputy Secretary of the Office of Medical Assistance Programs, and Emily Katz, Executive Director of Pennsylvania Medicaid MCOs, joined health plan leaders in assessing how well the physical health managed care program is improving access, quality, and cost management. 

The conversation centered on persistent challenges involving provider participation, care coordination, the complexity of administering the programs, and the variation in performance by region. There are opportunities to reform or refine managed care to better align incentives with patient needs and system sustainability. 

Workforce shortages 

Like all states, Pennsylvania is facing a health professional shortage across all sectors. Jennifer Hale, Director of the Bureau of Policy and Regulatory Management in the Office of Long-Term Living, and Garry Pezzano, President and Chief Executive Officer of LeadingAge PA, highlighted how this issue is affecting people who need long-term care. Speakers emphasized that Pennsylvania’s ability to meet the needs of an aging population will depend largely on strengthening the workforce that delivers these services. They explained several of the strategies underway and being discussed to achieve this goal, for example by improving wages and benefits for direct care workers, strengthening education and training pipelines, expanding loan repayment programs, prioritizing recruitment, and investing in technology for telehealth services and AI-assisted workflows. 

Advancing Change: Upstream Interventions and Collaboration 

Paying for care continues to be a chief concern. While many of the financial pressures come from within the healthcare system as the result of policy and budgetary challenges, throughout the conference speakers emphasized that many of Pennsylvania’s most pressing healthcare challenges begin outside the healthcare system. Food insecurity, unstable housing, transportation barriers, limited caregiver support, and lack of social and community supports worsen health outcomes and lead to increased healthcare expenditures. 

Panelists called for greater investment in upstream prevention services that help people remain healthy and independent before their needs become more acute to contain costs over time. Speakers recommended approaches such as expanding housing supports, food as medicine initiatives, community health worker investments, caregiver supports, reentry services, and technology that allows people to receive care at home, as well as other initiatives to ensure people can remain healthy and independent. 

Pennsylvania has already begun investing in several of these areas. The fiscal 2027 budget allocated $1.9 million to the Investments in Health pilot program for housing stability services and reentry supports for incarcerated individuals. Federal matching dollars for the first year of this program total $5.2 million. Another tool, PA Navigate, connects people with CBOs, state agencies, and providers that can help people access basic necessities. 

Speakers also stressed that these efforts will have limited reach if organizations operate separately. Better coordination among healthcare providers, MCOs, CBOs, hospital systems, and state agencies can reduce the fragmentation, make services easier to navigate, and help funding and data systems support common goals. That message was consistently expressed throughout the conference: Pennsylvania’s healthcare challenges cannot be addressed by one sector alone, and progress will depend on sustained collaboration among the organizations that serve individuals and communities. 

Looking Ahead 

If you are looking for strategies and solutions to address urgent healthcare policy and operational challenges, Health Management Associates (HMA) experts are available to help you navigate these complex changes and identify practical paths forward. 

Through the HMA National Conference, State of Reform partnership events, and other HMA meetings across the country, we connect state leaders, providers, health plans, and community stakeholders to share insights, elevate lessons, and advance solutions. Join us at an upcoming event—including our next HMA National Conference in New Orleans, LA, October 5–7, 2026—or explore additional opportunities to engage with HMA and access the full schedule of conferences and resources. 

State of Reform develops its conference agendas through collaboration with HMA subject matter experts/market leads and stakeholders across the public and private sectors, including state officials, community-based organizations, providers, payers, and more.

VA Community Care Program: Richard Topping to Discuss NextGen VA at HMA 2026 Conference

Read Blog

Health Management Associates (HMA) is pleased to welcome The Honorable Richard F. Topping, Assistant Secretary for Management and Chief Financial Officer at the US Department of Veterans Affairs (VA), to HMA’s US Healthcare 2026: Signals, Signs & Flashing Lights conference, October 5-7, 2026, in New Orleans, LA. His participation will give health plans, providers, technology companies, and other organizations interested in working with the VA Community Care program a timely opportunity to hear directly from senior VA leadership about the priorities shaping the program’s next phase. 

VA Community Care Priorities and Opportunities for Collaboration 

HMA’s Jean Glossa, MD, MBA, FACP, will join Mr. Topping during Community Care for Veterans—NextGen VA to discuss priority healthcare issues for the VA. They will examine the VA care delivery system, Mr. Topping’s areas of oversight, and opportunities to better integrate care delivered by VA providers with services furnished by contracted community providers. 

In addition to its direct care system, the VA operates six national payer programs, including VA Community Care—now the fourth-largest health insurer in the United States. Mr. Topping will describe how the VA is shifting Community Care from a network administration model toward a true healthcare purchasing and performance‑management model. CCN NextGen is the VA’s first major modernization of Community Care contracting since the MISSION Act, which took effect in 2019. This 10‑year, multiple‑award IDIQ structure will increase competition, enable regional adaptability, and support iterative improvements through sequential task orders opening up new opportunities for industry to partner with the VA. 

Explore Best Practices for Working with the VA 

Mr. Topping also will participate in one of HMA’s Coffee Conversations and Collaborations, a highly interactive format, which fosters practical discussion. Participants will have an opportunity deepen their knowledge about effective approaches to working with the VA, ask questions, and share experiences. This combination of senior-level perspective and smaller group dialogue makes Mr. Topping’s participation especially relevant for managed care plans, provider organizations, technology firms, and other partners monitoring the direction of VA Community Care. 

Join VA and Healthcare Leaders at HMA’s 2026 Conference 

HMA is honored to host Mr. Topping and create space for a substantive discussion about the future of VA Community Care. Register for HMA’s US Healthcare 2026 conference to hear directly from leaders who are shaping public healthcare and connect with peers working to turn policy priorities into stronger systems of care. 

Medicaid Managed Care Enrollment Declines in Q2 2026: HMA Analysis of State Trends and Market Share

Read Blog

Health Management Associates (HMA) analyzed monthly Medicaid managed care enrollment data reported by 34 states in the second quarter of 2026. Enrollment totaled 59.2 million members in June 2026—a decline of 3.5 million members (5.5%) from June 2025. The broader Medicaid and CHIP population has declined at approximately the same pace as managed care, with the Centers for Medicare & Medicaid Services (CMS) data showing a 5.9% decrease from May 2025 to May 2026. 

The findings establish a timely baseline before new eligibility policies take effect. Under the 2025 budget reconciliation act (P.L. 119-21), now known as the Working Families Tax Cut (WFTC) Act, most states must implement Medicaid community engagement requirements for certain adults beginning January 1, 2027, conduct eligibility redeterminations every six months for this population, and implement other policies that will narrow Medicaid eligibility. 

Medicaid Managed Care Enrollment Trends in Q2 2026 

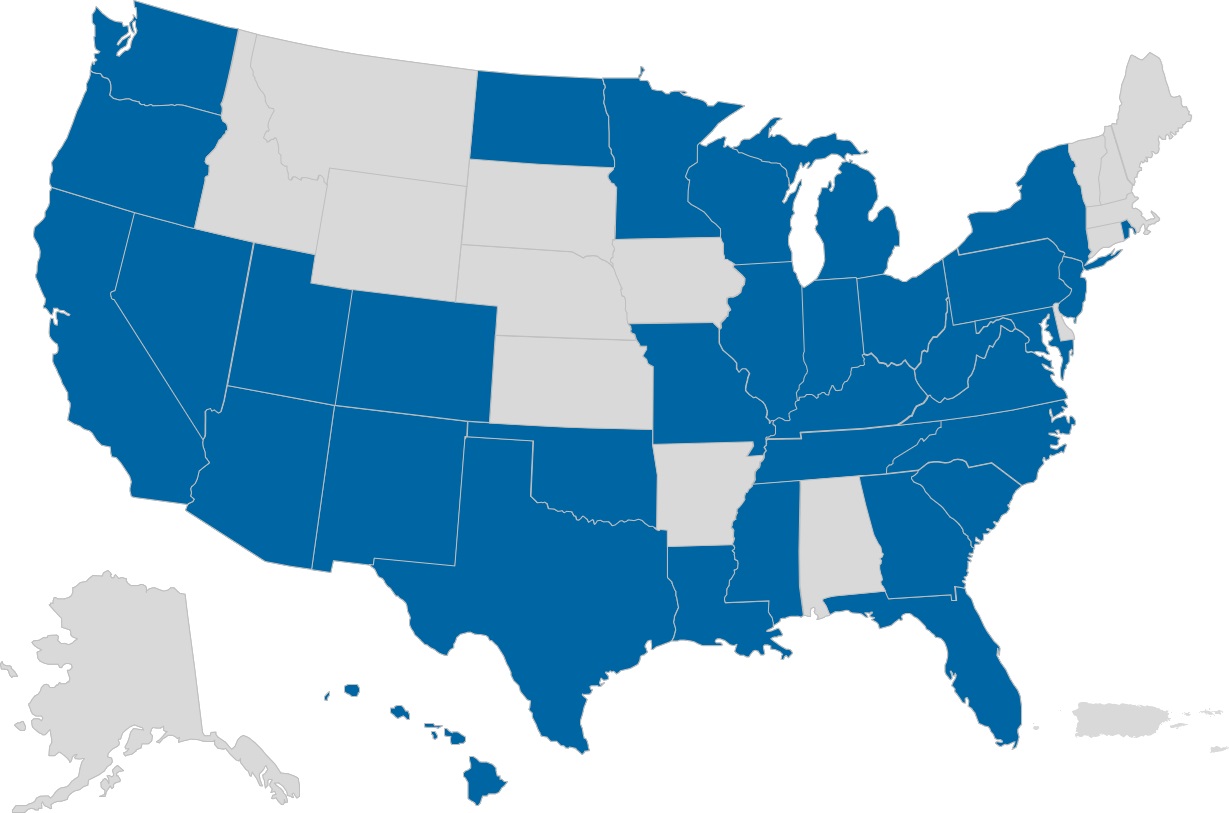
HMA Information Services (HMAIS) tracks monthly Medicaid enrollment for all states, including managed care enrollment in the subset of states with managed care programs. Among the 34 states with managed care programs that reported enrollment data in the second quarter of 2026: 

  • Enrollment changes varied across states, reflecting a combination of state-specific demographic, administrative, operational, and policy factors. 
  • Only three states—Mississippi, Nevada, and South Carolina—reported modest gains in Medicaid managed care enrollment since June 2025. 
  • Arizona, Indiana, and Louisiana each reported double-digit declines, ranging from 10.1% to 21.1%. 
  • The seven non-expansion states in this analysis—Florida, Georgia, Mississippi, South Carolina, Tennessee, Texas, and Wisconsin—experienced a decline of 455,000 (3.8%), bringing enrollment to 11.6 million enrollees. 

Among the expansion states in the analysis, enrollment decreased by 3 million (5.9%) to 47.6 million. The larger decline among expansion states is particularly relevant because adults in expansion states will be most directly affected by the new community engagement and six-month redetermination policies. Details are illustrated in Figure 1. 

Figure 1. States Included in the Medicaid Managed Care Enrollment Analysis, June 2026

Note: States colored as blue shown on the map above are included in the HMA Enrollment Analysis. 

National Medicaid Managed Care Market Share 

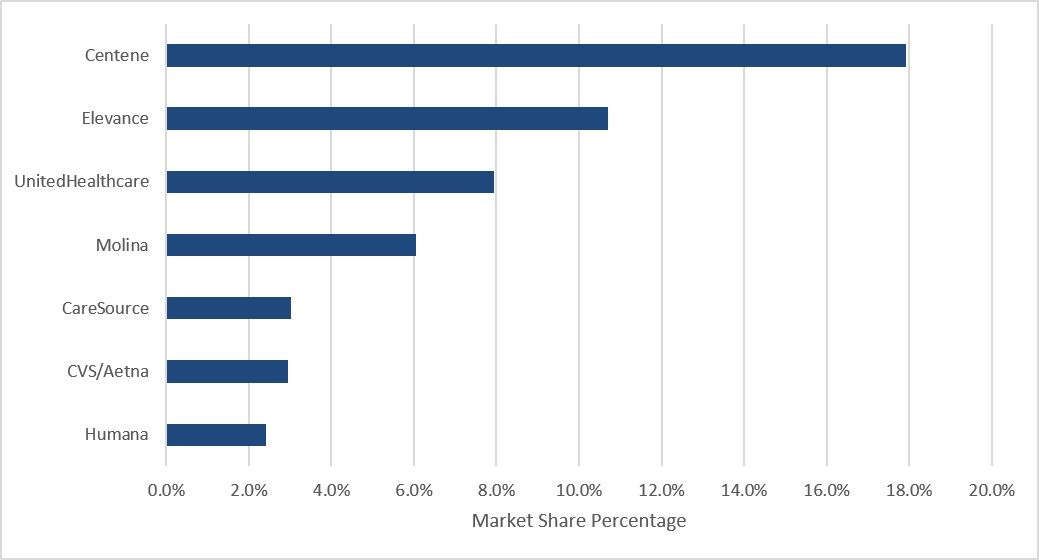
HMAIS also tracks Medicaid managed care ownership, program participation, and tax status for nearly 300 plans. In this June 2026 snapshot, Centene covered 17.9% of enrollees, followed by Elevance at 10.7%, UnitedHealth Group at 8%, and Molina at 6% (see Figure 2). These four organizations represented 42.6% of enrollment in the HMAIS dataset, underscoring continued concentration among large, national Medicaid managed care organizations. (Note: The number and mix of plans changed over the past 12 months, and several state enrollment reports reflect different reporting months. Other limitations are discussed in the Data Considerations section of this article.) 

The enrollment declines as well as pressure from acuity, utilization, and payment rates are compelling Medicaid managed care organizations (MCOs) to reassess where they participate, including whether individual markets can support sustainable performance. For example, one national Medicaid MCO has publicly discussed exiting unprofitable Medicaid markets and left one state market in August 2026 with plans to exit another at the end of the year. These decisions illustrate how enrollment contraction can interact with rate adequacy, acuity, utilization, and state-specific contract performance to influence plan participation. 

Figure 2. National Medicaid Managed Care Enrollment Share by Parent Organization, June 2026 

How Medicaid Work Requirements and Eligibility Policies Could Affect Enrollment in 2027 

In June 2025, approximately 20.4 million people were enrolled in Affordable Care Act Medicaid expansion plans—5 million of whom reside in California, and nearly 2 million live in New York. The WFTC Act applies requirements to Affordable Care Act (ACA) expansion adults and certain Medicaid Section 1115 demonstration populations in 44 states beginning January 2027. 

In September 2026, CMS published an implementation resource that outlines an optional framework that states may use to identify and verify individuals who qualify for the medical frailty exclusion. Although the framework gives states options for consideration, they still must determine which health conditions to cover and data sources to use when additional documentation is requested and how to notify members of their determinations. Many states have already made decisions about these issues, which could materially affect administrative workload, the consistency of determinations, and whether eligible individuals maintain coverage as well as the number of people who retain coverage and the composition of the population that remains enrolled. 

In addition, a few states have already started implementing the new eligibility policies. For example, Nebraska launched Medicaid work/community engagement requirements on May 1, 2026. Montana began implementation on July 1, 2026, while Arkansas began a soft launch in July 2026 before enforcement begins in January 2027. Iowa intends to begin early implementation December 1, 2026. Although Montana and Arkansas are not managed care states, they, along with Nebraska, can offer directional insights on beneficiary response, exclusion determinations, procedural losses, appeals, and administrative workload before nationwide implementation. 

Notably, the second quarter enrollment decline predates full implementation of the new federal eligibility policy changes and community engagement requirement, which means future enrollment changes may not be entirely attributable to the WFTCA requirements. 

Organizations should continue to monitor total enrollment, churn, eligibility category, risk mix, and transitions to Marketplace or uninsured status. 

Data Considerations. HMA Information Services (HMAIS) tracks monthly Medicaid managed care enrollment, ownership, program participation, and tax status for approximately 300 plans. The data in this analysis have some important limitations. States report enrollment figures at different points throughout the month, with some data reflecting beginning of the month totals and others capturing end of month enrollment. In addition, some state datasets encompass all Medicaid programs that offer managed care plans, whereas others reflect only a subset of the managed Medicaid population. As a result, the analysis can be used to identify direction, magnitude, and market signals rather than as a comprehensive state-by-state comparison. 

The HMAIS enrollment reports and analyses, available through subscription, use data from nearly 300 health plans in 39 states, DC, and Puerto Rico. HMAIS’s Medicaid enrollment data, financials, procurement tracking, and a robust library of public documents equips stakeholders with timely, actionable intelligence. Subscribe here. 

Preparing for Enrollment Shifts

WFTC Act implementation will require state-specific policy decisions, eligibility system changes, new data-matching processes, staff training, beneficiary outreach, and workable approaches to identifying people who qualify for exemptions for medical frailty and other conditions. Differences in data availability, verification pathways, documentation requirements, and review processes could produce materially different effects on enrollment, continuity of coverage, beneficiary experience, and the risk profile of the population that remains enrolled. 

Healthcare executives and state Medicaid leaders should establish a baseline, monitor emerging implementation signals, and model the operational and financial implications. Priority measures include enrollment and churn, procedural terminations, exclusion determinations, appeals, transitions to other coverage, changes in acuity and utilization, payer mix, and geographic variation. These insights can inform decisions about eligibility operations, beneficiary support, capitation and rate development, network strategy, provider reimbursement, revenue forecasting, and uncompensated care exposure. 

MCOs are unable to help states with determining eligibility determination or compliance, cannot receive capitation rate bumps for non-medical activities, or use their own work programs to help beneficiaries meet the community engagement requirements but may be able to provide support through outreach and education. CMS has indicated it expects to provide additional guidance on what activities are appropriate. MCOs can potentially use their existing relationships with beneficiaries, care managers, providers, and community organizations to help members understand and navigate the new requirements. 

HMAIS provides the market intelligence needed to track these shifts, including state-reported enrollment, plan ownership, financial performance, procurement activity, and related public documents. HMA consultants extend that intelligence through state- and market-specific scenario modeling, policy and operational analysis, and implementation support—helping clients forecast enrollment and revenue, assess payer mix and utilization effects, strengthen eligibility and beneficiary support workflows, evaluate competitive positioning, and prepare for changes in program financing and oversight. 

Contact HMA to translate evolving enrollment and implementation signals into an actionable strategy for your state, market, or organization.

Ready to talk?