Insights

HMA Insights: Your source for healthcare news, ideas and analysis.

HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.

or
or
Receive timely expert insights on topics you care about.

257 Results found.

CMS Finalizes 2026 Payment and Policy Updates for Medicare Advantage and Part D

Read Blog

CMS approves average increase of 5.06 percent for MA plans while deferring major policy changes in MA and Part D programs

The Centers for Medicare & Medicaid Services (CMS) released the 2026 Medicare Advantage (MA) and Part D Rate Announcement on April 7, 2025, finalizing payment updates for calendar year (CY) 2026. This announcement came shortly after the release of the Contract Year 2026 MA, Part D, and PACE Policy and Technical Changes Final Rule, on April 4, 2025. Together, these updates mark the conclusion of CMS’s annual rulemaking cycle for Medicare Advantage, ahead of the June 2, 2025, deadline for 2026 MA plan bids.

Notably, because of the timing of the draft notices and proposed rule, Trump Administration officials ultimately had more input into policies omitted from the rate notice and final policy rule than on policies that were finalized. For example, the final rule is exclusive of proposals to expand coverage for anti-obesity medications, guardrails for artificial intelligence (AI), and new requirements related to utilization management and prior authorization procedures.

In his confirmation hearing, CMS Administrator Mehmet Oz, MD, cited Medicare Advantage prior authorization practices and health risk assessments that lead to upcoding as areas that deserve further consideration and scrutiny, raising the potential for future regulatory shifts and even legislative reform. With the possibility of Medicare, including MA, facing cuts as part of broader budget negotiations in Congress, the rate notice and policy rule offer program stability counterbalancing the political and fiscal pressures that may emerge this year.

CMS has sought to stabilize MA and Part D programs into 2026, and stakeholders can benefit from understanding the impact in markets for 2026 and the signals of potential regulatory changes to come. For more in-depth analysis and insights on the rate notice, look for our policy and actuarial experts’ brief due out next week.

The remainder of this In Focus article reviews CMS’s decisions on major payment and policy proposals in the Rate Announcement and Final Rule and examines key considerations for healthcare stakeholders.

Payment Impact on Medicare Advantage Organizations

In the CY 2026 Rate Announcement, CMS projects that federal payments to MA plans will increase by 5.06 percent from 2025 to 2026, which represents a $25 billion increase in expected payments to MA plans next year. According to CMS, this represents an increase of 2.83 percentage points compared with the CY 2026 Advance Notice that is largely attributable to an increase in the effective growth rate. The increase in the effective growth rate—increasing to 9.04 percent in the Rate Announcement from 5.93 percent in the Advance Notice—is primarily the result of the inclusion of additional data on Medicare fee-for-service (FFS) expenditures, including payment data through the fourth quarter of 2024.

The Rate Announcement estimates represent the average increase in payments to MA plans and actual payments will vary from plan to plan. Below, Table 1 provides CMS estimates of the impact of finalized payment changes on net MA plan payments.

MA Risk Adjustment Changes

As expected, CMS finalized the last year of the three-year phase-in of the MA risk adjustment model, which requires calculating 100 percent of the risk scores using only the 2024 CMS-HCC (Hierarchical Condition Category) model in 2026. CMS also addressed stakeholder concerns with the planned transition toward a risk adjustment model based on MA encounter data, as previewed in the CMS CY 2026 Advance Notice. CMS pledged to engage stakeholders in this model development process while continuing to evaluate the feasibility, transparency, and timing of a future transition to an encounter-based risk adjustment model.

CMS also finalized the MA coding pattern adjustment factor of 5.9 percent for CY 2026, which is the statutory minimum adjustment factor to account for differences in coding patterns between MA plans and providers under Medicare FFS Parts A and B.

Part D Risk Adjustment

For CY 2026, CMS finalized the revised 2026 RxHCC model with adjustments for maximum fair price drugs. Importantly, CMS also finalized using separate FFS normalization factors for MA-Prescription Drug (MA-PD) plans and Prescription Drug Plans (PDPs), making 2026 the second year CMS will vary normalization for these two markets. The calculation of the factors for CY 2026 is different, however, and will have substantially greater impact than the method used previously. It also will reduce Part D risk scores significantly for MA-PD plans while increasing scores for PDPs.

MA Star Ratings

CMS continues to solicit feedback from stakeholders on ways to simplify and refocus MA Star Ratings measures to focus more on clinical care, outcomes, and patient experience of care measures. Also included in the CY 2026 Rate Announcement are non-substantive measure specification updates and a list of measures included in the Part C and Part D improvement measures and categorical adjustment index for the 2026 Star Ratings.

Separately, in the policy and technical changes rule, CMS finalized new regulatory requirements designed to enhance MA beneficiary protections in an inpatient setting, provisions related to allowable special supplemental benefits for the chronically ill (SSBCI), and the care experience for dually eligible beneficiaries enrolled in MA special needs plans.

Enhancing MA Beneficiary Appeal Rights and Notification Requirements

CMS is finalizing provisions that limit the ability of MA plans to reopen and modify a previously approved inpatient hospital decision on the basis of information gathered after the approval. Under the final rule, MA plans will be able to reopen an approved hospital admission only due to error or fraud. In addition, CMS finalized several provisions to enhance beneficiary appeal rights and new reporting and notice requirements, including:

  • Ensuring that MA appeals rules apply to adverse plan decisions, regardless of whether the decision was made before, during, or after the receipt of such services
  • Codifying existing guidance that requires plans to give a provider notice of a coverage decision
  • Ensuring enrollees have a right to appeal MA plan coverage denials that affect their ongoing source of treatment

Non-Allowable Special Supplemental Benefits for the Chronically Ill

The final rule establishes guardrails for SSBCI benefits by codifying a list of non-allowable examples (e.g., unhealthy food, alcohol, tobacco, life insurance). CMS did not finalize proposals that were designed to improve administration of supplemental benefits and enhance transparency of the availability of such benefits.

Improving Care Experience for Dual Eligibles

CMS finalized new requirements for dual eligible special needs plans (D-SNPS) that are applicable integrated plans (AIPs) as follows:

  • D-SNPs will be required to have integrated member ID cards for their Medicare and Medicaid plans
  • D-SNPs will be required to conduct an integrated health risk assessment for Medicare and Medicaid, rather than separate ones for each program.

These provisions affecting certain D-SNPS plans will be effective for the 2027 plan year.

Provisions Pertaining to the Medicare Part D Inflation Reduction Act

CMS is finalizing proposals to codify existing requirements related to key provisions of the Inflation Reduction Act, including no cost sharing for adult vaccines and capping monthly copayments for insulin at $35. In addition, CMS is codifying existing guidance related to the implementation of the Medicare Prescription Payment Plan, which is also part of the Inflation Reduction Act.

Key Proposals CMS Has Yet to Finalize

As noted earlier, CMS finalized a streamlined rule that excluded several regulatory changes identified in the November 2024 proposed rule. In addition to provisions related to coverage of anti-obesity medications, guardrails for AI, and mandatory analysis of the health equity impact of MA plans utilization management practices, the following proposals were not finalized. CMS notes that these proposals might be finalized in future rulemaking.

  • Expanding Medicare Part D Medication Therapy Management (MTM) eligibility criteria
  • Ensuring equitable access to behavioral health services by applying MA cost-sharing limits
  • Enhancing the Medicare Plan Finder to include information on plan provider directories
  • Promoting informed choice by enhancing CMS review of MA marketing and communication materials
  • Enhancing rules on MA plans’ use of internal coverage criteria

Key Considerations

The policies finalized in the CY 2026 Rate Announcement are projected to increase average Part C payments to MA plans by 5.06 percent in CY 2026—a significant uptick from the payment updates originally proposed in the CY 2026 Advance Notice. Nonetheless, the final rate increase will have varying effects across MA plans, with some experiencing larger or smaller impacts in CY 2026. MA plans should assess these outcomes as they prepare their bid submissions for 2026.

According to the CY 2026 Rate Announcement, CMS expects that the 5.06 percent increase will provide continued stability for the MA program and its beneficiaries while ensuring accurate and appropriate payments to Medicare Advantage organizations.

In the CY 2026 MA and Part D Final Rule, CMS adopted a significantly scaled-back final rule, which omitted some of the more far-reaching proposals for MA and Part D that were originally proposed in November 2024. CMS, however, could potentially revisit and finalize some of these proposals in future rulemaking. Moreover, new regulatory requirements that enhance enrollee protections in inpatient care settings and improving the care experience for dual eligibles signal CMS’s continued interest in improving program oversight and enhancing consumer protections for MA beneficiaries.

Connect With Us

MA stakeholders need to undertake scenario planning and be prepared to adapt to a rapidly evolving federal policy environment. From modeling and impact assessments of specific policy changes to strategy development and implementation, HMA is home to experts with diverse skill sets. Our team can help stakeholders assess and prepare for potential changes to prior authorization, looking holistically at their organization’s operations, patient care models, and reimbursement strategies. Our team also provides detailed modeling and assessments to ensure health plans are prepared for changes in risk adjustment and coding policies, supplemental benefits, and other key issues affecting capitation payment, bids, and care delivery models.

For details about the finalized payment and policy rules contact our featured experts below.
HHS Begins Reorganization: Actions Focus on Efficiency, Establishment of Administration for a Healthy America

Read Blog

On March 27, 2025, the US Department of Health and Human Services (HHS) Secretary Robert F. Kennedy, Jr. announced significant changes in the department with respect to staffing and organizational restructuring. This reorganization is consistent with President Trump’s February 11, 2025, Executive Order (EO) 14210, “Implementing the President’s Department of Government Efficiency Workforce Optimization Initiative.”

HHS is moving rapidly to implement its plans. On April 1, 2025, HHS initiated actions to reduce the federal workforce across the agencies and remake the department. In addition, the Senate is expected to vote on a budget resolution this week, which could have significant impacts on federal healthcare spending, including for the Medicaid and Medicare programs.

In the coming weeks and months, HHS intends to make additional announcements about how the department will be restructured. It will be critical that healthcare organizations and stakeholders track these developments closely. Organizations seeking to participate in the development of new federal policies and initiatives must know which offices within HHS will maintain authority over key policy areas. Further, to adapt to changes in funding and policies, it is vital that healthcare leaders remain informed.

Because many changes have already begun, the remainder of this article explains what is known to date about the HHS restructuring and other developments and actions relevant to providers, life sciences firms, insurers, safety net clinics, state and local agencies, and other interested stakeholders. This information can help stakeholders consider how best to proceed.

The Reorganization Plan

EO 14210 required agencies to develop reorganization plans and submit them to the Director of the Office of Management and Budget within 30 days and to “promptly undertake preparations to initiate large-scale reductions in force.” The broader HHS reorganization plan seeks to implement a new departmental focus on “ending America’s epidemic of chronic illness by focusing on safe, wholesome food, clean water, and the elimination of environmental toxins.”

The reorganization calls for the following:

  • Consolidating the 28 HHS divisions into 15
  • Reducing the HHS regional offices from 10 to five
  • Centralizing the human resources, information technology, procurement, external affairs, and policy functions of the department
  • Reducing the full-time staff at HHS by 10,000

When combined with other efforts, including early retirement and pre-reduction in force (RIF), HHS’s staffing levels of 82,000 full-time will be reduced to 62,000. The announcement listed specific workforce reduction plans for the Food and Drug Administration (FDA), the Centers for Disease Control and Prevention (CDC), the National Institutes of Health, and the Centers for Medicare & Medicaid Services (CMS).

Following the March 27 announcement, additional details regarding the restructuring have continued to emerge, including:

  • The Biomedical Advanced Research and Development Authority (BARDA) reportedly will be combined with Advanced Research Projects Agency for Health (ARPA-H) under a new Office of Healthy Futures.
  • The Administration for Strategic Preparedness and Response (ASPR) will be reorganized as a part of CDC.
  • Programs currently under the Administration for Community Living (ACL) are slated to be reassigned to other agencies; for example, programs that support older adults and people with disabilities will move to the Administration for Children and Families (ACF), Assistant Secretary for Planning and Evaluation (ASPE), and CMS.

HHS Plans for New Agencies that Mirror Policy Priorities

The reorganization includes the establishment of a new Administration for a Healthy America (AHA), which will combine the following offices and agencies:

  • Office of the Assistant Secretary for Health, which includes the Office of the Surgeon General, the Office of Women’s Health, and several programs focused on health promotion, chronic disease prevention, and vaccines
  • Health Resources and Services Administration (HRSA)
  • Substance Abuse and Mental Health Services Administration (SAMHSA)
  • Agency for Toxic Substances and Disease Registry (ATSDR)
  • National Institute for Occupational Safety and Health (NIOSH)

According to HHS, the changes are intended to “improve coordination of health resources for low-income Americans and will focus on areas including, Primary Care, Maternal and Child Health, Mental Health, Environmental Health, HIV/AIDS, and Workforce development.” The department also noted that transfer of SAMHSA to the new AHA will “break down artificial divisions between similar programs” and improve operational efficiency.

HHS also intends to establish a new Assistant Secretary for Enforcement position, which will be responsible for leading efforts to address waste, fraud, and abuse at the Departmental Appeals Board, Office of Medicare Hearings and Appeal, and the Office for Civil Rights.

HHS will merge the ASPE and Agency for Healthcare Research and Quality (AHRQ) to establish a new Office of Strategy. The new office will support research “that informs the Secretary’s policies and evaluates the effectiveness of federal health programs.” This office will also include some of the “critical programs that support older adults and people with disabilities” that are currently within the Administration for Community Living.

Developments on Workforce Reduction Plans

On April 1, 2025, HHS began issuing formal termination notices to a significant number of federal employees across several agencies, including the FDA, SAMHSA, and CDC. The workforce actions reportedly include a full dissolution of some offices, for example, SAMHSA’s Office of the Director for Centers for Mental Health Services, Office of Behavioral Health Equity, The Policy Lab, among others, and CMS’s Medicare Medicaid Coordination Office.

What’s Next

In the coming weeks HHS will put in place a structure for the new AHA and other planned new entities. Many questions remain about the impact on specific agencies and authorities as well as reassignment of responsibilities for programs and functions that were carried about by affected federal employees and offices.

Congressional committees are seeking additional information about the HHS restructuring. The US Senate Committee on Health, Education, Labor, and Pensions (HELP) requested that Secretary Kennedy testify at a hearing on April 10, 2025, to discuss the proposed reorganization plan. Providers, health centers, life sciences firms, insurers, health systems, state and local agencies and other healthcare stakeholders and partners should take steps to work through challenges and avail themselves of opportunities to strengthen healthcare systems and improve health. Examples include:

  • Identify the HHS agencies and offices that are now responsible for policies and procedures that impact your business.
  • Establish a plan for tracking developments—including litigation—and processes to brief key organizational leaders and act on information, when needed. Healthcare providers, insurers, community groups, and state and local governments will benefit from information as it becomes available regarding changes to agencies and their portfolios and decision makers for policies governing Medicare, Medicaid, child-specific programs, aging and disability programs, mental health and substance use programs, among many others.
  • Immediately assess current federal discretionary funding and reimbursement policies that may be at risk for your organization, your key partners, and collaborators. Consider potential impact of the policy changes that Congress is separately negotiating, which would significantly affect Medicare and Medicaid. Identify changes that may minimize risk for your organization and position it to engage in new initiatives.
  • Familiarize your organization with federal oversight and enforcement priorities and incorporate flexibility into compliance plans. Identify opportunities to mitigate vulnerabilities going forward.
  • Engage now—with your community, your peers, and other experts—to identify opportunities for improvement and plan to build out the strategy, infrastructure and funding to support this work. Think creatively, act decisively.

Connect with Us

Health Management Associates, Inc., experts know the federal landscape and have an intimate knowledge of the dynamics in states and communities. Our policy team is working with clients to help them understand what is happening within HHS and Congress that is ushering in significant policy and funding changes. Our teams are advising stakeholders on the implications for Medicare, Medicaid, and other public programs; strategies to advance their objectives in this new environment; and working with healthcare organizations and state and local government to understand immediate impacts on local financing.

For details about these federal level developments contact one of our featured federal policy experts listed below.

What to Watch: Medicare Payment Rules

Read Blog

Medicare stakeholders are awaiting the imminent release of the Centers for Medicare & Medicaid Services (CMS) final Medicare Advantage and Part D rate notice and technical updates, as well as a final policy rule that establishes a significantly new direction for Medicare Advantage (MA) stakeholders. These final rules typically are released in April of each year.

In addition, the agency kicks off the annual cycle of payment rules for traditional fee-for-service Medicare, including the first wave of proposed rules that typically are released in April for the forthcoming payment year. These proposed rules for 2026 pertain to the following: Hospital Inpatient Prospective Payment System for Acute Care Hospitals, the Inpatient Rehabilitation Facility Payment System, the Home Health Payment System, and the Inpatient Psychiatric Facility Payment System. A second wave of 2026 proposed rules are typically released in July, including the Medicare Physician Fee Schedule and the Hospital Outpatient Prospective Payment System.

The MA rules and the first wave of Medicare Part A and Part B rules are highly anticipated regulations and now under review at the Office of Management and Budget. These rules are expected to be released in the coming days and weeks.

Why These Rules Matter

The rules set the rates for MA and reimbursement for a significant number of healthcare providers and facilities that serve Medicare beneficiaries. The rules also contain important information about CMS’s quality reporting programs and bonus payments and other changes required for Medicare stakeholders to ensure compliance.

What’s Different About 2025 Proposals

In the first year of a new presidential administration, CMS leaders have a limited window to include their policy priorities in the MA and Part D Final Rate Notice. CMS may, however, decline to finalize some or all of the prior administration’s proposals. Key issues that Health Management Associates (HMA), experts are watching for in the final rules include:

  • Whether CMS chooses to delay or not finalize significant policy changes proposed by the Biden Administration, including new requirements and guardrails around the use of prior authorization
  • Potential finalization of improvements to the Medicare plan finder
  • Direction on oversight of MA plan marketing activities
  • CMS decision and response to the proposal to expand coverage of anti-obesity medications under Medicare Part D and Medicaid

Stakeholders can access HMA’s review of the contract year (CY) 2026 MA and Part D proposed rule and key considerations and our review of the 2026 Advance Notice for the Medicare Advantage and Medicare Part D programs.

Similarly, in the first year of a presidential transition, CMS has a narrower opportunity to shape Medicare’s first set of proposed payment and policy rules. The agency may, however, begin to signal important policy direction on a global level and technical issues that can have an impact on Medicare stakeholders. HMA experts are watching in particular for requests for information and other signals of CMS’s Medicare priorities, including reforms in quality reporting, value-based contracting, pricing and contract transparency, among others.

Connect with Us

HMA’s expert consultants provide the advanced policy, tailored analysis, and operational skills you need to navigate today’s rapidly evolving regulatory landscape and to support implementation of final policies. Don’t let the uncertainty of future policies derail your strategic plans or burden your teams.

For details about the forthcoming Medicare Advantage and traditional Medicare regulations, contact one of our featured experts below.

Navigating Uncertainty in Medicare and other Federal Health Programs

Read Blog

As we approach Medicare’s 60th Anniversary this July, the program again finds itself at a critical crossroads, facing demands for higher quality care, expanded access to transformative treatments, and streamlined patient access to their medical information.  Decision makers also must integrate digital tools into clinical models, address mounting scrutiny of costs, and ensure accountability for outcomes influenced by social determinants of health.

This period of transition at the Federal level is bringing new scrutiny and pressure for efficiency. With more than 68 million beneficiaries, nearly half of whom are enrolled in Medicare Advantage, the Medicare program is continually evolving to respond to shifting policies and priorities. Organizations that stay ahead of policy changes will be best positioned for success and drive meaningful improvements for Medicare beneficiaries.

When you work with HMA’s federal policy experts, you get access to former CMS officials and plan executives, payment system and coding experts, and policy analysts to support your efforts. HMA’s Medicare team includes experts specializing in Medicare Advantage, dual eligibles, Medicare stars, value-based care, rural health, PACE, actuarial support, and data and quality. We draw on the resources of experts from our HMA companies to provide comprehensive and end-to-end solutions. Read some of our insights in the links below.

Here’s how HMA is helping clients navigate this dynamic landscape:

  • Our policy team is working with clients to understand what is happening right now in Congress and in the US Department of Health and Human Services that will usher in significant policy and funding changes. Our teams are advising stakeholders on the short- and long-term implications, strategies to advance their objectives in this new environment, and working with states to understand immediate impacts on local financing.
  • Our clinicians are working closely with insurers, providers, and health systems to strengthen models of care that address complex conditions, behavioral health issues, long-term services and supports and unique needs of special Medicare populations.
  • Our actuaries are conducting financial modeling and analysis to forecast costs, revenues, and potential outcomes to help navigate financial uncertainties in Medicare Advantage bids, Medicare payment models, and emerging environmental and regulatory issues, including digital quality measure collection, increased focused on dual integration, supplemental benefits, and drug price negotiations.
  • Our digital quality experts are working with healthcare organizations to prepare for rapid changes that digital health quality measurement will bring to reimbursement models. Our teams are advising on the influx of newly accessible clinical data to ensure it is properly validated and interpreted and working with insurers and providers to develop strategies allowing them to be more agile in contract negotiations.

To talk to an expert to help support and improve your Medicare programs, contact Greg Gierer with the HMA DC office ( [email protected]) or Josh Trent with the Leavitt Partners DC office ([email protected]).

For more cutting-edge information check out some of our recent insights:

Policy & Regulatory Strategies: Legislative, regulatory, reimbursement, and budget analysis from experienced former staffers from CMS and various legislative committees. The HMA policy team includes past HHS officials like Amy Bassano and Monica Johnson, as well as the team at Leavitt Partners.

Actuarial & Financial Analytics: Leading actuaries with deep MA experience and robust tools to support innovative benefit and pricing strategies. Encounter data audits to improve risk scores. The HMA Actuarial team includes  Wakely Consulting Group and Cirdan Health Systems and Consulting.

Communications & Engagement: Creative campaigns to inform, persuade, and engage providers and payers. The HMA team includes 720 Strategies and Lovell Communications.

Strategy & Transformation: Strategy & analytic fundamentals informed by variety of experts in Medicare, health insurance, care delivery for older and vulnerable populations, and value-based payment and delivery innovations.

Operations & Implementation: Clinical and administrative operations building care models, implementing value-based payment incentives, technology, and compliance. The HMA Managed Care team is led by Holly Michaels Fisher.

Quality Outcomes & Research: Integrated approach to STARS ratings, building digital quality management tools and strategies for compliance and accreditation. The HMA team includes Caprice Knapp and Sarah Scholle.

CMS Shakes Up the Innovation Center Model Landscape: What Comes Next?

Read Blog

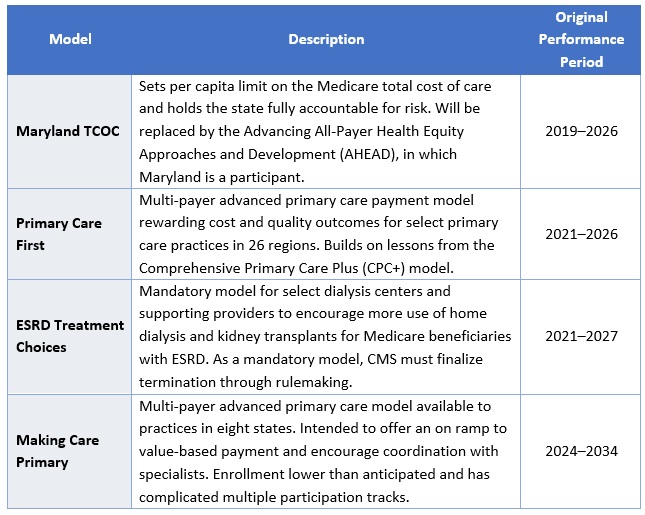
This week, our In Focus section focuses on a March 12, 2025, announcement from the Centers for Medicare & Medicaid Services (CMS) regarding CMS Innovation Center programs under the new Administration. After reviewing the Innovation Center’s model portfolio, CMS has elected to discontinue four models ahead of their original end dates: Maryland Total Cost of Care (TCOC), Primary Care First (PCF), End-Stage Renal Disease (ESRD) Treatment Choices (ETC), and Making Care Primary (MCP). The agency also intends to downsize the Integrated Care for Kids Model (InCK) and forgo the launch of two drug pricing initiatives. According to the announcement, CMS appears to be moving forward with other Innovation Center models, but signaled upcoming modifications to models to align with Administration priorities as well as new model announcements.

The following is a discussion of CMS’s announcement and what it may signal about the agency’s commitment to value-based care, key takeaways regarding the four terminated models, and how stakeholders should be preparing to engage with the Innovation Center on current or future models while we await additional details.

CMS’s Strategic Decision

As part of CMS’s recent announcement about the model terminations, the agency reaffirmed its support for testing models that reduce program spending while maintaining or improving quality of care. Furthermore, the Innovation Center “plans to announce a new strategy based on guiding principles to make Americans healthier by preventing disease through evidence-based practices, empowering people with information to make better decisions, and driving choice and competition.” These statements should be seen as a commitment to using the Innovation Center to test new approaches to delivering care but with an expectation that the models will need to demonstrate significant cost and quality improvements as outlined in its statutory authority. According to CMS, the cancellation of these models is projected to save an estimated $750 million.

Because CMS said it may modify additional models in the future, it is reasonable to expect those changes will focus on achieving a higher level of savings or to see savings earlier in the demonstration, as well as aligning model design with the priorities of this Administration. The potential modifications could have an impact on the number of model participants, length of model testing, and financial arrangements, especially with regard to risk and quality improvement approaches.

Models Ending

CMS Innovation Center models are time-limited pilots meant to help the agency test which types of interventions lead to cost savings and improved quality and, if successful, can be scaled on a nationwide basis. These models are evaluated regularly, and CMS has the authority to modify or terminate models if they fall short of the statutory criteria.

The four models the agency plans to terminate are ending for various reasons (e.g., underwhelming performance, forthcoming replacement by successor model, etc.) and, as stated above, the decision should not be seen as a retreat from value-based care, but rather as a signal regarding Administration priorities for Innovation Center models. For example, despite terminating PCF and MCP prior to their original end dates, CMS reaffirmed its support for primary care as a “foundational component of the Center’s strategy” and that future primary care payment reforms will focus on approaches that produce savings. CMS also noted that ending these models early offers an opportunity to move beneficiaries into more permanent programs, such as the Medicare Shared Savings Program (MSSP)—CMS’ flagship accountable care initiative—even going so far as to direct readers to the MSSP’s calendar year 2026 application.

CMS plans to advise current model participants of other options for advanced primary care payment before the models conclude by December 31, 2025. Table 1 presents information on the models scheduled for early termination.

Table 1: Models Ending by December 31, 2025

In addition, the agency is considering options to reduce the size of the InCK model and will no longer pursue the Medicare Two Dollar Drug List and Accelerating Clinical Evidence models. The latter two initiatives were included in a Biden Executive Order on drug pricing and were not implemented. Notably, CMS did not end another drug pricing Innovation Center model, Cell and Gene Therapy Access (CGT) Model.

Innovation Center’s New Strategic Plan

CMS also announced that it will soon release its new vision for the Innovation Center, based on principles designed to improve Americans’ health through evidence-based practices, empower individuals with decision-making information, and drive competition.

This vision will set the direction for future value-based care initiatives and reflect the leadership changes within CMS, including the anticipated confirmation of Mehmet Oz, MD, as CMS Administrator and the appointment of Abe Sutton, as the new Director of the Innovation Center. Mr. Sutton’s experience with value-based care—especially during his time as an advisor to then Department of Health and Services Secretary Alex Azar under the first Trump Administration and his subsequent private sector leadership of value-based companies—positions him to play a key role in shaping CMS’s future efforts.

Stakeholder Considerations

Stakeholders have several critical operational decisions and strategic considerations to address, including:

  • Transition Support. Participants in the models scheduled to end must assess their options for sustaining certain components of the payment models without Innovation Center support. This effort will require strategic, operational, and financial analyses to make informed decisions.
  • Evaluation of Other Programs. While the Innovation Center has signaled its intentions of announcing new models, participants should not wait to evaluate options. The Administration plans to prioritize permanent payment programs and will continue to support the MSSP as CMS’s permanent model for accountable care organizations (ACOs). Stakeholders interested in participating in the MSSP in 2026 must act quickly to assess their organizational readiness, conduct financial modeling of their potential benchmark and performance, evaluate potential partners, and prepare for the application process. Both existing and new ACOs should be exploring their strategies and infrastructures to optimize performance.
  • Adapting to Changes in Existing Models. While CMS discontinued select models, it is likely the agency will make additional changes to the Center’s continuing models. These revisions likely will reflect President Trump’s executive actions and policy priorities. With the increased focus on cost savings, CMS may choose to spend fewer resources on model implementation, including participant support and model engagement.
  • Policy and Market Intelligence. Monitoring the dynamic federal policy landscape and seeking strategic advisory support can help stakeholders navigate and inform potential future federal and state alternative payment model opportunities. Stakeholders should expect that existing and potential new models may have stricter requirements and higher expectations for financial risk. Providers, states, insurers, and other interested stakeholders should monitor public and private sector developments to understand the landscape and evolving opportunities.

Connect with Us

Health Management Associates, Inc. (HMA), is home to alternative payment model experts that can assist stakeholders in responding to changes in Innovation Center models and the agency’s approaches and to help prepare for participation in future model opportunities. Additionally, HMA produces a weekly briefing focused on public and private sector VBP-related news. To learn more about how HMA can support your organization’s federal engagement and innovation strategy, contact our experts below.

On Rare Disease Day, HMA releases new report analyzing federal spending on Orphan Drugs

Download

Rare Disease Day is observed globally each year on February 28 to raise awareness, access, and diagnosis to therapies for people with rare diseases. Today HMA releases a report titled Analyzing the Impact of Policies to Exclude Certain Orphan Drugs from the Drug Price Negotiation Program of the Inflation Reduction Act, that examines how many orphan drugs the ORPHAN Cures Act might affect and the percentage of Medicare Part B and Part D spending that is attributable to these drugs. Using that information, we estimated how the legislation would affect federal spending, applying the same assumptions and methodology that the Congressional Budget Office (CBO) uses in a 10-year budget score.

State Cost Growth Benchmarking Programs: An Evaluation of Eight States’ Experiences and the Lessons Stakeholders Have Learned

Download

Background

In 2024, Health Management Associates (HMA) evaluated programs implemented by eight states (California, Connecticut, Delaware, Massachusetts, New Jersey, Oregon, Rhode Island, and Washington) aimed at controlling healthcare cost growth. In recent years, these states have tried to address the trend of escalating healthcare costs using an approach referred to as cost growth benchmarking (CGB). This is the act of setting a target for annual healthcare cost growth and measuring actual performance against the target. Since 2018, the Peterson-Milbank Program (PMP) for Sustainable Health Care Costs has invested in state-based CGB efforts by funding program development, implementation, and technical assistance. HMA evaluated the Peterson Center on Healthcare’s cost growth benchmarking efforts across the eight states.

Methodology

HMA’s evaluation for the Peterson Center on Healthcare included a detailed landscape review for each of the eight states and interviews with 45 state officials, providers, payers, and other stakeholders in these states. The HMA team synthesized findings from the landscape review and the key informant interviews and produced an internal evaluation report.

Analytic Approach

The landscape review captured the state’s CGB program chronology, governance structure, growth targets, enforcement authority, and performance against the target. The interviews examined the contextual factors, stakeholder influence, implementation developments, capacity to control costs, facilitators and barriers to developing cost control capabilities, and the lessons learned based on the states’ experience. The interview discussion guide included a scoring component which enabled quantitative analysis in addition to the qualitative findings. HMA analyzed these findings by state, category of interviewee (state officials, payers, providers, or others) and implementation stage (early vs. more recent adopters).

Findings

States’ efforts to engage and gather stakeholders, establish cost growth targets, collect and report data, and identify cost drivers have been successful, but states have had challenges to date in developing policies aimed at containing costs.

Utility

The findings from this analysis can be useful to the existing states in enhancing their CGB programs and to states interested in launching new CGB initiatives.

Medicare Hospital Inpatient Device-Intensive Payment Policy

Download

Medicare’s fee-for-service (FFS) payment system includes payment policies that support providers’ use of innovative medical device technologies. The continued evolution of these policies is necessary to keep pace with current and future medical innovation. In this report, HMA summarizes models testing the implementation of a newly proposed policy for the hospital inpatient system which aims to eliminate systemic bias that may slow hospitals’ adoption of innovative technologies. HMA concludes that targeted policies that eliminate the use of the hospital wage index to standardize device costs can result in more accurate reimbursement for hospitals and increase beneficiary access to innovative technologies.

340B Duplicate Discounts: Enforcement Inconsistent and Weak Due to Lack of Data Transparency and Despite Federal Prohibition

Download

At the intersection of the federal 340B Drug Pricing program and the federal Medicaid Drug Rebate Program (MDRP), a potentially large set of Medicaid claims are generating duplicate discounts, which pharmaceutical manufacturers provide to eligible entities such as hospitals and health centers. These two complex federal programs were designed to reduce the costs of prescription drugs for providers that serve low-income patients, but both state Medicaid agencies and federal policymakers have been actively working to eliminate the unintended overlap of these two programs. To gain deeper insights into why duplicate discounts continue to occur, the scope of this concern, and to identify considerations of future policymaking, HMA conducted interviews with Medicaid officials and drug policy experts across several states.

Duplicate discounts occur when for a single sale a manufacturer is required to: (1) prospectively reduce the price of the product (a discount) they sell to a 340B covered entity in advance of the delivery of care to the patient; and (2) provide a retrospective payment (a rebate) to a state Medicaid program or managed care plan under the MDRP after care is delivered to a Medicaid enrollee. When duplicate discounts occur the manufacturer’s product is discounted twice for the same sale, contravening federal law, which prohibits duplicate discounts.

Despite the statutory prohibition, duplicate discounts remain a concern. Both state and federal policymakers have been actively addressing duplicate discounts but have been unable to identify clear and consistent policy solutions that neutralize this inefficiency. On the state level, Medicaid agencies and state legislatures have implemented policies to address duplicate discounts. On the federal level, the Health Resources and Services Administration (HRSA) and the Centers for Medicare & Medicaid Services (CMS) have conducted audits and published best practices for states to eliminate duplicate discounts. Nonetheless, duplicate discounts persist. 

To gain deeper insights into how Medicaid agencies navigate duplicate discounts, Health Management Associates (HMA) conducted semi-structured interviews with former and current Medicaid directors and pharmaceutical policy experts in 14 states. Interviewees were asked about the frequency of duplicate discounts, the extent to which Medicaid agencies devote resources to tracking them, the policies states have implemented to address them, and the extent to which state or federal authorities are working to eliminate duplicate discounts.

Based on interviews, four key themes emerged:

  • Duplicate discounts remain a problem, the scope of the problem is unclear, and better data collection from covered entities is necessary.
  • The opacity and complexity of duplicate discounts create a burden for state Medicaid agencies, influencing the policies they implement, resulting in variable state policy strategies.
  • Contract pharmacies add an additional layer of complexity, exacerbating the burden that duplicate discounts create.
  • State and federal authorities could take more decisive action to address duplicate discounts.

Policymakers should consider that the environment for addressing duplicate discounts may become more complex in the future, which may increase the need for a federally coordinated policy solution. The complexity of the environment may deepen due to the increasing presence of contract pharmacies, the increasing presence of managed care in Medicaid programs, and the implementation of the drug pricing policies of the Inflation Reduction Act of 2022. Policy action coordinated across the various stakeholders (e.g., HRSA, CMS, state Medicaid agencies, covered entities, and manufacturers) may represent the best opportunity for success in eliminating duplicate discounts.

CMS Releases Final 2026 Marketplace Benefit and Payment Parameters

Read Blog

Trump Administration and Congress to Consider Policy Changes

This week, our In Focus section reviews the final Notice of Benefit and Payment Parameters (NBPP) for 2026. The Centers for Medicare & Medicaid Services (CMS) rule, released January 13, 2025, describes the policy and payment parameters for issuers that participate in federally facilitated and state-based marketplaces in 2026.

The NBPP is particularly notable given that marketplace enrollment is at an all-time high. Last week, CMS reported that 24.2 million people joined a marketplace plan during 2025 Open Enrollment, exceeding last year’s historically high enrollment levels by more than 2 million people.[1] With millions more individuals covered in the individual market, this final rule presents several opportunities for the healthcare industry to improve the well-being of covered individuals and families and the financial health of participating organizations.

Marketplace policies are under scrutiny, however, from new Trump Administration officials and congressional leaders. Subsidies, eligibility, and reimbursement are among the topics receiving the greatest attention.

Key highlights from the final rule and considerations for stakeholders in the changing healthcare landscape follow.

Consumer Protections

The final rule further strengthens consumer protections, consistent with the policies advanced during the Biden Administration. CMS finalized policies to achieve the following:

  • Protect consumers from agents and brokers seeking to make unauthorized changes to their healthcare coverage
  • Allow the agency to take enforcement actions against lead insurance agents for violations of marketplace standards
  • Expand the agency’s authority to immediately suspend an agent or a broker’s ability to make transactions within the marketplace if the information creates an unacceptable risk to the accuracy of marketplace eligibility determinations, operations, applicants, or enrollees, or marketplace IT systems
  • Update the model consent form, which helps agents and brokers document consent from consumers to assist with their marketplace enrollments and submission of marketplace eligibility applications

Revisions to Marketplace User Fees

The enhanced premium tax credits are the driving force behind the increase in nationwide marketplace enrollment to more than 24 million today from 11.4 million in 2020. If not extended, or if Congress takes no action by July 31, 2025, CMS will increase the user fees collected to pay for administration of HealthCare.gov as follows:

  • Increase fees to 2.5 percent of monthly premiums in 2026 for federally facilitated marketplaces (FFM) states, up from 1.5 percent in 2025
  • Increase fees to 2.0 percent of monthly in 2026 for state-based marketplaces on the federal platform (SBM-FPs)—up from 1.2 percent in 2025

CMS also is finalizing an alternative set of user fee rates. If enhanced premium tax credit subsidies are extended through the 2026 benefit year by July 2025 at the current or a higher level the following user fees rates will apply:

  • 2 percent for FFM states
  • 1.8 percent for SBM-FPs

CMS originally proposed a March 2025 subsidy extension deadline for activating the lower user fee. Insurer should take into account the higher user fees when setting their 2026 premiums—SBMs as they finalize their 2026 user fee levels and FFM states considering the costs of staying in Healthcare.gov or transitioning to a SBM.

Premium Payment Threshold Options

CMS finalized new options for insurers to avoid triggering late payment grace periods for members who make most but not all their premium payment. The new threshold options are intended to minimize termination of coverage for people who owe small amounts. The options include:

  • For the first month’s premium payment to effectuate coverage—or binder payments—the only option is to use a net premium threshold as low as 95 percent
  • For all other premium payments after the first month’s payment, the options include:
    • Net premiums as low as 95 percent or a fixed dollar threshold of up to $10
    • Gross premiums percent of as low as 98 percent or fixed dollar threshold of up to $10

Fixed dollar thresholds will be adjusted for inflation.

Information Sharing and Transparency

CMS is finalizing policies designed to increase transparency and promote program improvements by publicly releasing state marketplace operations data, including spending on outreach and additional open enrollment customer service metrics, such as for call center performance surveys and website visits. The final rule clarifies that CMS will not publicly release each SBM’s annual State-based Marketplace Annual Reporting Tool (SMART), a reversal from what was proposed.

In addition, CMS is finalizing that it will share aggregated, summary-level Quality Improvement Strategy (QIS) information publicly on an annual basis starting January 1, 2026, with data submitted during the 2025 qualified health plan application period.

What’s Next/Key Considerations

The new leadership at the US Department of Health and Human Services (HHS) and CMS will likely conduct a thorough review of these payment and policy changes. In consideration of potential repeals or modifications, states and marketplace plans will need to consider the following:

  • Uncertainty around extending or modifying Affordable Care Act subsidies
  • Potential statutory changes approved by Congress and regulatory changes from the Trump Administration
  • Review of existing operations and policies in light of the new regulations and the changing policy environment

Connect With Us

Health Management Associates experts support states, managed care organizations, consumer groups, and other interested stakeholders to achieve success in the operation of and participation in the marketplaces. Our team has the broadest historical perspective on the challenges and opportunities in this market and can support every step of the planning and execution processes to optimize markets as they continue to evolve in the coming months and years. If you have questions or want to discuss the final rule, contact our experts below.

[1] Centers for Medicare & Medicaid Services. Over 24 Million Consumers Selected Affordable Health Coverage in ACA Marketplace for 2025. January 17, 2025. Available at: https://www.cms.gov/newsroom/press-releases/over-24-million-consumers-selected-affordable-health-coverage-aca-marketplace-2025.

CMS Stays the Course with Proposed Payment Updates for Medicare Advantage and Part D Services in 2026

Read Blog

Trump Administration will Issue Final Policies

This week, our In Focus section examines the Centers for Medicare & Medicaid Services (CMS) calendar year (CY) 2026 Advance Notice for the Medicare Advantage (MA) and Medicare Part D programs, published January 10, 2025. That same day, CMS also released draft CY 2026 Part D Redesign Program Instructions. This regulatory guidance includes CY 2026 payment updates as well as additional technical and methodological changes to MA and Part D for the coming plan year.

The release of the CY 2026 Advance Notice—along with the complementary CMS policy and technical proposed rule released in November 2024—represent the last major Medicare regulations of the Biden Administration, and these annual payment and policy updates will be finalized under the incoming Trump Administration. As a result, the proposed MA and Part D payment policies could be modified before finalization in April 2025.

Comments on the Advance Notice are due by February 10, 2025, leaving a tight timeline for MA plans and other stakeholders to provide formal feedback and written comments to CMS. Following are brief summaries of the major proposals in the Advance Notice and key considerations for stakeholders as they analyze the proposals.

Payment Impact on Medicare Advantage Organizations

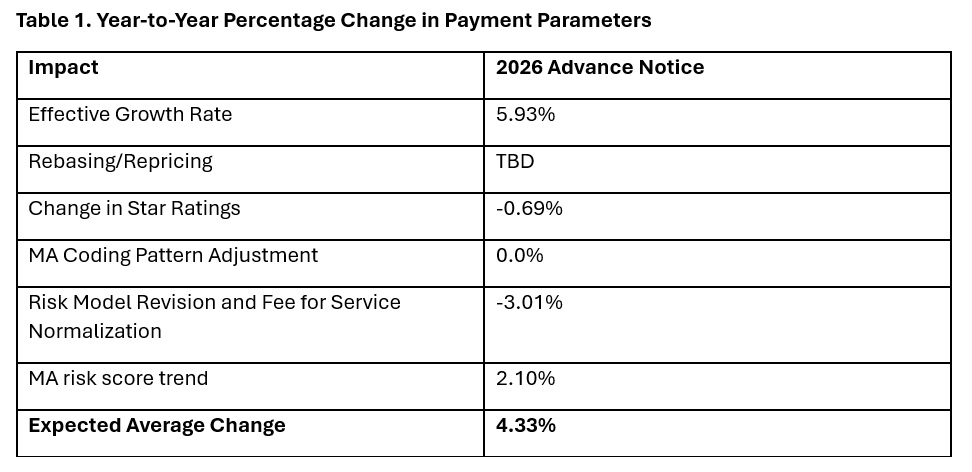
In the Advance Notice, CMS projects that federal payments to MA plans will increase by 4.33 percent from 2025 to 2026—which represents a $21 billion increase in expected payments to MA plans next year. CMS estimates that federal payments to MA plans in 2026 will total $590.9 billion.

The proposed increase in payments accounts for several factors, including growth rates in underlying costs, changes to MA Star Ratings, continued implementation of the new risk adjustment model, and MA risk score trends. The estimated growth rate considers demographic changes in MA enrollment, including projected increases in the number of enrollees.

The Advance Notice estimates represent the average increase in payments to MA plans and actual payments will vary from plan to plan. Below, Table 1 provides estimates of the impact of proposed policy changes on net MA plan payments.

MA Risk Adjustment Changes

CMS intends to complete the three-year phase-in of the MA risk adjustment model that was first published in the CY 2024 Rate Announcement. Specifically, CMS proposes to calculate 100 percent of the risk scores using the new MA risk adjustment model, referred to as the 2024 hierarchical condition categories (CMS-HCC) framework. CMS maintains that the changes to the methodology for calculating risk have improved the predictive accuracy of the model while ensuring risk-adjusted payments to MA plans are accurate.

In addition, CMS has been working to calibrate the risk adjustment model based on MA encounter data, and CMS proposes to begin phasing in an encounter-based MA risk adjustment model as soon as CY 2027.

CMS also proposes to apply the statutory minimum MA coding pattern difference adjustment factor of 5.90 percent for CY 2026.

Technical Adjustment to Cost Calculations Related to Medical Education Costs

Similar to changes in the MA risk adjustment model, CMS plans to complete the three-year phase-in of technical adjustments to the per capita cost calculations related to indirect and direct medical education costs associated with services delivered to MA beneficiaries. This technical adjustment—finalized in the CY 2024 Rate Announcement—has reduced growth rates for MA plans because of the removal of MA-related medical education costs from the benchmarks.

MA Star Ratings

CMS reiterates its continued focus on moving toward a “Universal Foundation” of measures with the goal of creating metrics that center on clinical care, patient outcomes, and improved patient experiences and are aligned across CMS programs. In addition, CMS is soliciting initial feedback on both substantive measure specification updates as well as comments on new measure concepts. CMS also is seeking stakeholder feedback on modifications to the Health Equity Index, including adding social risk factors and geography (urban or rural) to the reward factor. Any specific changes to MA Star Ratings measures, including modifications to the Health Equity Index, would occur through the formal rulemaking process.

Medicare Part D Provisions

The CY 2026 Advance Notice and the CY 2026 Draft Part D Redesign Program Instructions include several payment and benefit updates as required in the Inflation Reduction Act (IRA) of 2022. The CY 2026 updates include:

  • The CY 2026 annual out-of-pocket cost threshold for Part D covered drugs is $2,100, which is the original out-of-pocket cap of $2,000 adjusted for the annual percentage increase in average expenditures for Part D covered drugs
  • Establishment of the selected drug subsidy program
  • Changes to the liability of enrollees, plan sponsors, drug manufacturers, and CMS in the standard Part D benefit design, specifically to account for the start of the Medicare Drug Price Negotiation Program in 2026
  • Guidance on the successor regulation exception to the IRA’s formulary inclusion requirement for selected drugs under the Medicare Drug Price Negotiation Program

Other previously implemented IRA reforms will continue in CY 2026, including no cost sharing for Medicare beneficiaries for Part D covered drugs in the catastrophic phase, which begins after the annual out-of-pocket threshold of $2,100 is reached; a $35 monthly cap on enrollee cost sharing for insulin; no cost sharing for adult vaccines recommended by the Centers for Disease Control and Prevention’s (CDC’s) Advisory Commission on Immunization Practices and covered under Part D; and the requirement for Part D plans to offer the Medicare Prescription Payment Plan to beneficiaries.

What to Expect

The CY 2026 Advance Notice includes important technical, programmatic changes and payment updates for MA and Part D plans, which will be finalized when CMS publishes the final CY 2026 Rate Announcement on or before April 7, 2025. MA plans and other stakeholders have a rigid timeframe to provide formal input and written comments to CMS before the February 10 deadline.

Like the policy and technical changes included in the MA proposed rule, the CMS Advance Notice payment updates will be finalized under the incoming Trump Administration. MA plans and other stakeholder can anticipate that the new leadership at the US Department of Health and Human Services and CMS will closely examine and take a fresh look at the proposed payment and policy changes. Though the current CMS leadership maintains that payment updates included in the Advance Notice are sufficient to support stability in MA premiums and benefits, proposed payment policies can be modified or delayed as the new leadership takes shape.

For example, officials in the Trump Administration could seek to delay the phase in of the risk adjustment changes as well as the technical adjustment regarding medical education costs, which CMS estimates would result in an additional $10.4 billion in payments to MA plans.

Connect With Us

Medicare experts at Health Management Associates, will continue to assess and analyze the policy and political landscape, which will determine the final policies included in the CY 2026 Rate Announcement. HMA experts have the depth of knowledge, experience, and subject matter expertise to assist organizations that engage in the rulemaking process and to support implementation of final policies, including policy development, tailored analysis, and modeling capabilities.

For details about the CY 2026 MA Advance Notice and its impact on MA and Part D plans, providers, and beneficiaries, contact our featured experts below.

MyCare Ohio: The Next Generation’s Impact on the Ohio Medicare and Medicaid Landscape

Read Blog

This week, our In Focus section also reviews the significant efforts under way in Ohio to transform how the state provides healthcare services to its Medicare and Medicaid dual-eligible population. Effective January 1, 2026, MyCare Ohio will transition to the Next Generation of its program for people who are dually eligible for both programs.

Overview of Ohio’s Transition to Next Generation MyCare Ohio

This evolution moves Ohio to a fully integrated dual-eligible special needs plan (FIDE-SNP) model that seeks to achieve several key goals through a population-based health approach designed to address inequities and disparities in care for dual-eligible individuals. Examples include:

  • Improved Care Coordination: Strengthening integration between Medicare and Medicaid services to provide seamless, holistic care for individuals, thereby reducing fragmentation and ensuring comprehensive management of medical, behavioral, and social needs
  • Personalized Care: Applying data analytics and technology to create more tailored care plans, with a focus on proactive care to address the unique health needs of each individual, especially people with chronic conditions
  • Expanded Access to Services: Increasing accessibility, particularly through telehealth and digital tools, to reach underserved populations and improve accessibility, particularly for people living in rural or remote regions
  • Enhanced Quality of Care: Shifting focus from service volume to outcomes, encouraging providers to deliver high-quality care and improve patient satisfaction, while incentivizing preventive care to reduce hospital admissions and other high-cost interventions
  • Technology Integration: Leveraging advanced technologies like mobile apps, predictive analytics, and telemedicine to monitor patient health, improve communication between patients and providers, and deliver care more efficiently

The MyCare program currently is offered in 29 counties across Ohio but will transition to a statewide program as a part of the Next Generation changes. In addition, coordination only dual-eligible special needs plans (CO-DSNP) will no longer be permitted.

After the Ohio Department of Medicaid (ODM) publicly released the request for applications and evaluated submitted proposals, the agency selected four managed care organizations (MCOs), which will become the Next Generation MyCare plans. The ODM awarded contracts to the following MCOs that will serve MyCare members beginning in January 2026: Anthem Blue Cross and Blue Shield, Buckeye Health Plan, CareSource, and Molina HealthCare of Ohio.

Considerations for the Market

The shift to the FIDE-SNP model and selection of four participating health plans will have a considerable impact on the competitive landscape for Medicare and Medicaid managed care in Ohio. The resulting changes may affect both selected and non-selected participants in different ways, including:

  • Increased competition among MyCare MCOs: MCOs will need to focus on enhancing their care coordination systems, adopting new technologies, and developing personalized care plans to compete not just in terms of the volume of services provided, but also to the quality and effectiveness of healthcare delivery. Those plans that can best integrate services, offer proactive care management, and improve patient outcomes through value-based care and advanced technology initiatives will gain the competitive advantage, potentially attracting more beneficiaries.
  • Strategic responses of nonparticipating MCOs to counter potential membership and financial losses: MCOs that lose members because they were not selected or are unable to offer CO-DSNPs moving forward, will likely strategize to gain membership through other product lines or benefit design to offset losses. Strategies may vary but might include tactics such as: enhancing benefits or decreasing member cost sharing to entice member movement across carriers for non-D-SNP plans; finding innovative ways to further reach different segments of the Medicare population, such as Special Supplemental Benefits for the Chronically Ill (SSBCI) packages or Chronic Condition SNP plans; or shifting their focus to product lines outside of Medicare Advantage and Medicaid.

Connect with Us

Ohio is one of many states transitioning to a FIDE model beginning January 2026. Health Management Associates, Inc. (HMA), has successfully supported participating and nonparticipating carriers throughout the transition process and continues to be a dedicated partner to organizations navigating Medicare and Medicaid changes across the country.

Contact our featured experts below, to learn more about the Ohio FIDE-SNP initiative and HMA’s capabilities and expertise to support states, carriers, and other key partners with these transitions.

Ready to talk?