Insights

HMA Insights: Your source for healthcare news, ideas and analysis.

HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.

or
or
Receive timely expert insights on topics you care about.

257 Results found.

President Issues Executive Order Calling for Most Favored Nation Drug Pricing

Read Blog

On May 12, 2025, the President signed an Executive Order (EO), Delivering Most-Favored-Nation Prescription Drug Pricing to American Patients.” The EO calls for or, in some cases, presumes a range of manufacturer, administrative and regulatory actions to reduce drug prices, but ultimate outcome remains unclear.

HMA experts, including Leavitt Partners, an HMA company, are closely following executive agency and stakeholder responses to the EO. In this article, our experts summarize the EO and identify key considerations for healthcare stakeholders.

Policy Overview

Since his first administration, President Trump has consistently criticized disparities in brand-name prescription drug prices between the United States and other developed countries. In 2018, the previous Trump Administration issued a preliminary proposal to institute an International Pricing Index (IPI) model targeting Medicare payments for a subset of clinician-administered drugs. The IPI model would have set a Medicare payment amount for select Part B drugs at a lower amount to align with international prices and allow for negotiation of prices, while still providing a drug add-on payment to providers consistent with historical drug costs.  In November 2020, the administration issued an interim final rule (IFR) instituting an escalated version of this concept, entitled the Most Favored Nation (MFN) Model. Both the IPI proposal and the MFN final rule, the latter of which was enjoined by the courts on largely procedural grounds and later rescinded by the Biden administration, would have been implemented under the Center for Medicare and Medicaid Innovation’s (CMMI) demonstration authority.

On May 12, 2025, the President signed an EO, Delivering Most-Favored-Nation Prescription Drug Pricing to American Patients, which reaffirms the Administration’s concerns regarding what it perceives to be American funding of pharmaceutical research and development “while foreign health systems get a free ride.” In an effort to address the Administration’s concerns, the EO notes that the Administration “will take immediate steps to end global freeloading” and that “should drug manufacturers fail to offer American consumers the most-favored-nation lowest price, my Administration will take additional aggressive action.”

The EO outlines efforts to implement this policy, including:

  • Trade Efforts. The US Department of Commerce and United States Trade Representative (USTR) are directed to ensure that foreign countries are not engaged in actions with the effect of forcing Americans to “pay for a disproportionate amount” of R&D costs.
  • Direct-to-Consumer (DTC) Sales at MFN Price. The US Department of Health and Human Services (HHS) is directed to facilitate DTC sales programs for manufacturers to offer MFN prices.
  • MFN Targets. The HHS Secretary is directed to provide MFN targets to manufacturers within 30 days with the expectation that manufacturers will “bring prices for American patients in line with comparably developed nations.”
  • If “significant progress” toward MFN pricing is not made, HHS will be directed to propose a rulemaking plan to impose it.
  • The order suggests that the HHS Secretary certify, on a case-by-case basis, that reimportation will pose no additional risk to public health and will result in savings, as well as to create standard mechanisms for importation. It is unclear how this direction aligns with the current statutory framework, which is focused on Canada.
  • Federal Trade Commission/Department of Justice Action. The EO calls for efforts “consistent with law” to undertake enforcement action against anticompetitive practices identified in the prior drug pricing EO, including use of the Sherman Antitrust Act.

Key Considerations

At this stage, the scope and practical effects of the EO remain uncertain, as the administration has not yet provided details regarding the regulatory and subregulatory actions envisioned under the document. With respect to trade policy, for instance, the EO does not outline explicitly what particular tools it expects USTR or the Commerce Department to leverage in combating “foreign freeloading.”

Similarly, the EO does not elaborate on the steps that the administration plans to take in “facilitat[ing]” voluntary MFN target pricing under DTC purchasing arrangements. Such efforts could theoretically bring waivers or other regulatory flexibilities to bear, or else they could take a more hands-off approach, simply encouraging drugmakers to take action on their own.

Without further clarifications around how the administration might define or assess “significant progress” towards MFN pricing targets on the part of manufacturers, nor the form, manner, or timeline that “aggressive action” in the absence of such progress might take, the EO serves principally as an illustration of the President’s posture, perspective, and priorities with respect to prescription drug affordability and access.

Even in the absence of immediate pricing or payment interventions, the EO could provide a preview of future executive actions aligned with the document’s focus. Such actions could include CMMI models building on the IPI or MFN initiatives from the first term, explicit trade negotiation priorities, regulatory measures related to DTC purchasing arrangements, FDA reimportation program flexibilities, or any number of other drug-related policies.

Our experts will continue to monitor these activities as they progress.

Connect With Us

For details regarding the EO and potential impact on the healthcare sector, contact our featured experts below at [email protected]

House Committees Consider Policies to Meet Budget Reconciliation Instructions

Read Blog

This week, key committees in the House of Representatives released recommendations for legislative language that meets their federal savings and spending targets required in the fiscal year (FY) 2025 budget resolution. On May 11, 2025, the House Energy and Commerce Committee released legislation—and subsequently a substitute amendment—that contains several substantive Medicaid proposals designed to address eligibility and enrollment; financing; fraud waste, and abuse; and to institute mandatory work and community engagement requirements and cost sharing. The Committee completed its markup on May 14, 2025, voting to approve the provisions in the substitute amendment.

The release of text and committee markups are key steps in Congress’s budget reconciliation process; however, proposals may change during Senate proceedings.

Health Management Associates (HMA), and Leavitt Partners, an HMA company, are tracking these developments and analyzing the extensive health and health-related legislative text, including the Medicaid, Medicare, and Affordable Care Act (ACA) Marketplace proposals. Below, we review the status of congressional efforts and key policies.

Background

The budget reconciliation process is a powerful tool for enacting significant fiscal policy changes, as it allows for expedited consideration and passage of budget-related legislation. It has been used in the past to enact major tax reforms, healthcare legislation, and other important budgetary measures.

In 2025, Congress has been actively working to develop its budget bills through a series of steps. The House adopted a budget resolution on February 25, 2025, which sets the framework for federal spending, revenue, and the debt limit for fiscal year 2025 and outlines budgetary levels for the following years through 2034. The Senate passed an amended version of the budget resolution on April 5, 2025. The Senate’s amendments included reconciliation instructions that require $4 billion in gross deficit reductions and allow a $5.8 trillion net deficit increase. On April 10, 2025, the House agreed to the Senate’s amendments with a vote of 216−214. This agreement set the stage for the development of a reconciliation bill.

House Energy and Commerce Markup

On May 14, 2025, the House Committee on Energy and Commerce completed its second day of marking up legislative language to comply with the Concurrent Resolution on the Budget for Fiscal Year 2025, voting to advance the proposals out of committee. The committee’s proposal excluded certain significant structural reforms that had generated concern among some members and stakeholders, such as broad reductions in the federal matching rate (enhanced federal matching assistance percentage (FMAP)) for Medicaid expansion populations, per-capita caps on federal Medicaid cost growth, or reductions in the safe harbor threshold for state Medicaid provider taxes. The proposal does, however, contain more than a dozen provisions that would reduce federal health care spending by $715 billion with the funding reductions mostly focused on Medicaid, which the Congressional Budget Office projects will reduce the federal share of Medicaid spending, including:

  • Adding mandatory work and community engagement requirements for individuals ages 19−64 without dependents, subject to exceptions for pregnant women, people who are medically frail, people with disabilities, people in compliance with other government program work requirements, people living in areas experiencing a temporary hardship, and other individuals
  • Adding cost sharing for beneficiaries in the expansion population who earn more than 100 percent of the Federal Poverty Level, not to exceed $35 per item or service
  • Pausing implementation of several final rules published during the Biden Administration, including: the final rule published September 21, 2023, “Streamlining Medicaid; Medicare Savings Program Eligibility Determination and Enrollment”; the April 2, 2024 rule, “Streamlining the Medicaid, Children’s Health Insurance Program, and Basic Health Program Application, Eligibility Determination, Enrollment, and Renewal Processes”; and the May 10, 2024, final rule, “Minimum Staffing Standards for Long Term Care Facilities and Medicaid Institutional Payment Transparency Reporting”
  • Adding provider screening requirements
  • Increasing frequency of eligibility redeterminations for certain individuals and adding enrollee address verification policies
  • Reducing expansion FMAP for certain states that provide Medicaid coverage to undocumented individuals and families, regardless of the source of funding
  • Preventing certain spread pricing arrangements in Medicaid between states and pharmacy benefit managers
  • Restricting funding for certain essential community providers that furnish family planning services, reproductive health, and related healthcare services
  • Ending a temporary increased FMAP to new states adopting Medicaid expansion, revising policies governing the use of Medicaid provider taxes, and payment limits for state directed payments

Committee Markups

Various other House committees have begun holding markups for the reconciliation package. The Committee on Ways and Means conducted its markup on May 13, 2025, to discuss its portion of the reconciliation bill, which involves $4.5 trillion in deficit increases. The initial Ways and Means proposal did not include many significant healthcare proposals, but on May 12, 2025, the committee released a substitute amendment that includes several changes that would affect private insurance coverage and Medicare. Key provisions include:

  • Changes to Medicare and ACA premium tax credit (PTC) eligibility requirements related to immigration status
  • Improvements to ACA PTC eligibility verification checks
  • Changes to Health Savings Account flexibilities
  • Codification and renaming of individual coverage health reimbursement accounts, which serve as a defined contribution that employees can use to purchase insurance in the individual market

Other committees, such as the Education and Workforce, Judiciary, Armed Services, and Homeland Security Committees, also have conducted markups and approved their respective portions of the reconciliation bill.

Connect With Us

These steps are part of the ongoing process to finalize the budget and reconciliation legislation for FY 2025. Our federal policy experts with Leavitt Partners and across HMA are monitoring the legislative policies and ongoing negotiations in Congress and with the administration. They work with healthcare organizations and industry to plan for the range of scenarios and policies Congress is debating.

For more information about the impact of these policies, contact our featured federal policy experts below.

Preparing for Change: The TEAM Model and what Medicare’s 2026 Inpatient Proposed Rule Means for Hospitals

Read Blog

This week, in our In Focus section, Health Management Associates’ Medicare experts review the changes to the Center for Medicare and Medicaid Innovation’s (CMMI) Transforming Episode Accountability Model (TEAM) proposed in the Fiscal Year (FY) 2026 Medicare Hospital Inpatient Prospective Payment System (IPPS) and Long-Term Acute Care Hospital (LTCH) Proposed Rule (CMS-1833-P). The IPPS proposed rule, released April 11, 2025, maintains the model with no changes to the timeline, participants, accountable care organization overlap policies, or required episodes.

While most changes are technical in nature, involve minor methodological tweaks, or seek to align with the Trump Administration’s policy priorities, stakeholders should continue to assess their readiness and prepare to implement the TEAM model. This is a critical time for healthcare stakeholders to stay on top of this specific proposed rule, the TEAM model, and other federal and state-level developments that are affecting the healthcare system.

This article reviews key aspects of the IPPS proposed rule policies related to TEAM with strategic steps for stakeholders as they continue to prepare for the model’s implementation.

Background on TEAM

TEAM is a value-based care initiative that requires participating hospitals to manage costs for a range of surgical procedures, including both inpatient and outpatient services. The program involves bundled payments covering all aspects of care from the surgical procedure itself to most post-acute care occurring within a 30-day window following discharge from the hospital. Payments will be calculated based on regional benchmarks, and hospitals will assume financial responsibility for the quality and cost of care provided.

TEAM is scheduled to begin in 2026 with 741 hospitals required to enter into value-based arrangements. The program will affect how hospitals manage five types of surgical episodes in both the inpatient and outpatient hospital setting by shifting more risk to the hospitals themselves. This risk includes not only the cost of the surgery but also post-acute care, including readmissions, complications, and downstream provider services. The goal is to incentivize hospitals to improve care coordination, reduce costs, and enhance patient outcomes.

Proposed Changes to the Model

According to the proposed changes, CMS is moving forward with the five-year mandatory model largely as planned, with minor updates focusing on technical details rather than a significant overhaul. Some of the proposed changes were expected based on the administration’s policy priorities, including removal of:

  • The Decarbonization and Resilience Initiative
  • Health equity plans
  • Health-related social needs data reporting

Other technical changes address flexibility for newly opened hospitals within TEAM’s required geographies, the impact of the possible expiration of the Medicare Dependent Hospital (MDH) program, and modified episode attribution to be based on discharge date, rather than start date. CMS is also still seeking comment on how to finalize the low-volume threshold policy, where hospitals under a certain number of procedures would only have Track 1 (upside only) applied.

Overall, CMS expects that its proposed changes to TEAM “should not result in dramatic shifts to the Medicare savings estimate” of $481 million in savings to CMS across the model’s five performance years.

Stakeholder Considerations for the Future

Keeping this model largely intact and maintaining the mandatory nature signals that the Trump Administration intends to continue with value-based arrangements and is looking for ways to achieve program savings. A mandatory model will generally achieve a higher level of savings than a voluntary one.

As they prepare for implementation, stakeholders will need to take action, including:

  • Thoroughly reviewing the proposed changes to the TEAM model to understand the changes and their implications to model of care policies and operations, financing, and collaborations with clinicians and care teams outside of the facility. Consider submitting comments to CMS on the proposed changes. Review the list of hospitals in TEAM.
  • Contextualizing their work to implement this model alongside other pending federal and state policy changes. Stakeholders will benefit from staying on top of developments in this dynamic policy landscape since many pending proposals have financial and structural implications for healthcare providers.
  • Preparing for the mandatory model by developing strategies to manage the financial risk associated with the bundled payments and improving care coordination. This may include modeling hospital payment policies and assessing the implications of the proposed changes.
  • Assessing the system and technology changes and collaborations that will be required to effectively manage risk in the model.

Connect With Us

Health Management Associates’ (HMA’s) Medicare Practice Group monitors federal regulatory and legislative developments in the inpatient setting and assesses the impact on hospitals, life science companies, and other stakeholders. Our experts interpret and model hospital payment policies and assist clients in developing CMS comment letters and long-term strategic plans. Our team replicates CMS payment methodologies and model alternative policies using the most current Medicare fee-for-service and Medicare Advantage claims data. We also support clients with Diagnosis Related Group (DRG) reassignment requests, new technology add-on payments (NTAP) applications, and analyses of Innovation Center alternative payment models.

For more information about the proposed policies, contact our featured experts below.

Transforming Medicare: Key Developments and Future Trends 

Read Blog

April is always a busy month for Medicare. It is the month when Medicare Advantage (MA) policies get finalized and the bid season moves into the final stretch. It is also the starting month for annual rule making for the next cycle of Medicare payment rules. These provide important signals about the Center for Medicare & Medicaid Services (CMS) plans for modernizing Medicare’s quality programs and commitment to value-based care. 

This month, we’ve highlighted the work that HMA’s federal policy experts do to support organizations’ Medicare projects. We’ve discussed our experts’ ability to support organizations with the transition to digital quality measures. Our experts were on top of policies that made it into final MA rate notices and policy rules. We also flagged what wasn’t included and what this may mean for the future of Medicare policy. We examined the notable policy proposals in Medicare payment rules for inpatient hospitals and how these are a “canary in the coal mine” for other upcoming rules, especially related to making quality reporting and measurement more efficient and actionable. And we asked whether Medicare is ready for the next era of innovation?  

We are at the start of a new season of priority setting for CMS. Early signals of what will be important to policy officials include alignment with the Make America Healthy Again (MAHA) initiative, digital health, transparency, and addressing fraud. 

Impact of Recent Policy Changes 

Recent policy changes have impacted the Medicare landscape in various ways. Changes announced in recent Medicare Advantage and Part D rate notices and policy include updates to payment models, quality reporting requirements, and measures to enhance transparency and accountability. The focus on digital health and the integration of digital tools into clinical models are reshaping how care is delivered and measured. Additionally, the emergent emphasis on chronic disease and program integrity is driving organizations to take a fresh look at their data, models of care, and strategies for collaborating with partners to improve patient care. Staying informed and adapting to these policy changes is crucial for organizations to remain competitive and deliver high-quality care to Medicare beneficiaries. 

The Future of Medicare 

Medicare will continue to play a vital role in providing healthcare to the more than 68 million beneficiaries in the program, as it is poised for significant transformation through the integration of digital tools, increased focus on quality care, and the need for cost efficiency in both Medicare Advantage and in Fee-for-Service Medicare. Organizations that stay ahead of these changes and align with policy priorities will be well-positioned to drive meaningful improvements and ensure the sustainability of the program. 

As we look ahead, the commitment to innovation, transparency, and quality will be key to shaping the future of Medicare. HMA is helping clients navigate this dynamic landscape in Medicare Advantage, integrated care programs for dual eligibles, Medicare Advantage Stars and Medicare value-based care programs, PACE, and rural-focused health by providing actuarial support, long term strategic plans for data and quality initiatives, modeling of payment policies, and analyses of alternative payment models.   

If you missed it, watch the replay of our Medicare Town Hall from Wednesday April 30th. And to learn more about our work in Medicare, read our recent blog post Navigating Uncertainty in Medicare and other Federal Health Programs or visit our Medicare page. Our policy team, actuaries, clinicians and digital quality experts are ready to help advance your Medicare projects. Contact us at [email protected]

Helping organizations navigate the New Technology Add-on Payment (NTAP) Program

Read Blog

Hospitals that use specially designated new technologies in the inpatient setting may receive additional reimbursement through a program offered by the Centers for Medicare & Medicaid Services (CMS) known as the new technology add-on payment (NTAP) program. CMS offers a separate NTAP payment in addition to the regular Medicare Severity-Diagnosis Related Group (MS-DRG) payment, for use of specially designated new technologies that qualify. This payment is meant to remove some of the disincentives faced by hospitals under the bundled inpatient payment system, when the costs of new technologies are not incorporated into the payment rates until two to three years after market entry. At a recent webinar, HMA Principal Clare Mamerow discussed the NTAP program, what manufacturers must do to apply for and receive NTAP designation for their new technologies, and some of the changes coming in 2025. This blog shares some of the key issues raised.  

While NTAP designation can offer manufacturers of new technologies a significant advantage, the NTAP application process can be intense, arcane, and difficult to navigate without proper guidance. Most products applying for NTAP need to meet three criteria: newness, cost, and substantial clinical improvement. Certain other products – breakthrough devices and certain antibiotic and antimicrobial drugs – are deemed to have already met the newness and substantial clinical improvement criteria and therefore, only need to show that the cost criterion is met. This alternative application pathway is significantly streamlined and makes gaining NTAP designation much easier for these special products because the majority of products that fail to meet the three criteria miss substantial clinical improvement. 

The newness criterion has two facets. First, the product must be newly on the market (received FDA approval recently, but prior to May 1, 2026) and must not be “substantially similar” to other available products. CMS looks to whether the product has a different mechanism of action or whether the product treats a new or different disease or patient population in making a substantially similar determination. 

The cost criterion involves an analysis of Medicare claims data, where claims from two years ago are identified as cases where the new product could have been used had it been available and then repriced to account for the cost of the new technology. The average charges on those claims are compared to a DRG specific thresholds that CMS calculates. If the claim charges exceed the threshold, the cost criterion is met.

Finally, the substantial clinical improvement criterion requires that applicants show that patient outcomes are better with treatment with the new technology. Outcomes such as reduced mortality, reduced complications, and reduced health care utilization are all examples of clinical improvement. CMS takes a totality of the circumstances view of substantial clinical improvement, so applicants are encouraged to provide as much data as possible to support their application.

While NTAP can provide supplemental payments in some circumstances, it’s important to understand the program’s limits. The NTAP payment that hospitals receive is calculated on a claim-by-claim basis, with the payment at the lesser of 65% of the cost of the product, or 65% of the cost above the regular DRG payment. This means that hospitals are only made aware of the payment amount after the claim has been submitted, and that the hospital can never be made whole for the use of the new technology.  In addition, the payment can be any amount less than 65% of the cost of the product—it’s even possible that the hospital will receive no payment if the cost of the case isn’t high enough to trigger the payment. Certain antibiotics and gene therapies that treat sickle cell disease receive a high payment, up to 75% of the cost of the product. Additionally, the payments are only applicable to Medicare fee-for-service claims in IPPS hospitals. Medicare Advantage, Medicaid, and commercial hospital claims are not eligible for payments. Finally, NTAP eligibility only extends for 2-3 years after market entry.    

Although the NTAP application deadline for FY 2027 has not yet been announced, manufacturers of new technologies with an interest in NTAP should begin preparing their applications soon. 

HMA experts in Medicare and Life Sciences can partner with your organization navigate the challenges in the NTAP program. If you are interested in learning more, contact us.

Is Medicare Ready for the Next Era of Innovation?

Listen Now

Amy Bassano is a Managing Director at Health Management Associates and a nationally recognized Medicare policy expert. In this episode of Vital Viewpoints on Healthcare, we unpack the complexities of Medicare innovation and examine where the program is headed next. Drawing on decades of experience—including her leadership at the Center for Medicare and Medicaid Innovation—Amy breaks down what makes value-based care so complex, why scaling successful models is harder than it sounds, and how Medicare Advantage continues to reshape the healthcare landscape. She also discusses how financial incentives, regulatory constraints, and the urgent need for system-wide efficiency are shaping the next chapter of Medicare policy. This conversation offers practical insights for policymakers, providers, and advocates navigating the future of one of the nation’s most essential programs. 

The Medicare Advantage VBID Program Is Ending: Here’s What All Plans Can Do to Prepare for What’s Next

Read Blog

This week, our second In Focus article addresses the transition to end the Medicare Advantage Value-Based Insurance Design (VBID) model, which launched in 2017 and subsequently has been expanded with bipartisan support. This model was designed to promote flexible benefit design, reduce cost barriers, and enhance care for targeted populations, especially dual eligibles and individuals with chronic conditions. In December 2024, however, the Centers for Medicare & Medicaid Services (CMS) announced that the model would be terminated by the end of 2025, citing unmitigable costs to the Medicare Trust Funds, totaling more than $4.5 billion across 2021 and 2022 alone​.

Despite its popularity and effectiveness in improving medication adherence and addressing social determinants of health, CMS concluded that the cost trajectory was unsustainable within the parameters of the Innovation Center’s mandate.

The end of the VBID model is not the end of innovation in Medicare Advantage (MA); rather, it is a strategic inflection point. Plans that approach this transition with a proactive, data-driven lens will be best positioned to maintain competitive advantage, compliance, and member trust. This article reviews critical steps VBID plans should be taking and how Medicare Advantage Organizations (MAOs) and their partners can best prepare for future opportunities.

Pain Points and Key Strategic Decisions for MAOs

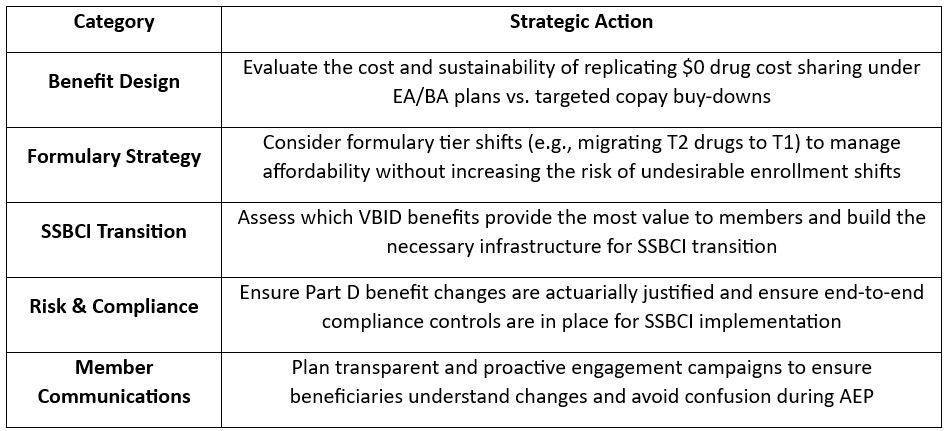
As plans prepare for a post-VBID world, they face a series of complex trade-offs—especially those with Dual Eligible Special Needs Plans (D-SNPs) that had $0 drug cost sharing under VBID. With the end of CMS’s drug cost offset in the initial coverage phase, MAOs will need to determine whether and how to absorb those costs through alternative mechanisms. In addition, plans will need to make important decisions regarding their other VBID benefits, namely, whether to discontinue or transition them to the special supplemental benefits for the chronically ill (SSBCI) program. MAOs should consider the following key strategic decisions:

  • Offer an Enhanced Alternative (EA) or Basic Alternative (BA) Part D Plan: To replicate $0 cost sharing, MAOs would need to use EA or BA plan designs with $0 deductibles and $0 copays across all tiers—an expensive move and potentially untenable investment for many.
  • Tier-Specific Buy-Downs (T1/T2): Some plans may consider buying down T1 and T2 copays to $0, a much less costly approach. Others may consider moving key T2 drugs to T1, while keeping T1 copays at $0 to protect access and using non-zero dollar T2 copays to limit costs.
  • Competitive Alignment Considerations: MAOs offering broader cost-sharing reductions (e.g., $0 copays on both T1 and T2 drugs) may experience undesirable shifts in enrollment patterns depending on how competitors structure their formularies and benefit designs. MAOs should consider competitive parity and attempt to maintain a balanced benefit structure that aligns with market norms.
  • Transferring VBID Benefits to SSBCI: Some benefits—like non-health-related transportation, healthy foods, and general supports for living—could migrate to the SSBCI program. But SSBCI has strict eligibility, documentation, and operational requirements, calling for nuanced workflows and cross-departmental coordination.

Action Plan: What MAOs Should Be Doing Now

To navigate this transition successfully, teams of experts at Wakely, a Health Management Associates, Inc. (HMA) Company, are already working with VBID stakeholders to evaluate multiple transition scenarios. Our experts recommend that MAOs take the following actions:

What to Watch: Future Innovation in Medicare Advantage

Though VBID is ending, the innovation landscape is far from static. With the new Trump Administration and the return of Abe Sutton—a VBID expansion advocate—appointed as Director of the CMS Innovation Center, our experts are closely monitoring the potential for a revised version of VBID or similar models. Stakeholder advocacy could influence how CMS prioritizes the next wave of innovation. Plans should consider engaging in dialogue now to shape what happens next.

Connect with Us

Wakely is embedded in MA strategy and policy. Wakely and HMA teams are working with clients to evaluate multiple transition scenarios, helping them optimize value, protect Star Ratings, and preserve member satisfaction during this pivotal shift, while also supporting targeted policy engagement efforts to ensure their perspectives are reflected in future CMS and Innovation Center decision making.

Our joint capabilities bring together:

  • Actuarial modeling expertise to quantify cost and risk impacts of design alternatives
  • Regulatory insight to ensure compliance with CMS requirements
  • Operational support to help you implement SSBCI programs efficiently
  • Market strategy consulting to align your plan offerings with local competition and enrollment goals
  • Policy advocacy to help clients engage in the conversation around what comes next after VBID

To connect on additional questions contact our featured experts below.

FY 2026 Medicare Hospital Inpatient Proposed Regulation Signals Several Changes Lie Ahead for the Hospital Industry and Beneficiaries

Read Blog

This week, our In Focus section reviews the policy changes that the Centers for Medicare & Medicaid Services (CMS) proposes to make in the Fiscal Year (FY) 2026 Medicare Hospital Inpatient Prospective Payment System (IPPS) and Long-Term Acute Care Hospital (LTCH) Proposed Rule (CMS-1833-P). The IPPS proposed rule, released April 11, 2025, includes several important policy changes that will alter hospital margins and change administrative procedures, beginning as soon as October 1, 2025.

Key Provisions of the FY 2026 Hospital IPPS and LTCH Proposed Rule

For FY 2026, CMS proposes to modify several hospital inpatient payment policies. We highlight and interpret six of these proposed policies that may be among the most impactful for Medicare beneficiaries, hospitals and health systems, payers, and manufacturers, as follows:

  1. Annual inpatient market basket update
  2. Labor share reduction
  3. Medicare Advantage (MA) data integration in measuring hospital readmissions
  4. New Technology Add-on Payment (NTAP) program growth
  5. Transforming Episode Accountability Model (TEAM) modifications
  6. Uncompensated care payment increase for disproportionate share hospitals (DSHs)

Annual Inpatient Market Basket Update

Proposed Rule: CMS’s FY 2026 Medicare IPPS Proposed Rule will increase payments to acute care hospitals overall by 2.4 percent from FY 2025, amounting to an estimated $4 billion increase in reimbursement. This update is based on a hospital market basket increase of 3.2 percent and a 0.8 percent reduction for total factor productivity.

HMA Analysis: CMS’s 2.4 percent increase results from the estimated rate of increase in the cost of a standard basket of hospital goods—the hospital market basket. For beneficiaries, this payment increase will lead to a slightly higher standard Medicare inpatient deductible and an increase in out-of-pocket costs. For hospitals and health systems, payers, and manufacturers, the proposed payment increase (2.4 percent) is consistent with economy-wide inflation over the past year (2.4 percent) and below the amount that MA plans will receive for 2026 (5 percent).[1][2] Although the published payment update for FY 2026 is 2.4 percent, other policy changes result in the average change in inpatient payments totaling slightly more than 3 percent. We anticipate the proposed 2.4 percent increase will increase somewhat by the time CMS finalizes these rates later in the year.

Labor Share Reduction

Proposed Rule: CMS proposes to modify the hospital labor share used to reimburse hospitals for inpatient services. Using 2023 hospital cost report data CMS proposed a national labor‑related share of 66.0 percent, a decrease from the labor share of 67.6 percent.

HMA Analysis: Every five years, CMS recalculates the hospital market basket and the hospital labor share using updated cost data from the hospital cost reports. For FY 2026, CMS conducted its routine rebasing calculation using 2023 cost report data, replacing the 2018 cost data currently used. As a result, CMS calculated that the cost of labor accounts for a slightly smaller share of total hospital costs in 2023 than in 2018. The labor share is used within the IPPS to identify the proportion of payments that are affected by the hospital wage index in an effort to adjust payments for geographic variation in labor costs. The consequence of a lower hospital labor share is that a slightly smaller share of hospital inpatient payments will be adjusted by the hospital wage index. The subtle impact of this change is that hospitals with higher wage index values may experience reductions in payment. Further, this downward revision of the labor share signals that hospital wages, salaries, and employee benefits account for a smaller share of total costs in the post-pandemic environment. This change may come to a surprise to some, as hospital labor costs have been a subject of concern since the COVID-19 public health emergency.

Medicare Advantage Data Integration in Measuring Hospital Readmissions

Proposed Rule: CMS proposed to make several modifications to the Hospital Readmissions Reduction Program (HRRP), including:

  • Refining all six readmission measures to add MA patient data
  • Removing the COVID-19 patient denominator exclusion from measures
  • Reducing the applicable period from three years to two
  • Modifying the DRG payment ratios in the payment adjustment formula to include MA beneficiaries
  • Clarifying that CMS has the discretion to grant an extension to hospitals under the extraordinary circumstances exception (ECE)

CMS also proposed to include MA data in other measures included in the Hospital Value-Based Purchasing (VBP) program and the Inpatient Quality Reporting (IQR) program.

HMA Analysis: The inclusion of MA data in the HRRP may have significant payment implications for many hospitals because it will alter their readmission rates in unanticipated ways, particularly if hospitals’ MA patients differ substantially from traditional Medicare beneficiaries. Importantly, the inclusion of MA data in the HRRP measures, and also within the VBP program and the IQR program, signals that CMS is moving toward broader integration of MA data into Medicare fee-for-service reimbursement systems.

New Technology Add-on Payment Program Growth

Proposed Rule: CMS proposed to continue NTAP status for 26 products because they continue to meet the newness criteria required under this program. In addition, within the proposed rule CMS discusses new NTAP applications for 43 additional products. Among these applications, 29 were submitted under the alternative pathways for breakthrough devices and qualified infectious disease products (QIDP).

HMA Analysis: The overall number of products with NTAPs is on par with other recent years, but the number of NTAP applications has blossomed in FY 2026 as the result of the alternative breakthrough application pathway. This alternative pathway allows breakthrough devices and certain antibiotic and antimicrobial drugs to apply for NTAP using an abbreviated application process.

Transforming Episode Accountability Model Modifications

Proposed Rule: CMS proposed several modifications to the forthcoming CMS Innovation Center TEAM framework. Among the various methodological modifications proposed to this mandatory payment model beginning January 1, 2026, CMS proposed to take the following actions:

  • Limit the deferment period for certain hospitals
  • Replace the Area Deprivation Index (ADI) with the Community Deprivation Index (CDI)
  • Use a 180-day lookback period and Hierarchical Condition Categories (HCC) for risk adjustment
  • Remove health equity and health-related social needs data reporting
  • Expand use of the Skilled Nursing Facility (SNF) three-day rule waiver

HMA Analysis: The critical aspect of CMS’s TEAM provision is that the agency proposes to follow through with this Innovation Center model while cancelling other Innovation Center payment models in recent months. It also is noteworthy that the agency has proposed to remove the health equity data reporting requirements for TEAM in line with actions taken with many other CMS programs. Another proposal of note is the plan to expand the use of the waiver to circumvent the SNF three-day inpatient stay rule, which will allow hospitals to discharge patients more quickly to SNFs.

Uncompensated Care Payment Increase for Disproportionate Share Hospitals

Proposed Rule: CMS proposes to increase uncompensated care payments to DSHs by $1.5 billion in FY 2026.

HMA Analysis: CMS’s proposal will increase uncompensated care payments to hospitals by 26 percent. This increase is driven by CMS’s assumption that the rate of uninsured people will increase to 8.7 percent of the population in 2026 from 7.7 percent in 2025.

Stakeholder comments on the IPPS proposed rule are due no later than June 10, 2025.

Connect With Us

The Health Management Associates, Inc. (HMA), Medicare Practice Group monitors federal regulatory and legislative developments in the inpatient setting and assesses the impact on hospitals, life science companies, and other stakeholders. Our experts interpret and model hospital payment policies and assist clients in developing CMS comment letters and long-term strategic plans. Our team replicates CMS payment methodologies and model alternative policies using the most current Medicare fee-for-service and Medicare Advantage (100%) claims data. We also support clients with DRG reassignment requests, NTAP applications, and analyses of Innovation Center alternative payment models.

For more information about the proposed policies, please contact our expert below.

[1] U.S. Bureau of Labor Statistics. Table 1. Consumer Price Index for All Urban Consumers (CPI-U): U.S. City Average, by Expenditure Category. Modified April 10, 2025. Available at.

[2] Centers for Medicare & Medicaid Services. 2026 Medicare Advantage and Part D Rate Announcement. April 7, 2025.

Webinar Replay – Medicare Town Hall with HMA Experts

Watch Now

This webinar was held on April 30, 2025.

Whether you’re navigating Medicare Advantage policy changes, seeking actuarial insights, analyzing risk-based payment structures, or working to improve integration for Dual Eligibles and align D-SNPs, our team is here to provide actionable insights and answers. We had HMA professionals from across the country share their perspectives and help navigate the complexities of Medicare during this town hall style webinar.

Webinar Replay: PACE Development Best Practices for Policy Makers and Program Sponsors

Watch Now

This webinar was held on May 15, 2025.

Health Management Associates (HMA) conducted a multi-state study to examine the policy decisions influencing the operation and expansion of Programs of All-Inclusive Care for the Elderly (PACE). It explored different program structures, associated advantages and challenges, and strategies to enhance efficiency while meeting regulatory requirements.

This webinar summarized our research on 10 active PACE states (CA, FL, IL, KY, LA, MA, NJ, NY, OH, and WA) that have either implemented or expanded their PACE programs between 2020 and 2024. Using state survey responses and credible third-party, publicly available data, we showcased the outcomes of PACE program development through open and competitive RFP processes. We also outlined development timelines to demonstrate the effectiveness of each approach and highlight key insights gained during the discovery and research phase of the study.

Learning Objectives:

  • Comparing the Open versus Competitive RFP approach
  • Understanding state-level practices, challenges, and opportunities for improvement
  • Review state profiles highlighting: Program development outcomes; Building PACE program capacity; Program development timelines; Fostering PACE growth

Amber ground ambulance dataset reflects complexity and challenges of the industry, highlights the need to improve and continue cost data collection

Download

The Centers for Medicare & Medicaid Services (CMS) is on the cusp of possessing the data needed to make long anticipated changes to the Medicare fee-for-service (FFS) ground ambulance payment system. It has been more than two decades since CMS revised these payment rates through a negotiated rulemaking process that was exclusive of actual cost data or inflationary considerations. Since then, the cost structure of ground ambulance entities has changed. CMS is now using the Ground Ambulance Data Collection System (GADCS) to gather ambulance cost data, as required by Congress, to offer an improved understanding of the costs of delivering ground ambulance services. Given the potential of GADCS data to improve the adequacy of Medicare FFS reimbursement rates, the American Ambulance Association developed a similar data collection device, referred to as Amber, to test these data with its membership of ground ambulance entities. Amber offers a glimpse into the current challenges of the ground ambulance industry.[i]

Health Management Associates, Inc. (HMA) assessed the Amber dataset for response rates and data quality, along with responses containing calendar year 2022 financial data. Amber response rates were low, but sample volumes were on par with prior industry surveys conducted in the past by federal agencies. The Amber sample is representative of the industry’s wide variation in entity size and geographic service area. Amber data are reliable for calculating margins, but some aspects of these data also signal that ground ambulance entities, particularly smaller entities, may have had difficulty with variable definitions or the submission process. We observe that Amber would be improved by including information on uncompensated care and more details on medication supply costs.

The 2022 financial data from Amber suggest that Medicare FFS margins, at -6 percent, had declined since GAO’s 2010 assessment and that the share of costs associated with labor has increased. Amber data also suggest that the cost structure of smaller ground ambulance entities and rural and super-rural entities differs from that of larger and more urban entities. Margins for small and rural entities are lower.

Based on our assessment of the Amber dataset and its 2022 financial, we offer several recommendations to policymakers and stakeholders. These recommendations are intended to improve future cost collection efforts that may inform payment reforms to enhance the payment accuracy of the Medicare FFS payment system for ground ambulance services.

  • Provide additional educational support to respondents to improve consistency of data reporting
  • Streamline and modify data collection devices to adhere to industry trends and challenges
  • Develop a standardized method for assigning ground ambulance entities to geographic service area for research purposes
  • Collect data on ground ambulance uncompensated care and bad debt
  • Collect payer level data for cases involving treatment without transport
  • Collect targeted data on top 10 medications by cost to accurately reflect costs in payment rates
  • CMS should consider collecting ground ambulance cost data on a semi-regular basis
  • CMS should consider phasing in the use of GADCS data to ensure that the data reflect the diversity of ambulance entities and consistent reporting of key financial variables

[i] American Ambulance Association. Ambulance Cost Collection. 2023.

Medicaid Managed Care Enrollment Update: Q4 2024

Read Blog

Our second In Focus section reviews the most recent Medicaid enrollment trends in capitated risk-based managed care programs in 29 states.[1] Health Management Associates Information Services (HMAIS) collected and analyzed monthly Medicaid enrollment data from the fourth quarter (Q4) of 2024.

The data offer a timely overview of trends in Medicaid managed care enrollment and valuable insights into state-level and managed care organization (MCO)-specific enrollment patterns. This information allows state governments, their partners, and other organizations interested in Medicaid to track enrollment shifts. Understanding the underlying drivers of enrollment shifts is critical for shaping future Medicaid policies and adjusting program strategies amid a dynamic healthcare landscape.

Overview of the Data

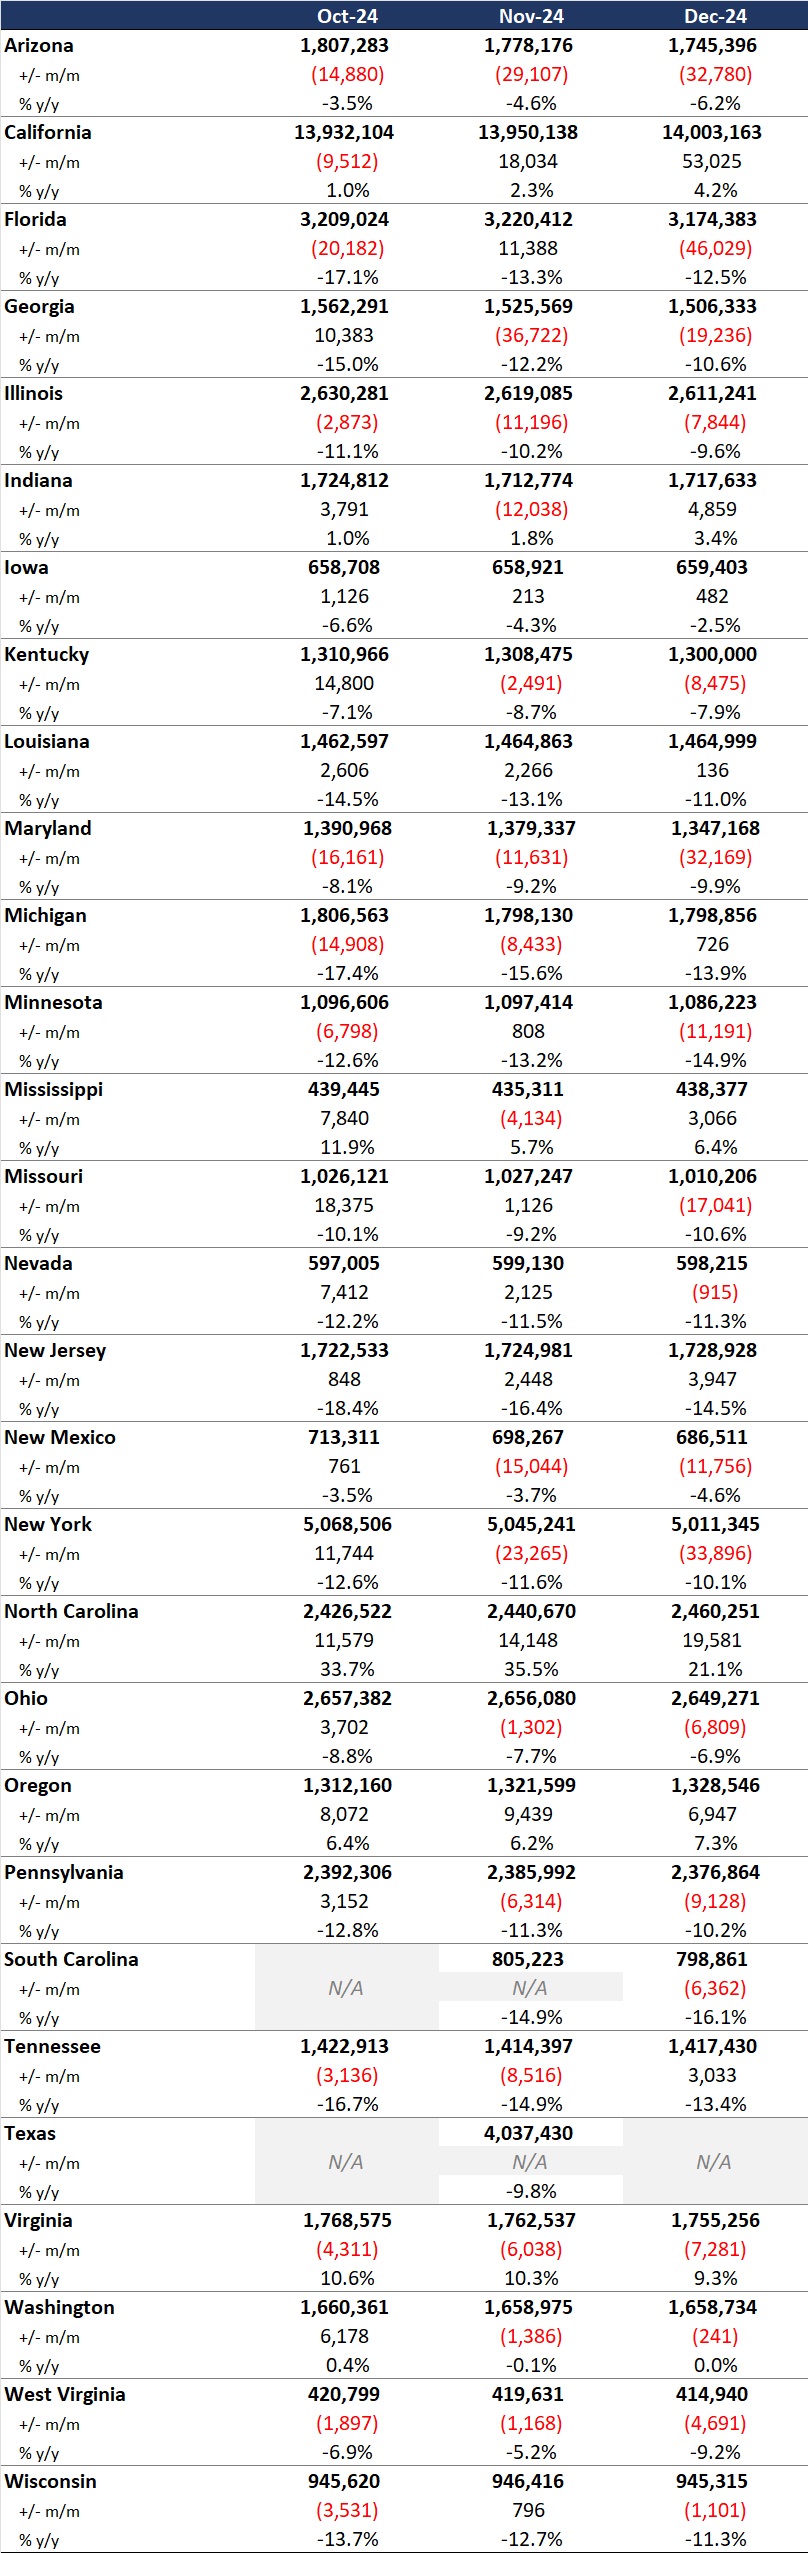
The 29 states included in our review have released monthly Medicaid managed care enrollment data via a public website or in response to a public records request from Health Management Associates (HMA). This report reflects the most recent data posted or obtained. HMA has made the following observations related to the enrollment data (see Table 1):

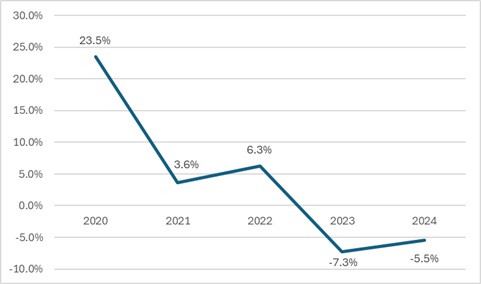
  • As of December 2024, across the 29 states tracked in this report, Medicaid managed care enrollment was 61.7 million, down by 3.6 million (-5.5%) year-over-year.
  • Though most states experienced declines in enrollment, six states saw enrollment increases as of December 2024—double the number of states from the previous year.

Figure 1. Year-Over-Year Medicaid Managed Care Enrollment Percent Change in Select States, 2020−24

  • Among the 22 expansion states included in this report, net Medicaid managed care enrollment has decreased by 2.1 million (-4%) to 49.5 million members at the end of Q4 2024, compared with the same period in 2023.[2]
  • Among the seven states included in this report that had not expanded Medicaid as of December 2024, net Medicaid managed care enrollment decreased by 1.5 million, or 1 percent, to 12.3 million members at the end of Q4 2024 compared with to the same period in 2023.

Table 1. Monthly MCO Enrollment by State—October through December 2024

Note: In Table 1 above, “+/- m/m” refers to the enrollment change from the previous month. “% y/y” refers to the percentage change in enrollment from the same month in the previous year.

It is important to note the limitations of the data presented. First, not all states report the data at the same time during the month. Some of these figures reflect beginning of the month totals, whereas others reflect an end of the month snapshot. Second, in some cases the data are comprehensive in that they cover all state-sponsored health programs that offer managed care options; in other cases, the data reflect only a subset of the broader managed Medicaid population. This limitation complicates comparison of the data described above with figures reported by publicly traded Medicaid MCOs. Hence, the data in Table 1 should be viewed as a sampling of enrollment trends across these states rather than as a comprehensive comparison, which cannot be established based solely on publicly available monthly enrollment data.

HMAIS also compiles a more detailed quarterly Medicaid managed care enrollment report representing nearly 300 health plans in 41 states. The report provides by plan enrollment plus corporate ownership, program inclusion, and for-profit vs. not-for-profit status, with breakout tabs for publicly traded plans. Table 2 shows a sampling of plans and their national market share of Medicaid managed care beneficiaries based on a total of 66.3 million enrollees. These data too should be viewed as a broader representation of enrollment trends rather than as a comprehensive comparison.

Table 2. National Medicaid Managed Care Market Share by Number of Beneficiaries for Sample of Publicly Traded Plans, 2024

What to Watch

Enrollment in Medicaid MCOs has experienced significant fluctuations recently, influenced both by policy changes and economic factors. Since April 2023, Medicaid enrollment has been on a downward trajectory as states complete eligibility redeterminations after the end of the COVID-19 public health emergency. This trend, coupled with financial and political challenges, necessitates strategic planning for stakeholders to navigate the evolving Medicaid landscape effectively.​

Potential changes that may affect enrollment and require scenario and readiness planning include:

  • Federal requirement, or a new state option, to implement Medicaid work requirements for at least some categories of enrollees
  • Changes to the federal financial match policy, which may cause some states to make different decisions about their Affordable Care Act expansion program for adults
  • Modifications in requirements and expectations for more efficient eligibility processes to improve the accuracy of determinations and assignment to eligibility categories

Connect with Us

HMA is home to experts who know the Medicaid managed care landscape at the federal and state levels. The HMAIS subscription provides point-in-time and longitudinal Medicaid enrollment data, health plan financials, and additional actionable information about eligibility expansions, demonstration and waiver initiatives, as well as population- and service-specific information. HMAIS also includes a comprehensive public documents library containing Medicaid requests for proposals and responses, model contracts, scoring sheets, and protests.

For detail about the HMAIS enrollment report and subscription service, contact our experts below.

[1] Arizona, California, Florida, Georgia, Illinois, Indiana, Iowa, Kentucky, Louisiana, Maryland, Michigan, Minnesota, Mississippi, Missouri, Nevada, New Jersey, New Mexico, New York, North Carolina, Ohio, Oregon, Pennsylvania, South Carolina, Tennessee, Texas, Virginia, Washington, West Virginia, Wisconsin.

[2] Health Management Associates, Inc. Medicaid Managed Care Enrollment Update—Q4 2023HMA Weekly Roundup. April 17, 2024.

Ready to talk?