HMA Insights: Your source for healthcare news, ideas and analysis.
HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.
In this webinar, attendees learned the essential methods and practices to enhance Star ratings through the HMA Stars Accelerator program. The session explored how to leverage data analytics to effectively track current star performance and identify areas for improvement. Additionally, it covered stratification techniques that allow for targeted focus on key measure opportunities throughout the year to ensure optimal results.
Learning objectives:
Learn how to implement proven strategies and best practices
Understand how to leverage data analytics to monitor and assess trends
Provide focus areas to measure opportunities and enhance performance
This week’s In Focus highlights a white paper that Wakely, a Health Management Associates, Inc. (HMA), company published in September 2024, titled “A Cut Above the Rest: Summary of 2025 Star Rating Cut Point Changes.” The paper provides an in-depth analysis of the latest cut point changes from the Centers for Medicare & Medicaid Services (CMS) to demonstrate how policies like the Tukey Outer Fence Outlier removal logic (Tukey), guardrails, and changes in overall quality performance have led to the highest Medicare Advantage (MA) Star Rating cut points in the program’s history.
Why Cut Points Matter
MA Star Ratings are a critical measure of the quality and performance of MA plans. The MA Star Ratings cut points are the thresholds CMS has set to evaluate the performance of MA plans. These ratings, ranging from 1 to 5 stars, are based on various quality measures, including clinical outcomes, patient experience, and plan administration. CMS applies methodologies such as Tukey to set the cut points and guardrails to stabilize them over time. MA plans are evaluated and earn a rating that is based on their performance against the cut points. Higher Star Ratings can lead to increased enrollment and higher payments from CMS, making them a key focus for MA organizations.
Key Findings
Wakely used the 2025 Star Rating Technical Notes to analyze measure-level cut point changes. The data summarize how Medicare Advantage organizations (MAOs) performed on various quality measures during the 2023 measurement year. Notably, the Tukey methodology was applied for the first time within the 2024 Star Ratings cut points. Initially, the full impact of this methodology was evident in the initial 2024 Star Ratings, but the updated 2024 Star Ratings restricted use of guardrails and spread the impact of Tukey over a few years.
The analysis reinforces expectations for changes in MA spending in 2026, in part because of changes in Medicare Advantage Prescription Drug Overall Star Ratings.
The Star Ratings have been on a steady decline over the last two years while CMS continues to refine and evolve its Star Ratings methodology and areas of focus. Key issues to consider in this climate include:
MAOs are experiencing significant reductions in quality bonus and rebate payments, which potentially affects opportunities to improve member health outcomes.
Strategies to enhance Star Ratings and elevate program quality are crucial for performance and meeting the unique needs of MA enrollees.
MA plans and other stakeholders also should consider that as plans optimize performance on certain traditional quality measures, CMS is placing increased emphasis on member experience with their health plan and providers during care.
The Star Ratings is an important tool CMS uses to redirect plan focus and resources.
CMS is scheduled to release the final scores and Star Ratings for Star Year 2025 in early October 2024. These ratings will be based on the performance data from the 2023 dates of service. This release will provide MAOs with updated quality and performance metrics, which are used to determine CMS Star Ratings and subsequent quality-based payments.
Connect with Us
For further insights into the Star Ratings and more information on the report, contact our featured experts below.
Strategies and actions MAOs implement in 2024 and 2025 will affect their 2026 Star Ratings. For further insights into programmatic strategies, best practices for design of meaningful solutions to implement, and approaches to measure the effectiveness of these solutions, explore The HMA Stars Accelerator Solution.
This week, our In Focus section from the HMA Weekly Roundup highlights the Illinois Department of Healthcare and Family Services request for proposals (RFP) for a dual-eligible special needs plan (D-SNP) to replace its current Medicare-Medicaid Alignment Initiative (MMAI) demonstration.
Overview
Illinois is one of the states affected by the Centers for Medicare & Medicaid Services (CMS) decision to end the capitated model in the federal Financial Alignment Initiative (FAI) demonstration. Illinois is among the last states to issue an RFP that will support the transition from the demonstration program. Two states, Texas and South Carolina, have yet to issue RFPs. On September 10, 2024, CMS issued a memo discussing end-of-demonstration enrollment and operational considerations and deadlines by which states should make operational decisions.
The Health Management Associates, Inc., (HMA) In Focus article June 26, 2024, discussed related changes that CMS finalized to the federal policy framework for D-SNPs to enhance care coordination, improve health outcomes, and ensure that dual-eligible beneficiaries receive accurate information about their healthcare while integrating successful features of the FAI demonstration and the Medicare-Medicaid Plan (MMP) program. These decisions are prompting more states to develop new models for integrating Medicare and Medicaid services.
Illinois D-SNP RFP Highlights
This Illinois procurement will transition the state to a fully integrated dual-eligible special needs plan (FIDE-SNP) model, which will include a requirement that plans provide managed long-term services and supports (MLTSS) for both people who are dually eligible and Medicaid-only beneficiaries beginning in 2027.
The RFP is largely focused on quality care provisions and improved care coordination across all services lines, including overall expectations to achieve the following:
Improved access and quality of community-based behavioral health services
Better quality of care in facilities
Fewer program opt-outs
A strategy for increasing the use of alternative payment models (APMs) in Medicaid managed care in Illinois, particularly for behavioral health providers
Emerging National Trends
Overall, the Illinois D-SNP procurement reflects broader national trends toward more coordinated, equitable, and outcome-focused healthcare.
Focus on Health Equity. The procurement emphasizes health equity and reducing disparities, including information on innovations that are responsive to health-related social needs (HRSNs) and social determinants of health (SDOH). The state is weighing payers’ experience partnering with non-traditional providers to meet Medicaid customers’ needs, their innovative programs to address customers who are difficult to locate, and their strategies for improving care for adults with complex needs in facility or community-based settings.
In addition, the state will require plans to report outcomes by race, ethnicity, and geography. Given the demographic and health equity reporting requirements, payers should be prepared to speak to their data collection, member engagement strategies, and relationships with community-based organizations. This capability will be an essential component of addressing both population health and health equity activities.
Alternative Payment Models. The RFP also requests detailed information on the payer’s strategy for increasing the use of APMs in Illinois Medicaid managed care, including the models the payer intends to implement. Experience supported by data-driven outcomes and explanations of work with providers or clinics to adopt, manage, and support reporting and analytics for APMs is a key area of interest for the state. Notably, the state seeks information on plans to include behavioral health providers in APMs.
Long-Term Services Related Transitions. The RFP questions also reflect the long-term services and supports that dually eligible beneficiaries need, as well as those of Medicaid-only beneficiaries who are eligible for these services. More specifically, the RFP raises questions to determine how payers will effectively implement nursing home diversion plans, incentivize hospitals to discharge patients to community settings, and approaches to transition members from institutional settings to the home and community, including by connecting members with supports for HRSNs. Payers will be expected to provide specific examples of their experience and outcomes in other states.
Emerging National Trends
The emphasis on health equity in the Illinois RFP reflects a broader national trend. States are increasingly interested in—and in some situations required—addressing SDOH and reduce disparities, especially for the Medicare and Medicaid dual-eligible population. As a result, payers and other healthcare organizations must develop capacity internally and through external collaborations to build their expertise and evidence base for advancing improvements.
The push for APMs in the Illinois procurement aligns with national efforts to move away from fee-for-service models. Illinois’s inclusion of behavioral health providers in APMs and requiring integrated care models highlights the growing recognition of the importance of mental health in overall health outcomes.
Illinois’s RFP also reflects heightened interest in improving care transitions and coordination. The potential for incentive programs related to community placement and increased focus on nursing home diversion will require innovative plans and a long-term commitment to working with all stakeholders to build on the federal FAI experiences.
What We’re Watching
Responses to the Illinois RFP are due October 18, 2024, and awards are expected to be announced in December. The state anticipates making awards to the top four bidders. Contract execution is estimated July 2025, with implementation January 1, 2026.
As the FAI demonstration ends and CMS’s integration requirements take effect over the next several years, there will be a steep learning curve for states, payers, and other key stakeholders adapting to this evolving environment. Compliance with new CMS rules will be crucial, and experiences in Illinois and other FAI demonstration states can provide valuable insights for other states and stakeholders.
Additional growth and program refinements in the federal Medicare Advantage (MA) landscape are expected in the coming years, especially among MA D-SNPs. Those MA D-SNPs that have yet to participate in Medicaid will need to continue make significant business decisions on participation and actively compete to secure state Medicaid contracts, which will have downstream implications for their state and local partners.
Connect with Us
Health Management Associates (HMA) experts continue to review the evolving landscape and federal changes that will affect D-SNPs in 2025 and beyond. Contact our featured experts below for details about the nationwide D-SNP rules and landscape.
The upcoming HMA event, Unlocking Solutions in Medicaid, Medicare, and Marketplace, offers extensive opportunities to engage with leaders from various sectors who are designing and implementing Medicare-Medicaid integration initiatives. Join us for main stage panel discussions with distinguished health plan executives from national and local plans and Medicaid directors from Iowa, New Mexico, New York, and Rhode Island.
HMA Principal Holly Michaels Fisher will lead a deeper dive into integration issues during the breakout session, Innovations to Improve Outcomes for Medicare-Medicaid Dually Eligible Individuals, with speakers Michael Carson, President and CEO of WellCare; Dr. Steven R. Counsell, Medical Director for the Division of Aging at Indiana Family and Social Services Administration; Dr. Linda Kurian, Executive Medical Director for the Center of Excellence of Medicare Duals/D-SNP at Aetna; and Juliet Marsala, Deputy Secretary for the Office of Long-term Living in the Pennsylvania Department of Human Services.
During the breakout, Meeting New Expectations for Health Equity and Improved Beneficiary Outcomes in Medicare Advantage, HMA Principal Greg Gierer will facilitate a conversation on the evolving landscape of MA rates and supplemental benefits, with experts Melinda Buntin, Health Economist and Bloomberg Distinguished Professor at the Johns Hopkins Bloomberg School of Public Health and the Johns Hopkins Carey Business School; Mark Fendrick, Director of the University of Michigan’s Center for Value-Based Insurance Design, and Matt Kazan, Vice President of Policy and Government Affairs at the SCAN Group.
This week’s second In Focus continues the conversation on drug policies and trends, providing updates and insights into the current landscape of Medicare’s drug price negotiations.
The Centers for Medicare & Medicaid Services (CMS) recently released the negotiated prices for the first 10 Medicare Part D drugs under the Inflation Reduction Act’s (IRA’s) negotiation authority. CMS plans to add more drugs to the negotiation list, including 15 additional Part D drugs in 2027 and 15 more products from both Part D (pharmacy benefit drugs) and Part B (mostly physician administered drugs). In 2029 and later years, another 20 drugs from either Part B or Part D will be chosen.
Negotiated Prices for First 10 Drugs Leave Unanswered Questions
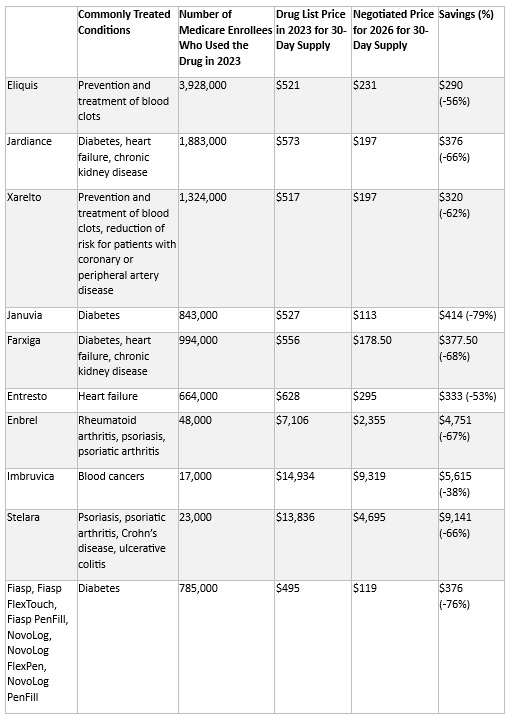
CMS estimates the negotiated prices for 30-day supplies of each medication will result in savings ranging from 38 percent to 79 percent compared with list prices when they take effect in 2026. This comparison, however, does not account for several factors that could affect the actual savings for the Medicare program and beneficiaries, including:
Current negotiated discounts available to Medicare Part D plans
Changes in tier placement for the negotiated drugs and their impact on patient cost sharing
The exemption for manufacturers from the 10 percent discount during the initial coverage phase and the 20 percent discount thereafter once negotiated prices take effect in 2026
The effect of Medicare’s negotiations on prices paid by other payers
The impact of the IRA program on prices for other products and manufacturer investments in research and development of new products
CMS is required to provide a detailed explanation of how negotiated prices were determined by March 1. The price comparisons with privately negotiated prices, however, will remain unclear and the effects on other payers and longer-term investments in new products may not be fully understood for some time. The table below lists the negotiated discounts for the first 10 drugs, which CMS selected from the top 50 Part D drugs by spending, which lacked generic or biosimilar alternatives and met other IRA criteria.
Age of Products and Role of Generic and Biosimilar Competition: Drugs eligible for negotiation are typically the highest expenditure drugs that have been on the market for at least seven years or 11 years in the case of biologics. Importantly, products with generic or biosimilar competition are exempt from negotiation. This exemption may increase the speed at which biosimilar or generic competition comes to market, as the IRA requires competitors to engage in bona fide marketing to exempt an innovator from negotiation. Despite approval, biosimilars for some of the drugs will remain subject to negotiated prices until their marketing efforts begin.1
Impact on Medicaid and Other Payers: The IRA’s negotiated discounts are not required to be available outside of the Medicare program. It remains uncertain whether other payers will use Medicare-negotiated prices as leverage in their own negotiations. For Medicaid, the direct impact of negotiations themselves is expected to be negligible; however, the IRA’s inflation penalties could encourage more manufacturers to moderate price increases over time, potentially leading to reduced inflation penalty rebates to state Medicaid programs.
Connect with Us
To explore these topics further, join Health Management Associates at the upcoming event, Unlocking Solutions in Medicaid, Medicare, and Marketplace. Engage with our Medicare experts below who will lead a small group discussion on trends in prescription drug policies during the pre-conference workshop.
For details on IRA pricing issues or other Medicare health policy developments, contact our featured experts below. HMA’s Wakely Actuaries also are available to discuss the IRA’s role in Medicare Part D.
The Medicare Advantage (MA) market has had an eventful year, and the chaos is expected to continue. As plans begin their preparation for the upcoming 2026 Plan Year, what are the emerging trends in benefits, STARS, revenue optimization and the regulatory environment? Are you a Medicare Advantage health plan leader overwhelmed with all the changes in the industry? Check out this webinar for some helpful information.
Learning Objectives:
Review recent high-level challenges in the MA market.
Gain an understanding of several “hot topics” that MA plans should be thinking about as they begin planning for 2026.
Learn from HMA experts on recommended actions for each of these topics
Given that 50 percent of Americans have publicly funded health insurance—including Medicare, Medicaid, or Affordable Care Act Marketplace plans in which many premiums are subsidized—the need is growing for innovations that will yield better quality at lower total cost. The Health Management Associates (HMA) Fall Conference, Unlocking Solutions in Medicaid, Medicare, and Marketplace, offers an agenda that dives deeply into the latest innovations and opportunities in these critical programs. Focused on improving collaboration and information sharing, the event will explore strategies and practical solutions to reduce health disparities and enhance outcomes for aging, disabled, and chronically ill people.
The federal government recently created the Advanced Research Projects Agency for Health (ARPA-Health), which is charged with supporting the development of high-impact solutions to improve health outcomes. We are fortunate to have as our keynote speaker Dr. Darshak Sanghavi from ARPA-H. We have asked him to share his thoughts on why innovation in the public healthcare space is critical.
Dr. Sanghavi will kick off the HMA conference with a discussion on how ARPA-H initiatives are intended to support new solutions to modernize today’s healthcare landscape—not only with technology, but also through changes in our approaches to healthcare delivery and payment.
Only a month before the November elections, the HMA conference presents a valuable opportunity to engage with healthcare leaders across the public and private sectors to hear how they are thinking about potential policy and regulatory changes that could affect publicly funded programs and supplemental coverage. Attendees will take home insights and actionable ideas to drive improvements in health and well-being. Join us to shape the solutions that will impact the future of healthcare!
This week, our In Focus section reviews the policy changes that the Centers for Medicare & Medicaid Services (CMS) finalized on August 1, 2024, in the fiscal year (FY) 2025 Medicare Hospital Inpatient Prospective Payment System (IPPS) and Long-Term Acute Care Hospital (LTCH) Final Rule (CMS-1808-F). This year’s IPPS final rule will impact hospital margins and administrative processes beginning October 1, 2024.
The remainder of our article delves into five of the key policy changes included in the final rule.
Key provisions in the FY 2025 Hospital IPPS and LTCH Final Rule
For FY 2025, CMS will modify several hospital inpatient payment policies. We highlight five of these policies because they will have the most significant impact on Medicare beneficiaries, hospitals and health systems, payors, and manufacturers:
The annual inpatient market basket update and changes to the standardized payment amount
New technology add-on payment (NTAP) policy changes
Implementation of the Transforming Episode Accountability Model (TEAM) bundled payment model in 2026
Hospital wage index changes and labor market adjustments
Severity of illness increase for housing insecurity social determinants of health (SDOH) codes
Several of these and other policy changes for FY 2025 will become effective October 1, 2024.
Marketbasket update
Final rule: Overall CMS’s Medicare 2025 Hospital IPPS Rule will increase hospital inpatient payments to acute care hospitals by 2.9 percent from 2024 to 2025, an estimated increase of approximately $2.9 billion after other policy changes are included.
Health Management Associates (HMA) analysis: CMS’s 2.9 percent increase is largely based on an estimate of the rate of increase in the cost of a standard basket of hospital goods—the hospital market basket. For beneficiaries, this payment rate increase will lead to a higher standard Medicare inpatient deductible and increase out-of-pocket costs. The finalized payment increase (2.9 percent) is larger than the increase included in CMS’s IPPS Proposed Rule (2.6 percent) but continues to fall below economy-wide inflation over the past year (3.5 percent).1,2 Importantly, after accounting for the various policy changes made within the final rule (e.g., wage index reclassifications) we anticipate individual cases will experience an average payment increase of 1.7 percent.
Transforming Episode Accountability Model
Final rule: CMS finalized the creation of a new mandatory episode-based CMS Innovation Center methodology—TEAM. Under TEAM, selected acute care hospitals will coordinate care for people with traditional Medicare who undergo one of the following surgical procedures:
Lower extremity joint replacement
Surgical hip femur fracture treatment
Spinal fusion
Coronary artery bypass graft
Major bowel procedure
Hospitals in the model will assume responsibility for the cost and quality of surgical care through the first 30 days after a Medicare beneficiary leaves the hospital. Hospitals also must refer patients to primary care services to support optimal long-term health outcomes. Hospitals will be assigned to different risk tracks to allow a graduated path to ease in to full-risk participation.
HMA analysis: The mandatory nature of this model requires hospitals in the selected geographic areas to begin to prepare for implementation of the model requirements in 2026. TEAM builds on and combines previous models such as the bundled payment for care improvement (BPCI) and the comprehensive care for joint replacement (CJR) models. Hospitals in roughly 23 percent (188 of 925) of the nation’s core-based statistical areas (CBSAs) are required to participate in this advanced payment model, with some exceptions, such as hospitals in Maryland and Sole Community Hospitals. Participating hospitals will be required to report various quality measures, and payment will be based on spending targets and include retroactive reconciliation. Reimbursement under the model will follow four different tracks, which vary by the level of upside and downside risk that the hospital accepts and with a specific track for safety net hospitals.
Hospital Wage Index Adjustments and Labor Market Changes
Final rule: CMS finalized two wage index policies for FY 2025. First, CMS extended the temporary policy finalized in the FY 2020 IPPS/LTCH PPS final rule for three additional years to address wage index disparities affecting low wage index hospitals, which includes many rural hospitals. Second, as required by law, CMS revised the labor market areas used for the wage index based on the most recent CBSA delineations issued by the OMB based on 2020 Census data.
HMA analysis:The two wage index policy changes for FY 2025 will have important positive and potentially negative consequences on hospital payment. The policy to extend the low wage index policy for three more years will allow many hospitals with low wage indexes to increase their wage index and their payment rates across all Medicare severity diagnosis-related groups (MS-DRGs).
Specifically, the roughly 800 hospitals with wage indexes below 0.9007 (the 25th percentile across all hospitals) will automatically receive an increase in their wage index and payment rates for all inpatient cases. This policy will bring additional millions of dollars to individual rural hospitals in FY 2025. The second policy is a statutorily required update to the labor markets used to establish CMS’s hospital wage indexes. To implement this policy, CMS will use US Census Bureau data to redefine urban and rural markets. As a result, CMS will redefine 53 urban counties as rural and will newly redefine 42 rural counties containing a hospital as urban. These changes will disrupt various hospital payment policies for hospitals in these counties. The overall impact of both geographic policy changes for FY 2025 will be to increase inpatient payment rates to rural hospitals.
Revision to Social Determinants of Health Housing Insecurity Diagnosis Coding
Final rule: CMS finalized a change in the severity designation of the seven ICD-10-CM diagnosis codes that describe inadequate housing and housing instability. Under the final rule, these codes are changing from non-complication or comorbidity (non-CC) to complication or comorbidity (CC) based on the higher average resource costs of cases compared with similar cases without these codes.
HMA analysis:This new policy will enable hospitals to receive higher inpatient payment rates when they provide care for patients with inadequate housing or housing instability are served. Specifically, this policy change will result in assigning cases involving patients with one of these codes to a higher-level MS-DRG. Hospital staff will want to ask patients about their housing upon admission and discharge to accurately document this critical SDOH characteristic.
New technology add-on payments
Final rule: CMS finalized three changes to the NTAP program and approved several products for NTAPs in FY 2025.
HMA analysis: CMS seems willing to increase NTAP payments in certain limited situations to boost selected policy goals but rejects comments seeking to increase the percentage for sickle cell products or expand the higher payments to other medical conditions. In addition, portions of the final rule indicate that CMS is applying some of the criteria for NTAPs more strictly than in recent years. If this trend continues, it may be more difficult for future new technologies to be approved for NTAPs.
Connect with Us
HMA’s Medicare Practice Group works to monitor legislative and regulatory developments in the inpatient hospital space and assess the impact of inpatient payment, quality, and policy changes on the hospital sector. We will continue to follow these and other changes happening to hospitals and are available to provide additional detail on these or other policies in the final rule. If you have any questions, please contact our featured experts below.
While legal experts assess the recent U.S. Supreme Court rulings, federal and state agency leaders face significant questions about how their agencies and their responsibilities will be impacted. This webinar featured insightful discussions with former federal and state agency leaders exploring the known and yet-to-be determined impacts of recent rulings on federal regulations, rulemaking and actions, and agency deference, and also explored the impact on state agencies implementing federal rules. The webinar addressed the impact of the pivotal Loper Bright Enterprises v. Raimondo and West Virginia v. EPA decisions. Together these decisions overturned the longstanding Chevron deference doctrine, are pushing Congress to craft more specific legislation, and are directing courts to interpret ambiguous statutes. The discussion also explored the most appropriate responses of agency leaders, anticipated the ways that these decisions impact federal and state agency decision-making, and identified areas of growing uncertainty.
Learning Objectives:
Understand what we know about the impact of these decisions on agency rulemaking and decision making, consider the impact on federal agency discretion, and understand the shift in power towards Congress and judicial interpretation
Analyze the likely impact on agency rulemaking processes
Explore state governance issues, both as a partner to federal agencies and as an implementer of federal policy and funds
Identify the most important questions yet to be answered
This week, Health Management Associates (HMA) shifts In Focus from a newsworthy development to commemorate a seminal event in the expansion and strengthening of healthcare access in the United States. On July 30, 1965, Medicaid and Medicare were signed into law under Title XVIII and Title XIX of the Social Security Act. Today we celebrate the 59th anniversary of this pivotal moment in America’s healthcare journey.
Medicaid: A Critical Safety Net that Remains Strong
All states, the District of Columbia, and the U.S. territories have Medicaid programs designed to provide health insurance coverage for low-income individuals. As of March 20241, 82,751,338 people, including eligible low-income adults, children, pregnant women, older adults, and people with disabilities are covered under their state’s Medicaid program in accordance with federal requirements. The COVID-19 pandemic underscored just how important this safety net program is for American families, as it continued to deliver vital services during unprecedented times.
Beyond its traditional role, Medicaid also drives significant innovations in care for people with complex conditions and challenges. States have implemented various programs and initiatives to improve healthcare quality and outcomes. These include:
Managed Care Expansion: Many states have expanded Medicaid managed care programs to enhance care coordination and improve health outcomes.
Value-Based Care Models: Innovations in value-based care are being tested, aiming to link reimbursement to quality of care and patient outcomes rather than volume of services.
Integration of Behavioral Health: Several states are integrating behavioral health services into Medicaid to address mental health and substance use disorders more effectively.
Telehealth: The pandemic accelerated the adoption of telehealth services in Medicaid, expanding access to care and reducing barriers for patients.
Medicare: Leading in Innovation and Coverage
Medicare provides coverage to more than 60 million seniors and people with disabilities. In addition to being a lifeline for so many Americans, Medicare is a force for innovation in health policy, piloting changes to payment and care delivery through the Innovation Center and through Medicare Advantage plan design. Key innovations include:
Alternative Payment Models: The Innovation Center has been at the center of piloting various alternative payment models to improve quality and reduce costs.
Medicare Advantage Enhancements: Medicare Advantage plans continue to evolve, offering more comprehensive benefits that include mental health and substance use disorder services and integrating additional services such as dental, vision, and wellness programs.
Chronic Care Management: Medicare is expanding its focus on chronic care management, providing additional resources and support for individuals with chronic conditions.
HMA’s Commitment to Medicaid and Medicare
Since HMA’s founding, our experts have helped states, plans, providers, and other stakeholders deliver the full spectrum of Medicaid and Children’s Health Insurance Program (CHIP) services. As HMA has evolved, we have built a leading-edge Medicare team that includes former agency officials, plan leaders, policy and data analysts, and actuaries. Healthcare plans, providers, and innovators call upon our colleagues to anticipate policy and regulatory change, develop and support Medicare Advantage business, transform fee-for-service programs, and support access to new technologies and treatments that can both improve quality patient outcomes and reduce costs of care.
Our growing team of includes 10 former state Medicaid directors and many more former state agency leaders, hospital and health plan executives, senior officials from the Centers for Medicare & Medicaid Services (CMS), and public health leaders.
HMA Colleagues Who Are Former Medicaid Directors Looking Ahead
As Medicaid and Medicare near their seventh decade, the programs will continue to evolve and change to better support covered individuals and meet the demands of policymakers and taxpayers. HMA experts are committed in service of this important mission, and we are excited about building their future together with our clients to create more innovative, high-quality care that improves health outcomes for all.
This week, our In Focus section reviews the notice of funding opportunity (NOFO) for the Transforming Maternal Health (TMaH) Model, which the Centers for Medicare & Medicaid Services (CMS) Center for Medicaid and Medicare Innovation (the Innovation Center) announced on December 15, 2023. States interested in participating in this model must submit an application to CMS during the competitive application process.
As described in a December 2023 In Focus, pregnancy-related deaths have more than doubled since 1987 to 17.6 deaths per 100,000 live births, with health disparities only worsening outcomes for different racial and ethnic groups. For example, the pregnancy-related mortality rates for Black and Native American and Alaska Native people are approximately two to three times higher than the rate for White people. In recent years, 38 states have extended postpartum coverage, and 11 states now offer doula coverage for Medicaid enrollees. This initiative accelerates the focus on maternal outcomes and, with Medicaid paying for nearly 43 percent of births, has the potential to affect health across generations.
This model is designed exclusively to improve maternal healthcare for people enrolled in Medicaid and the Children’s Health Insurance Program (CHIP). The TMaH model takes a whole-person approach to pregnancy, childbirth, and postpartum care, addressing the physical, mental health, and social needs people experience during pregnancy.
Model Overview
Up to 15 participating state Medicaid agencies (SMAs) will receive as much as $17 million over the 10-year period to develop a value-based alternative payment model for maternity care services, with the intention of improving quality and health outcomes and promoting the long-term sustainability of services. TMaH will focus on three pillars:
Access to care, infrastructure, and workforce capacity
Quality improvement and safety
Whole-person care delivery
The TMaH model is designed to support birthing persons along their care journey, expanding continuity, and improving outcomes.
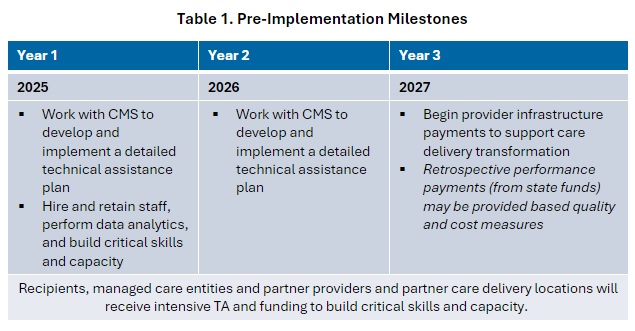
During the model’s first three years, states will receive targeted technical assistance to achieve pre-implementation milestones. The table below highlights the key activities in the pre-implementation phase.
Following pre-implementation, participants will enter a seven-year implementation period during which the SMAs will implement the program with partners, such as managed care organizations (MCOs), perinatal quality collaboratives, hospitals, birth centers, health centers and rural health clinics, maternity care providers, and community-based organizations.
In year four, states will offer partnering providers and care delivery sites upside-only performance payments from state funds (no cooperative funds may be used). In year five, states will transition partner provider and partner care delivery locations to a new value-based payment model. CMS will lead the development of the value-based model, and it will be finalized during the pre-implementation period.
The model also requires a health equity plan, which has been a consistent requirement across models from the Innovation Center. Awardees must develop a plan that addresses disparities among underserved populations, such as racial and ethnic groups and people living in rural areas, who are at higher risk for poor maternal outcomes.
State Medicaid Agency Requirements
For states considering TMaH, the NOFO outlines the requirements for participating SMAs, which include:
States must include CHIP if pregnant people receive services through CHIP
States that have managed care plans must contract with at least MCO for implementation
Collaborate with partner providers (e.g., OBs, midwives, doulas), care delivery location (e.g., hospitals, birth centers, federally qualified health centers), and partner organizations
Collaborate in the process to create cost and quality benchmarks with CMS
Be actively involved in technical assistance activities, including attending regularly scheduled calls, providing input and working on portions of documents as appropriate
Execute the data-sharing agreements necessary to support the exchange of data and information related to the TA activities and completion of milestones
Provide CMS and contractors the necessary information and data to support the development of documents to help reach milestones
States must demonstrate their ability to meet these requirements as part of the NOFO process, and CMS will evaluate their responses as part of the selection process
TMaH Opportunities and Considerations
The model offers states resources and technical assistance to develop value-based alternative payment models to support whole-person pregnancy, birth, and postpartum care and improved outcomes. Many SMAs already are working on programs to innovate care and payment, and the TMaH is an opportunity to expand and accelerate those programs.
The model offers an opportunity for states that have yet to expand postpartum coverage or added doula benefits to adopt these policies with the funding and technical assistance they may need to support their efforts.
SMAs interested in this opportunity should evaluate their application readiness and pre-plan for the application.
What’s Next?
States interested in TMaH should submit a letter of intent by August 8, 2024. Applications are due by September 20, 2024, and the model is expected to start January 2025.
The Health Management Associates team will continue to evaluate the TMaH model as more information becomes available. For more information, contact our featured experts below.
This report quantifies the economic impact of opioid use disorder (OUD) specific to the Medicare fee-for-service (FFS) program, which covers approximately 51.6 percent of Medicare beneficiaries. We find that the cost to Medicare for managing these newly diagnosed patients was $29,669 more per patient than the propensity-matched control patients without OUD in 2022. We thus estimate that newly diagnosed OUD patients cost the Medicare program $4.3 billion in 2022. If these incident patient results were extrapolated into a 10-year budgetary impact analysis and if we assume constant rates of OUD incidence in the Medicare population, we estimate that the 10-year impact of OUD to the Medicare program would be $62.56 billion.
Our analysis demonstrates that OUD results in significant Medicare spending, including rising costs to beneficiaries through copayments and increased premiums. Additional work may be needed to determine whether the cost differential for incident patients with OUD generalizes to prevalent OUD patients as well. Though the 10-year budgetary impact figures require extrapolation and assumptions about future OUD use, they illustrate for policymakers the size of the fiscal challenge created by OUD in the Medicare population.