Managed Care

Medicaid managed care spending tops $420 billion in 2021

This week, our In Focus section reviews preliminary 2021 Medicaid spending data collected in the annual CMS-64 Medicaid expenditure report. After submitting a Freedom of Information Act request to the Centers for Medicare & Medicaid Services (CMS), HMA received a draft version of the CMS-64 report that is based on preliminary estimates of Medicaid spending by state for federal fiscal year (FFY) 2021. Based on the preliminary estimates, Medicaid expenditures on medical services across all 50 states and six territories in FFY 2021 was nearly $710.2 billion, with over 59 percent of the total now flowing through Medicaid managed care programs. In addition, total Medicaid spending on administrative services was $30.8 billion, bringing total program expenditures to $741 billion.

Total Medicaid Managed Care Spending

Total Medicaid managed care spending (including the federal and state share) in FFY 2021 across all 50 states and six territories was $420.5 billion, up from $359.6 billion in FFY 2020. This figure includes spending on comprehensive risk-based managed care programs as well as prepaid inpatient health plans (PIHPs) and prepaid ambulatory health plans (PAHPs). PIHPs and PAHPs refer to prepaid health plans that provide only certain services, such as dental services or behavioral health care. Fee-based programs such as primary care case management (PCCM) models are not counted in this total. Below we highlight some key observations:

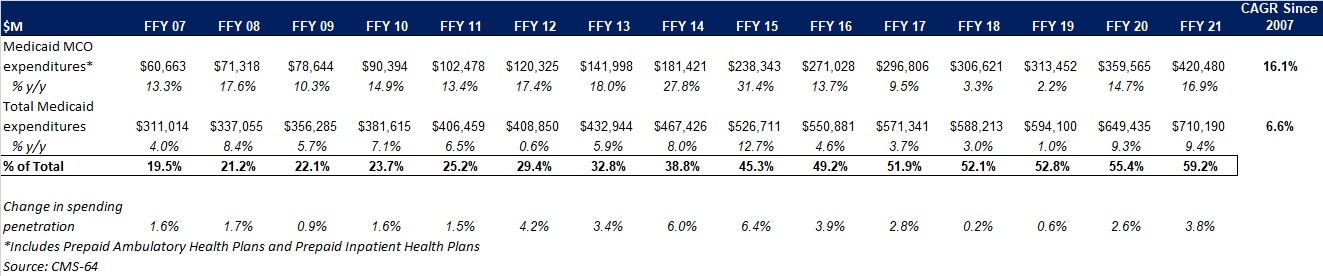
  • Total Medicaid managed care spending grew 16.9 percent in FFY 2021. The rate of growth has been increasing since the COVID-19 pandemic. Prior to 2020, the rate had decelerated since FFY 2016.
  • Managed care spending growth was due in large part to the COVID-19 pandemic and the resulting higher Medicaid enrollment.
  • In terms of dollars, the increase in Medicaid managed care spending from FFY 2020 to FFY 2021 was $60.9 billion, compared to $46.1 billion from FFY 2019 to FFY 2020.
  • Medicaid managed care spending has increased at a compounded annual growth rate (CAGR) of 16.1 percent since FFY 2007, compared to a 6.6 percent growth in total Medicaid spending.
  • Compared to FFY 2020, Medicaid managed care spending as a percent of total Medicaid spending in FFY 2021 increased by 3.8 percentage points to 59.2 percent.

Figure 1: Medicaid MCO Expenditures as a Percentage of Total Medicaid Expenditures FFY 2007-2021 ($M)
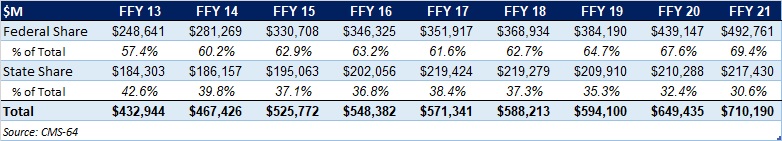
As the table below indicates, 69.4 percent of FFY 2021 spending came from federal sources, which is 12 percentage points higher than the pre-Medicaid expansion share in FFY 2013, and 1.8 percentage points higher than FFY 2020.

Figure 2: Federal vs. States Share of Medicaid Expenditures, FFY 2013-2021 ($M)
State-specific Growth Trends

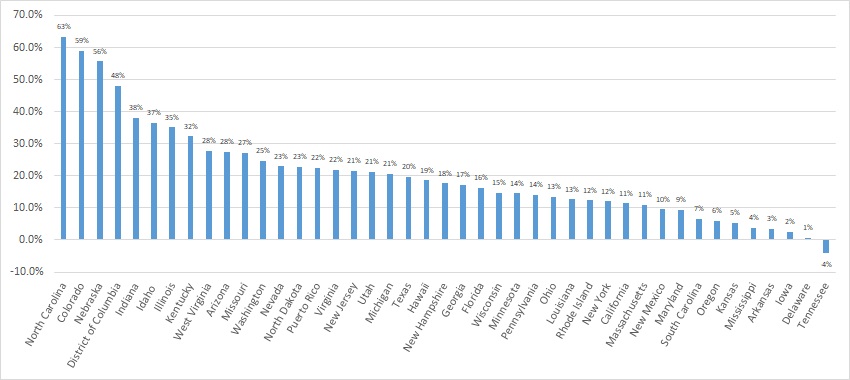
Forty-five states and territories report managed care organization (MCO) spending on the CMS-64 report, including Alaska, which utilizes a PIHP/PAHP model exclusively. Oklahoma is expected to implement a Medicaid managed care program in 2023. Of the remaining 44 states and territories that contract with risk-based MCOs, average MCO spending in FFY 2021 increased 17.6 percent. On a percentage basis, North Carolina experienced the highest year-over-year growth in Medicaid managed care spending at 63.3 percent due to the implementation of its risk-based Medicaid managed care program. Among states with more mature programs, Colorado experienced the fastest growth in FFY 2021 at 59 percent, followed by Nebraska at 55.6 percent.

The chart below provides additional detail on Medicaid managed care spending growth in states with risk-based managed care programs in FFY 2021.

Figure 3: Medicaid Managed Care Spending Growth on a Percentage Basis by State FFY 2020-21
Source: CMS-64; *Note: Not all states are included in the table.

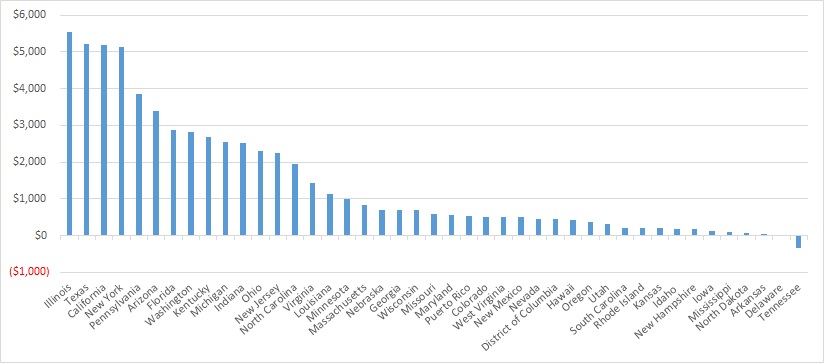
Looking at year-over-year spending growth in dollar terms, Illinois experienced the largest increase in Medicaid managed care spending at $5.5 billion. Other states with significant year-over-year spending increases in dollar terms included Texas ($5.2 billion), California ($5.2 billion), and New York ($5.1 billion). The chart below illustrates the year over year change in spending across the states.

Figure 4: Medicaid Managed Care Spending Growth on a Dollar Basis by State FFY 2020-21 ($M)
Source: CMS-64; *Note: Not all states are included in the table.

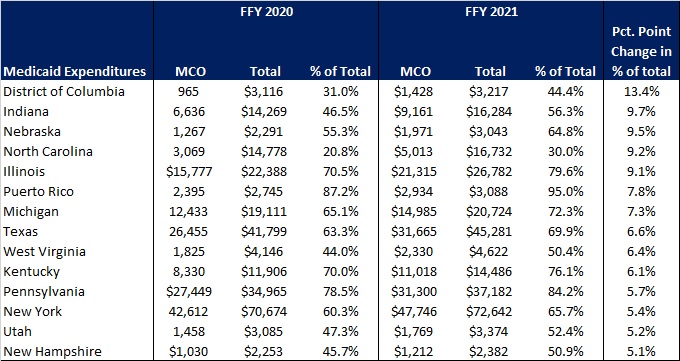
The percentage of Medicaid expenditures directed through risk-based Medicaid MCOs increased by more than  five percentage points in 14 states from FFY 2020 to FFY 2021. The managed care spending penetration rate rose 13.4 percentage points in the District of Columbia, 9.7 percentage points in Indiana, 9.5 percentage points in Nebraska, 9.2 percentage points in North Carolina, and 9.1 percentage points in Illinois.

Figure 5: Medicaid MCO Expenditures as a Percentage of Total Medicaid Expenditures in States with a 5 percent or Greater Increase from FFY 2020 to FFY 2021 ($M)
Source: CMS-64

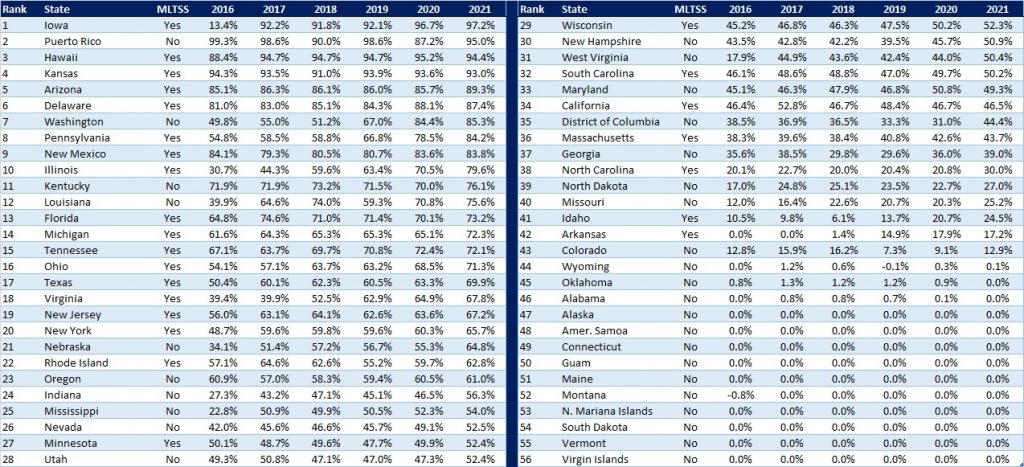
The table below ranks the states and territories by the percentage of total Medicaid spending through Medicaid MCOs. Iowa reported the highest percentage at 97.2 percent, followed by Puerto Rico at 95 percent, and Hawaii at 94.4 percent.

We note that in many states, there are certain payment mechanisms which may never be directed through managed care, such as supplemental funding sources for institutional providers and spending on retroactively eligible beneficiaries. As a result, the maximum achievable penetration rate in each state will vary and may be below that achieved in other states. The Medicaid managed care spending penetration rate is greatly influenced by the degree to which states have implemented managed long-term services and supports (MLTSS) programs.

Figure 6: Medicaid MCO Expenditures as a Percent of Total Medicaid Expenditures, FFY 2016-2021
Non-MCO Expenditures

Despite the rapid growth in Medicaid managed care over the last 10 years, program spending still represented approximately 59 percent of total Medicaid expenditures in FFY 2021. So where is the remaining fee-for-service (FFS) spending (approximately $291 billion) going? First, as noted above, there are many states/territories with Medicaid managed care programs in which certain beneficiaries or services are carved-out of the program, and these are typically associated with high-cost populations. The total amount of non-MCO spending in the 44 states with risk-based managed care in FFY 2021 was $260.4 billion. Assuming an average “full penetration” of 85 percent of total Medicaid spending, then HMA estimates that an additional $221 billion in current FFS spending could shift to a managed care model just in the states that already employ managed care for a subset of services and/or beneficiaries.

Thirteen states/territories did not utilize a comprehensive risk-based managed care model in FFY 2020. In general, the 13 states/territories that do not utilize managed care today are smaller states. Oklahoma, with $5.3 billion in Medicaid spending is expected to shift to risk-based Medicaid managed care in 2023. Total Medicaid spending across all 13 non-managed care states/territories was $29.8 billion. The 13 states/territories that did not employ a risk-based comprehensive Medicaid managed care model in FFY 2021 were Alabama, Alaska, American Samoa, Connecticut, Guam, Maine, Montana, Northern Mariana Islands, Oklahoma, South Dakota, Vermont, Virgin Islands, and Wyoming.

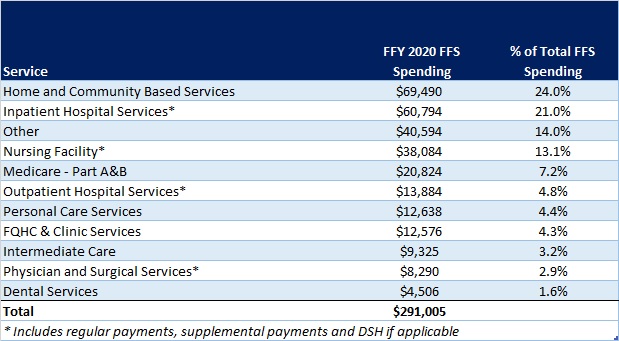
In terms of spending by service line, the largest remaining FFS category is home and community-based services at $69.5 billion, which accounts for 24 percent of FFS spending. Inpatient hospital services represent 21 percent of FFS spending at $60.8 billion.

Figure 7: Fee-for-Service Medicaid Expenditures by Service Line, FFY 2021
While the CMS-64 report provides valuable detail by service line for all FFS expenditures, it does not capture how spending directed to Medicaid MCOs is allocated by category of service. Therefore, it is not possible to calculate total MCO spending by service line, a challenge that will only intensify as more spending runs through MCOs.
Indiana releases MLTSS RFP

This week, our In Focus section reviews the Indiana Medicaid managed long-term services and supports (MLTSS) request for proposals, released by the Indiana Department of Administration on behalf of the Family and Social Services Administration on June 30, 2022. Indiana is seeking three managed care organizations (MCOs) that will serve an estimated 106,000 enrollees, beginning January 1, 2024, for a period of four years, with two one-year renewal options.

MLTSS Program

Indiana began forming a plan to reform the state’s Medicaid LTSS services in 2019 by holding stakeholder meetings. The state estimated that from 2010 to 2030 the proportion of Hoosiers over age 65 will grow from 13 percent to 20 percent, and that the state’s system would need to be reformed to meet the growing demand. The state set an objective to shift the LTSS program to a managed care model and to move a higher percentage of new LTSS members into home and community-based settings.

The new statewide, risk-based MLTSS program will serve Medicaid beneficiaries who are aged 60 years and older and are classified as aged, blind, or disabled. These beneficiaries will include individuals who are dually eligible for Medicare and Medicaid, those in a nursing facility, and those who are receiving LTSS in a home or community-based setting.

Beneficiaries in this program will receive all traditional Medicaid services, delivered through a capitated managed care arrangement. Those who meet a specified level of care will be eligible to receive home and community-based services (HCBS) waiver services. The Medicaid Rehabilitation Option (MRO), Adult Mental Health Habilitation Services Program (AMHH), and Behavioral and Primary Care Coordination (BPHC) will be carved out of the capitated arrangement. For dually eligible beneficiaries, Medicare will be the first payer for all Medicare covered services, including services that are covered by both Medicare and Medicaid.

Indiana seeks to contract with MCOs that can address complex and chronic health conditions of the program population and integrate care along the continuum and settings of LTSS in the state. Program goals include simplifying access to HCBS and expanding the HCBS provider network, especially in rural areas; using a person-centered approach; improving quality outcomes and consistency of care across the delivery system; promoting caregiver support and skill development; in addition to others.

Timeline

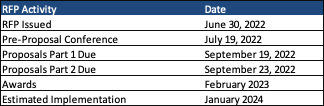
The first part of the proposals is due September 19, with the second part due September 23. Awards are expected in February 2023.

Evaluation

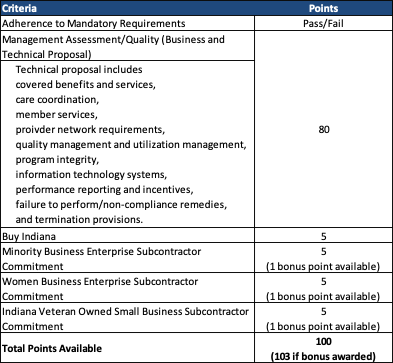
After ensuring proposals meet the mandatory requirement, proposals will be scored out of a total possible 103 points, as shown in the table below.

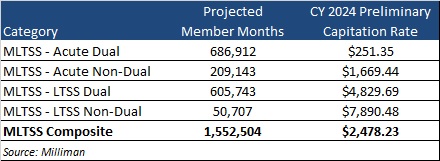
Preliminary Capitation Rate Summary

Based on the preliminary calendar year 2024 capitation rate development, contracts are estimated to be worth $3.8 billion annually.

Link to RFP

Early bird registration discount expires July 11 for HMA conference on the future of publicly sponsored healthcare, October 10-11 in Chicago

Be sure to register for HMA’s 2022 Conference by Monday, July 11, to get the special early bird rate of $1,695 per person. After July 11, the rate is $1,895.

Nearly 40 industry speakers, including health plan executives, state Medicaid directors, and providers, are confirmed for HMA’s The New Normal: How Medicaid, Medicare, and Other Publicly Sponsored Programs Are Shaping the Future of Healthcare in a Time of Crisis conference, October 10-11, at the Fairmont Chicago, Millennium Park.

In addition to keynote sessions featuring some of the nation’s top Medicaid and Medicaid executives, attendees can choose from multiple breakout and plenary sessions on behavioral health, dual eligibles, healthcare investing, technology-enabled integrated care, social determinants of health, eligibility redeterminations, staffing, senior care, and more.

There will also be a Pre-Conference Workshop on The Future of Payment Reform: Delivering Value, Managing Risk in Medicare and Medicaid, on Sunday, October 9.

Visit our website for complete details. Group rates and sponsorships are available. The last HMA conference attracted 500 attendees.

State Medicaid Speakers to Date (In alphabetical order)

  • Cristen Bates, Interim Medicaid Director, CO Department of Healthcare Policy & Financing
  • Jacey Cooper, Medicaid Director, Chief Deputy Director, California Department of Health Care Services
  • Kody Kinsley, Secretary, North Carolina Department of Health and Human Services
  • Allison Matters Taylor, Medicaid Director, Indiana
  • Dave Richard, Deputy Secretary, North Carolina Medicaid
  • Debra Sanchez-Torres, Senior Advisor, Centers for Disease Control and Prevention
  • Jami Snyder, Director, Arizona Health Care Cost Containment System
  • Amanda Van Vleet, Associate Director, Innovation, NC Medicaid Strategy Office, North Carolina Department of Health & Human Services

Medicaid Managed Care Speakers to Date (In alphabetical order)

  • John Barger, National VP, Dual Eligible and Medicaid Programs, Humana, Inc.
  • Michael Brodsky, MD, Medical Director, Behavioral Health and Social Services, L.A. Care Health Plan
  • Aimee Dailey, President, Medicaid, Anthem, Inc.
  • Rebecca Engelman, EVP, Medicaid Markets, AmeriHealth Caritas
  • Brent Layton, President, COO, Centene Corporation
  • Andrew Martin, National Director of Business Development (Housing+Health), UnitedHealth Group
  • Kelly Munson, President, Aetna Medicaid
  • Thomas Rim, VP, Product Development, AmeriHealth Caritas
  • Timothy Spilker, CEO, UnitedHealthcare Community & State
  • Courtnay Thompson, Market President, Select Health of SC, an AmeriHealth Caritas Company
  • Ghita Worcester, SVP, Public Affairs & Chief Marketing Officer, UCare
  • Mary Zavala, Director, Enhanced Care Management, L.A. Care Health Plan

Provider Speakers to Date (In alphabetical order)

  • Daniel Elliott, MD, Medical Director, Christiana Care Quality Partners, eBrightHealth ACO, ChristianaCare Health System
  • Taylor Nichols, Director of Social Services, Los Angeles Christian Health Centers
  • Abby Riddle, President, Florida Complete Care; SVP, Medicare Operations, Independent Living Systems
  • David Rogers, President, Independent Living Systems
  • Mark Sasvary, Chief Clinical Officer, CBHS, IPA, LLC
  • Jim Sinkoff, Deputy Executive Officer, CFO, SunRiver Health
  • Tim Skeen, Senior Corporate VP, CIO, Sentara Healthcare
  • Efrain Talamantes, SVP & COO, Health Services, AltaMed Health Services Corporation

Featured Speakers to Date (In alphabetical order)

  • Drew Altman, President and CEO, Kaiser Family Foundation
  • Cindy Cota, Director of Managed Medicaid Growth and Innovation, Volunteers of America
  • Jesse Hunter, Operating Partner, Welsh, Carson, Anderson & Stowe
  • Bryant Hutson, VP, Business Development, MedArrive
  • Martin Lupinetti, President, CEO, HealthShare Exchange (HSX)
  • Todd Rogow, President, CEO, Healthix
  • Joshua Traylor, Senior Director, Health Care Transformation Task Force
  • James Whittenburg, CEO, TenderHeart Health Outcomes
  • Shannon Wilson, VP, Population Health & Health Equity, Priority Health; Executive Director, Total Health Care Foundation

Oklahoma to transition to Medicaid managed care

This week, our In Focus section reviews a new Oklahoma law to implement Medicaid managed care by October 1, 2023. The law, signed by Governor Kevin Stitt on May 26, 2022, requires the state to issue a request for proposals and to award at least three Medicaid managed care contracts to health plans or provider-led entities like accountable care organizations.

Provider-led entities would receive preferential treatment, with at least one targeted to receive a contract. However, if no provider-led entity submits a response, the state will not be required to contract with one.

Goals of the legislation include:

  • Improve health outcomes for Medicaid members and the state as a whole;
  • Ensure budget predictability through shared risk and accountability;
  • Ensure access to care, quality measures, and member satisfaction;
  • Ensure efficient and cost-effective administrative systems and structures; and
  • Ensure a sustainable delivery system that is a provider-led effort and that is operated and managed by providers to the maximum extent possible.

Plans would provide physical health, behavioral health, and prescription drug services. Covered beneficiaries would include traditional Medicaid members and the state’s voter-approved expansion population, but not the aged, blind, and disabled population eligible for SoonerCare.

Plans will need to contract with at least one local Oklahoma provider organization for a model of care containing care coordination, care management, utilization management, disease management, network management, or another model of care as approved by OHCA.

Oklahoma will also issue separate RFPs for a Medicaid dental benefit manager plan and a Children’s Specialty plan.

Background

Oklahoma currently does not have a fully capitated, risk-based Medicaid managed care program. The majority of the state’s more than 1.2 million Medicaid members are in SoonerCare Choice, a Primary Care Case Management (PCCM) program in which each member has a medical home. Other programs include SoonerCare Traditional (Medicaid fee-for-service), SoonerPlan (a limited benefit family planning program), and Insure Oklahoma (a premium assistance program for low-income people whose employers offer health insurance). Prior efforts to transition to Medicaid managed care have encountered roadblocks, starting in 2017 with a failed attempt to move aged, blind, and disabled members to managed care.

More recently, in June 2021, the Oklahoma Supreme Court struck down a planned transition of the state’s traditional Medicaid program to managed care, ruling that the Oklahoma Health Care Authority does not have the authority to implement the program without legislative approval.

Contracts had been awarded to Blue Cross Blue Shield of Oklahoma, Humana, Centene/Oklahoma Complete Health, and UnitedHealthcare. Centene/Oklahoma Complete Health also won an award for the SoonerSelect Specialty Children’s Health Plan program, covering foster children, juvenile justice-involved individuals, and children either in foster care or receiving adoption assistance.

Link to Senate Bill 1337

HMA conference on “The New Normal for Medicaid, Medicare, and Other Publicly Sponsored Programs” to feature insights from health plan leaders, state Medicaid directors, and providers

Pre-Conference Workshop: October 9, 2022
Conference: October 10-11, 2022
Location: Fairmont Chicago, Millennium Park

HMA Conference on the New Normal for Medicaid, Medicare, and Other Publicly Sponsored Programs to Feature Insights from Health Plan Leaders, State Medicaid Directors, Providers

Early Bird registration is now open for HMA’s fifth national conference on trends in publicly sponsored healthcare. Early Bird Registration Ends July 11th.

Read More

Nebraska releases Medicaid managed care RFP

This week, our In Focus section reviews the Nebraska Heritage Health request for proposals (RFP), released by the Nebraska Department of Health and Human Services (DHHS) on April 15, 2022. DHHS will award statewide contracts to two or three Medicaid managed care organizations (MCOs) to serve approximately 342,000 individuals. Implementation is set to begin July 1, 2023. Contracts are currently worth $1.8 billion annually.

Read More

Texas Releases STAR+PLUS RFP

This week, our In Focus section reviews the Texas STAR+PLUS managed care services request for proposals (RFP) released on March 31, 2022, by the Texas Health and Human Services Commission (HHSC). The STAR+PLUS program, including the STAR+PLUS Home and Community-based Services (HCBS) program, provides acute care services and Long-Term Services and Supports (LTSS) to the aged and disabled.

Read More

Iowa releases Health Link Medicaid managed care RFP

This week, our In Focus section reviews the Iowa Health Link request for proposals (RFP) for Medicaid managed care organizations (MCOs) to serve the state’s traditional Medicaid program, the Children’s Health Insurance Program (CHIP) known as Healthy and Well Kids in Iowa (Hawki), and the Iowa Health and Wellness Plan (IHAWP). The RFP was released by the Iowa Department of Human Services on February 17, 2022. Contracts are set to begin July 1, 2023, and are worth approximately $6.5 billion annually.

Read More

California releases Medi-Cal managed care RFP for three plan models in 21 counties

This week, our In Focus section reviews the California Medicaid (Medi-Cal) managed care request for proposals (RFP) released by the California Department of Health Care Services (DHCS) on February 9, 2022. DHCS is procuring contracts for commercial plans for three of the Medi-Cal managed care plan models in 21 counties, serving approximately 3 million beneficiaries. Contracts will be awarded to one managed care organization (MCO) in each of the Two-Plan model counties, two MCOs in each of the geographic managed care (GMC) model counties, and two MCOs in each of the Regional model counties. This procurement is the largest released by California, rebidding contracts for commercial plans statewide.

Read More

Delaware Releases Medicaid Managed Care RFP

This week our In Focus section reviews the Delaware request for proposals (RFP) for Diamond State Health Plan (DSHP) and Diamond State Health Plan Plus (DSHP Plus), the state’s Medicaid managed care programs. The RFP was released by the Delaware Department of Health and Social Services (DHSS), Division of Medicaid and Medical Assistance (DMMA) on December 15, 2021.

Read More

Ready to talk?