
HMA Insights—including briefs, webinars, and our podcast—gives you easy access to HMA’s deep expertise, helping you stay current on the latest healthcare trends and topics. Search for a topic of interest or browse the latest insights below.

An HMA Toolkit and Webinar to Advance Health Equity & Access for Rural Dually Eligible Individuals

As respiratory syncytial virus (RSV), a seasonal pathogen in young children is challenging the national health care system as part of an unprecedented “tripledemic” with COVID-19 and flu this winter, HMA authors weigh in on potential coverage pathways for new monoclonal antibody (mAb) preventive therapies for RSV and their implications for access.
The Vaccines for Children (VFC) program is a proven vehicle for ensuring comprehensive coverage of immunizations based on recommendations from the Advisory Committee on Immunization Practices (ACIP). An ACIP workgroup is actively discussing potential recommendations for immunization with RSV mAbs.
In the recent Health Affairs Forefront article, “Coverage By Vaccines For Children Program Is Critical For RSV Therapy Access,” HMA authors Helen DuPlessis, MD, FAAP, Diana Rodin, and Matt Wimmer explore the implications of ACIP recommendations, Medicaid coverage pathways, and children’s access to the new therapies.
This week, our In Focus section reviews changes to Medicaid’s COVID-19 Public Health Emergency (PHE) unwinding. People enrolled in the Medicaid program have been continuously enrolled for almost three years, but that situation is about to change. In December 2022, Congress passed, and the President signed into law a massive compromise bill to fund the government. It includes an important change to Medicaid’s continuous enrollment policy, which has been in effect since the early days of the COVID-19 PHE in March 2020.
Congress passed the Families First Coronavirus Relief Act (FFCRA) in March 2020. This legislation has allowed states to receive a 6.2 percentage point increase in their federal matching rate for Medicaid. As a condition for receiving the enhanced funding, states have been prohibited from disenrolling individuals who were otherwise determined ineligible for Medicaid. As a result, nearly 20 million more people are now enrolled in the Medicaid program.
The 2023 spending bill severs the link between the COVID-19 PHE declaration, the continuous enrollment requirement, and the higher federal match rate. The new law:
Congress also added new parameters and reporting requirements for states as they resume annual eligibility renewals with coverage cancellation for individuals who no longer qualify. These requirements are in addition to data the Centers for Medicare & Medicaid Services (CMS) previously directed states to report. For example:
Beyond the “Delinking”
The new law includes other important eligibility-related policies that may affect state and stakeholder planning for what is often referred to as the “unwinding” of continuous enrollment. Notably, the state Medicaid and CHIP programs will now be required to provide 12 months of continuous coverage for children. A total of 24 states already have adopted the 12-month continuous eligibility option for all children enrolled in Medicaid. While the new requirement will not take effect until January 1, 2024, additional states could adopt this option as they resume normal eligibility operations.
In addition, the new law makes permanent the option for states to extend Medicaid postpartum coverage to 12 months, up from 60 days. The one-year postpartum coverage option initially was approved in the American Rescue Plan but for a limited period of five years. Making the option permanent provides more certainty for states. Nearly two-thirds of states have already implemented or are planning to implement the 12-month postpartum coverage extension.
What Happens Next?
The definitive end date for the continuous enrollment policy sets in motion certain federal and state actions and the process for unwinding. On January 5, 2023, CMS published its first guidance to states on processes related to the new unwinding date. The agency is developing additional guidance and will use other communication tools to provide states with greater clarity on the new statutory reporting, matching rate, and federal agency expectations and oversight.
State plans: All states must submit unwinding plans to CMS by February 15; however, February 1 is the deadline for states that intend to begin renewals in February. These proposals must provide details regarding unwinding strategies, the timeline for starting enrollee renewals, and the pace of ongoing renewal processes. The specific end date for the continuous enrollment policy is driving more states to review and finalize their initiatives and engage with stakeholders.
Impact on health plans and providers: The unwinding process will create important decision points and considerations for Medicaid health plans and providers that have members and patients whom the unwinding process may affect in the next 12-18 months. The law’s requirements reinforce the imperative for states, Medicaid health plans, providers, and other partners to renew efforts to confirm enrollee contact information. The unwinding all will create new considerations for Medicaid health plans with respect to enrollee support, case mix, and rate setting issues.
State budgets and legislation: Many states will kick off their legislative sessions this month. The unwinding process—especially the phase-out of higher federal funding—has important implications for state budgets. State legislatures also may address the new continuous eligibility requirements for children and the permanent option for 12 months of postpartum coverage. As a result, Medicaid will likely remain a top priority during upcoming legislative sessions.
Federal oversight and enforcement: The law’s enhanced reporting provision is intended to provide safeguards to ensure eligible individuals remain enrolled in Medicaid. The reporting also focuses on data related to identifying and directing individuals likely to be eligible for the Marketplace program. Although CMS must publicly report these data, the agency has offered no specific timeline for posting the information. Notably CMS has oversight tools and may impose financial penalties on states that are noncompliant with the unwinding requirements.
Forthcoming federal guidance will confirm the parameters for state unwinding actions, CMS’s plans for oversight of state work, and how these efforts affect current Medicaid enrollees. Medicaid partners should closely monitor state level actions, including announcement of state unwinding plans and opportunities for collaboration. Earlier blogs describe the strategies and actions HMA is working with states and partners to undertake as they prepare for this significant change in Medicaid eligibility policies.
Please contact HMA experts below for more information.
This week, our In Focus section reviews a rule proposed by the Centers for Medicare & Medicaid Services (CMS) on December 14, 2022, that would revise regulations governing Medicare Advantage (MA or Part C), the Medicare Prescription Drug Benefit (Part D), Medicare cost plans and Programs of All-Inclusive Care for the Elderly (PACE).
The proposed rule reflects the agency’s focus on increasing transparency, improving health equity, reducing the cost of care, and improving access to behavioral health services. Collectively, these are among the most impactful policy changes CMS has proposed to the MA and Part D programs in recent years. CMS also writes that many of the policy proposals are informed by public comments to the agency’s earlier requests for input.
MA and Part D stakeholders will want to consider providing feedback and analysis to CMS regarding the impact of these changes. The changes would begin to take effect for contract year 2024, but stakeholders can begin gap assessments and strategic planning now. Comments on the proposed rule are due by February 13, 2023.
The rule proposes to increase the transparency of MA plans’ utilization management and prior authorization policies, with the goal of ensuring that MA enrollees receive the same access to medically necessary care they would receive in Traditional Medicare.
The proposed rule also takes steps to address potentially misleading marketing while also ensuring that Medicare beneficiaries have accurate information to make coverage choices.
The prosed rule includes several policies designed to increase health equity across the program.
CMS proposes policies to strengthen network adequacy requirements and reaffirms the responsibility of MA organizations to provide behavioral health services.
CMS proposes greater formulary flexibility for MA and Part D plans for certain biological products and authorized generics. CMS proposes to permit Part D sponsors to immediately substitute: (1) a new interchangeable biological product for its corresponding reference product; (2) a new unbranded biological product for its corresponding brand name biological product; and (3) a new authorized generic for its corresponding brand name equivalent.
In addition, CMS proposes several new requirements for Part D sponsors related to Medication Therapy Management (MTM) programs.
The LI NET program currently operates as a demonstration program that provides immediate and retroactive Part D coverage for eligible low-income beneficiaries who do not yet have prescription drug coverage. In this proposed rule, CMS proposes making the LI NET program a permanent part of Medicare Part D, as required by statute.
CMS proposes to implement a section of the Inflation Reduction Act (IRA), enacted in August 2022, which expands eligibility under the Part D low-income subsidy (LIS) program. Under the provision, individuals with incomes up to 150 percent of the federal poverty level (FPL) and who meet statutory resource requirements will qualify for the full low-income subsidy beginning on or after January 1, 2024. This change will provide the full subsidy to those who currently qualify for only a partial subsidy.
The proposed rule includes several proposals to codify existing policies that govern special needs
plans (SNP), which are MA plans specifically designed to provide targeted care and limit enrollment to special needs individuals. Specifically, CMS proposes to codify recent statutory requirements concerning the definition of severe or disabling chronic condition and several other provisions relating to the definition of a Chronic Condition SNP. The rule also proposes several updates to policies governing Programs of All-Inclusive Care for the Elderly (PACE), including technical changes to PACE contracting and application evaluation processes, requirements for medical clearance of PACE personnel, requirements for contracting for specialty services, and codification of certain care planning and care coordination requirements.
The HMA Medicare team will continue to analyze these proposed changes. We have the depth and breadth of expertise to assist with tailored analysis, to model policy impacts, and to support the drafting of comment letters to this rule.
If you have questions about the contents of CMS’s Medicare Advantage proposed rule and how it will impact MA plans, providers, and patients, please contact our experts below.
CMS Introduces Significant Proposed Changes to Medicare Advantage and Medicare Prescription Drug Benefit Programs for 2024
This week, our In Focus section reviews the State of Texas Access Reform (STAR), Children’s Health Insurance Program (CHIP), and Healthy Texas Women (HTW) Medicaid managed care request for proposals (RFP) released by the Texas Health and Human Services Commission (HHSC) on December 7, 2022. Medicaid managed care organizations (MCOs) will serve over 4.6 million members. Prior STAR & CHIP program contracts were valued at roughly $9.7 billion annually, with new contracts to be worth more.
Texas is currently in the process of rebidding all of its Medicaid managed care programs. A former STAR & CHIP RFP was cancelled in March 2020.
STAR is Texas’ traditional Medicaid program. Under the STAR program, MCOs will provide preventive, primary, acute care, behavioral health (including mental health and substance-use disorder counseling and treatment), Non-Emergency Medical Transportation (NEMT), and pharmacy services to eligible pregnant women, newborns, children, and parents with limited income.
CHIP is the state-federal jointly funded program covering children whose families who earn too much to qualify for Medicaid but cannot afford private insurance. In Texas, CHIP contracts also include the CHIP Perinatal Program covering pregnant women who are ineligible for Medicaid due to income or immigration status to receive prenatal care for their unborn children. Once born, newborns receive 12 months of continuous coverage.
The HTW program provides family planning services, family planning-related services, and other preconception women’s health services. The HTW program was originally a fee-for-service program until the Centers for Medicare & Medicaid Services (CMS) approved a Section 1115 waiver demonstration in January 2020. Texas is currently waiting on CMS approval for a waiver amendment to also add HTW Plus, an enhanced postpartum benefits package, into Medicaid managed care.
HHSC intends to award at least three contracts for each service area (SA). The maximum number of MCOs that will be awarded in the new procurement for each SA is shown below.
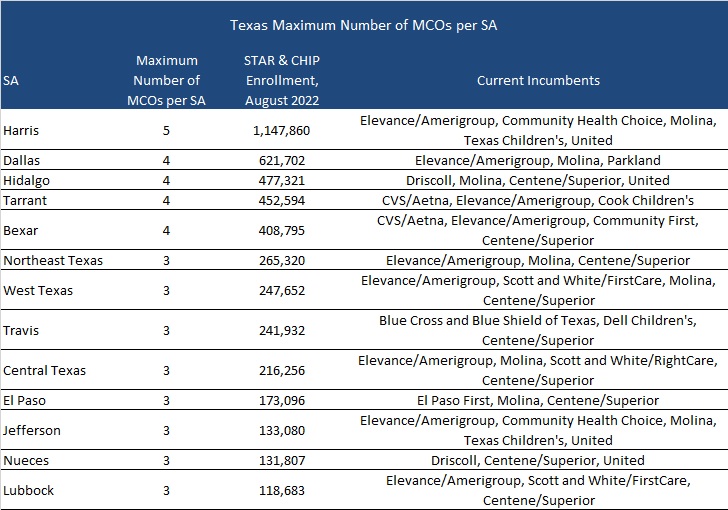
As of August 2022, STAR enrollment was 4.56 million and CHIP enrollment was over 97,000.
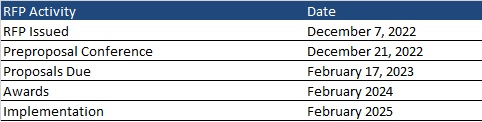
A preproposal conference will be held on December 21, 2022. While optional, the conference is recommended and will include training on the completion of the Historically Underutilized Business (HUB) Subcontracting Plan. Proposals will be due February 17, 2023, with awards anticipated in February 2024. Implementation is expected February 2025. Contracts will run for six years, with three two-year renewal options, not to exceed a total contract term of 12 years.
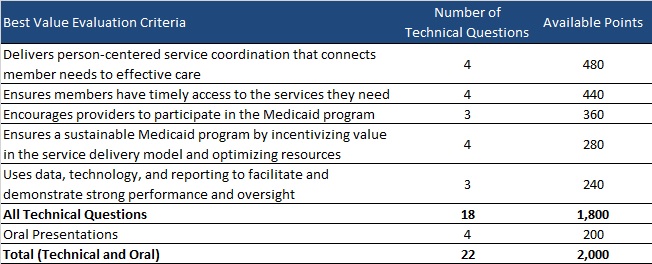
MCOs will be scored out of 2,000 points as shown below. HHSC will recommend contract awards in SAs based on MCOs’ final weighted scores and will take consideration of MCOs’ ranking of SAs by preference.
Each MCO can be awarded contracts in up to seven SAs. However, HHSC may choose to award more per MCO if the SA has not reached a maximum number of MCOs.
Link to RFP

